Sulphonamides, also referred to as sulpha drugs, constitute an important group of antimicrobial agents whose activity is closely associated with the disruption of folate metabolism in pathogenic microorganisms. Folate-derived compounds are indispensable to bacterial cells because they participate in metabolic pathways that generate essential precursors for nucleic acid production, cellular proliferation, and other fundamental biological processes. By interfering with this metabolic framework, sulphonamides exert their antimicrobial effects through a mechanism that differs fundamentally from antibiotics that directly target bacterial structures.
Sulphonamides are classified as antimetabolites. Antimetabolites are a group of antimicrobial compounds that resemble naturally occurring metabolites required for microbial growth and survival. Their structural similarity to essential metabolic substrates enables them to interfere with biochemical pathways that would otherwise support normal cellular development. Within the broader context of antimicrobial chemotherapy, compounds associated with antifolate activity include sulphonamides, trimethoprim, and pyrimethamine, while combinations such as sulphamethoxazole–trimethoprim demonstrate how sequential interference with folate metabolism can enhance antibacterial activity.
The significance of sulphonamides extends beyond their individual antimicrobial properties because they represent an important example of metabolic pathway inhibition in infectious disease treatment. Rather than primarily damaging bacterial membranes or disrupting cellular proteins, these agents interfere with the availability and utilization of metabolic intermediates necessary for continued growth. Folate metabolism is particularly important because it contributes to the production of compounds required for the formation of bacterial DNA and RNA, thereby linking metabolic activity with genetic replication and cellular multiplication.
The mode of action of sulphonamides illustrates how selective disruption of bacterial metabolism can impair pathogen viability while establishing a foundation for examining antimicrobial activity, therapeutic applications, and resistance mechanisms.
Sources of Sulphonamides
Sulphonamides are predominantly synthetic antibacterial agents obtained through deliberate chemical synthesis rather than direct isolation from living microorganisms. Their development marked an important transition in antimicrobial chemotherapy, as these compounds demonstrated that antibacterial activity could be achieved by designing chemical substances capable of selectively interfering with essential processes within pathogenic bacteria. Unlike several other classes of antibacterial agents whose origins can be traced to microbial fermentation, sulphonamides are manufactured through controlled chemical reactions involving appropriately selected aromatic and sulphonamide-containing compounds.
The historical foundation of the sulphonamide group is closely associated with sulphanilamide, a compound that emerged from investigations into the antibacterial properties of azo dyes. An important early compound was Prontosil, an azo dye whose antibacterial activity led to the identification of sulphanilamide as the active component generated within the body. This discovery provided the chemical and pharmacological basis for subsequent development of the sulphonamide family. Many modern sulphonamides can be regarded as products of structural modification and systematic optimization of the sulphanilamide nucleus.
The synthetic production of sulphonamides involves modifying specific chemical groups within the parent structure to generate compounds with differing pharmacological characteristics. Such modifications can influence antibacterial potency, absorption, distribution, metabolism, duration of action, and tolerability. Through progressive chemical refinement, numerous derivatives have been developed, each possessing distinctive physicochemical properties while retaining the fundamental sulphonamide framework responsible for their antimicrobial activity.
The source of sulphonamides is therefore fundamentally chemical rather than biological. They are produced under controlled laboratory and industrial conditions using organic synthesis, allowing their molecular architecture to be manipulated according to desired therapeutic properties. This distinguishes them from naturally derived antibacterial substances such as penicillins and many other antimicrobial compounds initially obtained from microorganisms. The synthetic origin of sulphonamides reflects the evolution of medicinal chemistry from the discovery of naturally occurring antimicrobial substances toward the purposeful design and modification of compounds with specific biological activities.
Structure of sulphonamides
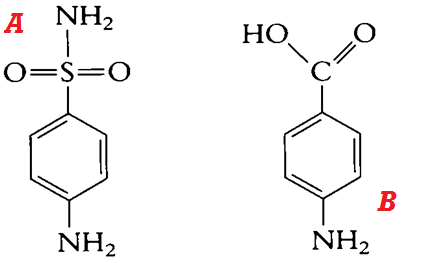
The structural foundation of sulphonamide antibiotics is represented by sulphanilamide. Sulfanilamide is a simple aromatic compound that provides the essential molecular framework from which numerous sulphonamide derivatives have been developed. Sulphanilamide contains structural features that closely resemble those of para-aminobenzoic acid (PABA), a naturally occurring bacterial metabolite involved in folate biosynthesis. This resemblance is central to the biological significance of the sulphonamide scaffold because it enables these compounds to interact with biochemical processes that normally recognize PABA.
As illustrated in Figure 1A, sulphanilamide provides the parent structure of the sulphonamide family, whereas Figure 1B presents the corresponding structure of PABA. Although the two molecules are not chemically identical, their related molecular architecture gives sulphonamides the characteristics required for their classification as structural analogues of PABA. The aromatic ring and associated functional groups contribute to the physicochemical properties of the molecule, while subsequent chemical alterations can influence characteristics such as solubility, stability, distribution, and antimicrobial performance.
The sulphonamide nucleus consequently serves as a versatile platform for synthetic modification. Chemists have exploited this framework by introducing different substituents onto specific regions of the parent molecule, generating a broad range of derivatives with distinct chemical and pharmacological properties. Such modifications have expanded the sulphonamide class beyond the original sulphanilamide structure and produced compounds suited to different therapeutic applications.
The structural diversity observed among sulphonamides therefore arises primarily from systematic chemical modification of the parent scaffold rather than from an entirely different molecular framework for each compound. Despite variations in their substituent groups, these derivatives retain the characteristic sulphonamide moiety that defines the class. Examination of sulphanilamide alongside PABA consequently provides a useful structural basis for understanding the molecular identity of sulphonamides and the relationship between their chemical architecture and biological function.
Clinical application of sulphonamides
Sulphonamides occupy an established position in antimicrobial chemotherapy because of their ability to interfere with essential metabolic processes required for the survival and multiplication of susceptible microorganisms. Their clinical relevance is particularly evident in the management of selected bacterial infections in which susceptibility is demonstrated and appropriate therapeutic alternatives may be limited. Among their recognized applications, urinary tract infections (UTIs) represent an important clinical setting, particularly where susceptible organisms are responsible for infection. Their usefulness in this context is associated with the pharmacological characteristics of specific sulphonamide preparations and their capacity to reach therapeutically relevant concentrations at sites of infection.
Beyond urinary tract infections, sulphonamide-containing therapies have been employed in the management of several other infectious conditions. These include selected cases of otitis media, lower respiratory tract infections, bacterial endocarditis, rheumatic fever, chlamydial infections, and nocardiosis. Their application across these conditions reflects the diversity of microorganisms that may remain susceptible to sulphonamide-based treatment. However, clinical selection is influenced by the causative organism, antimicrobial susceptibility, infection site, patient-specific considerations, and prevailing patterns of resistance.
The therapeutic importance of sulphonamides also extends beyond conventional bacterial disease. Certain members of this antimicrobial group have demonstrated activity against protozoal pathogens, providing a role in the treatment of particular non-bacterial infections. This broader antimicrobial scope illustrates the significance of metabolic inhibition as a therapeutic strategy and highlights how interference with essential biochemical pathways can affect organisms from different microbial groups.
A particularly important development in the clinical use of sulphonamides is their combination with trimethoprim. The sulphamethoxazole–trimethoprim combination is widely recognized for producing enhanced antimicrobial activity compared with either component administered independently. This combination targets sequential stages within microbial folate metabolism, producing a more pronounced interruption of the pathway and thereby improving activity against susceptible organisms. Its spectrum encompasses a range of Gram-positive bacteria and Gram-negative bacilli, although its effectiveness varies according to the organism and local resistance patterns.
The continued clinical relevance of sulphamethoxazole–trimethoprim demonstrates the value of rational antimicrobial combinations in managing infections where resistance or reduced susceptibility may compromise single-agent therapy. Nevertheless, sulphonamide use requires appropriate microbiological and clinical assessment because resistance has progressively altered their effectiveness against several bacterial pathogens. Their contemporary application is best understood within the broader framework of antimicrobial susceptibility, responsible prescribing, and pathogen-directed therapy.
Spectrum of activity of sulphonamides
Sulphonamides exhibit a comparatively broad spectrum of antimicrobial activity, with effects extending across several groups of clinically significant bacteria. Their antibacterial range encompasses a number of Gram-positive organisms as well as selected Gram-negative species, although the degree of susceptibility differs considerably among bacterial groups. This variation is influenced by differences in metabolic requirements, cellular permeability, intrinsic resistance characteristics, and the capacity of individual organisms to acquire or develop resistance to these agents.
The antimicrobial spectrum of sulphonamides is closely associated with their interference with folate-dependent metabolic processes. Since susceptible bacteria rely on endogenous folate synthesis to produce metabolites required for cellular proliferation, disruption of this pathway can restrict bacterial multiplication. Sulphonamides are generally regarded as bacteriostatic antibiotics, meaning that their primary effect is to suppress bacterial growth and reproduction rather than produce rapid bacterial destruction. This distinction is important when considering their therapeutic behaviour and their interaction with host immune mechanisms.
The spectrum of sulphonamide activity is not uniform, however, and their effectiveness against particular pathogens has changed over time because of widespread antimicrobial resistance. Some bacterial species possess intrinsic mechanisms that reduce susceptibility, while others may acquire resistance through genetic alterations affecting drug uptake, target enzymes, or metabolic pathways. Therefore, the classification of sulphonamides as broad-spectrum agents should not be interpreted as universal activity against all Gram-positive and Gram-negative bacteria.
Sulphonamides also provide an important basis for understanding the broader pharmacological concept of antimetabolite therapy. Although sulphonamides themselves are predominantly bacteriostatic, certain antimetabolite combinations can produce more pronounced antibacterial effects through simultaneous interference with sequential stages of folate metabolism. The distinction between bacteriostatic and bactericidal activity consequently depends not only on the antimicrobial class but also on the specific compound, concentration, organism, and therapeutic combination involved. The spectrum of sulphonamides reflects their capacity to affect diverse bacterial populations while demonstrating the limitations imposed by organism-specific susceptibility and antimicrobial resistance.
Mechanism or mode of action of sulphonamides
Sulphonamides exert their antimicrobial activity primarily by disrupting the folate biosynthetic pathway of susceptible bacteria. Folate, or folic acid derivatives, is essential for the production of metabolic intermediates involved in the synthesis of nucleic acids and other cellular constituents. Unlike humans, many bacteria must synthesize folate de novo because they cannot efficiently obtain sufficient quantities of preformed folate from their environment. This metabolic distinction provides an important basis for the selective toxicity of sulphonamides.
The principal target of sulphonamides is para-aminobenzoic acid (PABA), a normal substrate used during the early stages of bacterial folate synthesis. Sulphonamides possess structural similarities to PABA and therefore function as competitive antimetabolites. They compete with PABA for the active site of the enzyme dihydropteroate synthase (DHPS), which normally catalyses the incorporation of PABA into an intermediate required for subsequent folate production. When sulphonamides occupy the enzyme’s active site, the normal utilization of PABA is impeded, reducing the formation of downstream folate intermediates.
This interruption has consequences that extend beyond folate metabolism itself. Reduced availability of biologically active folate derivatives limits the synthesis of nucleotide precursors required for DNA and RNA production. Bacterial replication, cellular proliferation, and other processes dependent on nucleic acid synthesis become progressively restricted. Sulphonamides are therefore generally regarded as bacteriostatic agents, meaning that they primarily suppress bacterial multiplication rather than directly causing rapid cellular destruction. The eventual outcome, however, depends on factors such as the susceptibility of the organism, drug concentration, and host immune function.
The antimicrobial effect can be intensified through sequential blockade of the folate pathway, as demonstrated by the combination of sulphamethoxazole and trimethoprim. Sulphamethoxazole inhibits DHPS at an early stage, whereas trimethoprim acts subsequently by inhibiting dihydrofolate reductase (DHFR). This second blockade prevents the conversion of dihydrofolate into the reduced folate form required for essential biosynthetic reactions. By targeting successive enzymatic steps, the combination produces a more extensive interruption of bacterial folate metabolism than either component acting alone.
The selectivity of this pathway is also pharmacologically significant. Mammalian cells do not synthesize folate through the bacterial PABA-dependent pathway; instead, humans obtain folate primarily through dietary sources. This fundamental biochemical difference allows sulphonamides to preferentially interfere with microbial metabolism while exerting comparatively limited effects on the corresponding folate pathway in human cells.
Bacterial resistance to sulphonamides
The therapeutic usefulness of sulphonamides is increasingly influenced by the capacity of certain pathogenic bacteria to withstand their inhibitory effects. Bacterial resistance represents a significant challenge in antimicrobial therapy because it can reduce the effectiveness of treatment and allow susceptible infections to persist despite appropriate drug administration. The emergence of resistance is particularly relevant to sulphonamides because their antibacterial activity depends on interference with an essential metabolic pathway rather than direct destruction of the bacterial cell.
An important determinant of intrinsic susceptibility is the manner in which a bacterium acquires and utilizes folate. Bacteria that depend on the endogenous synthesis of folate are more vulnerable to agents that interfere with this pathway. In contrast, microorganisms capable of obtaining sufficient folate or related metabolites from their surrounding environment may demonstrate reduced susceptibility because they can circumvent the metabolic restriction imposed by sulphonamides. This distinction highlights the importance of bacterial physiology in determining antimicrobial response and helps explain why the activity of sulphonamides is not uniform across different microbial species.
Resistance may also arise through adaptive changes that alter the interaction between the antimicrobial agent and its metabolic target. Changes affecting enzymes involved in folate biosynthesis can diminish the ability of sulphonamides to interfere effectively with metabolic reactions. In addition, alterations in bacterial transport processes, metabolic compensation, or the acquisition of resistance determinants can contribute to reduced drug sensitivity. Such mechanisms may occur through spontaneous genetic variation or through the acquisition of transferable genetic material, allowing resistance traits to disseminate among bacterial populations.
The limitations associated with sulphonamide monotherapy have encouraged the development and continued use of strategic drug combinations. A notable example is the combination of sulphamethoxazole and trimethoprim, in which two agents interfere with sequential stages of bacterial folate metabolism. This complementary approach can produce a stronger antimicrobial effect than either compound used independently and may reduce the likelihood that bacteria will successfully bypass the entire metabolic blockade. Bacterial resistance to sulphonamides should be viewed not simply as a loss of drug sensitivity, but as an evolving interaction between antimicrobial pressure, bacterial metabolism, genetic adaptation, and therapeutic strategy.
Pharmacokinetics of sulphonamides
The pharmacokinetic profile of sulphonamides describes how these antimicrobial agents enter the body, circulate through biological compartments, undergo biochemical transformation, and are ultimately removed. Their disposition is influenced by the particular sulphonamide used, its formulation, dose, route of administration, and the physiological characteristics of the individual receiving treatment. These factors collectively determine the concentration of the drug available at sites of infection and consequently influence its therapeutic performance.
Following oral administration, many sulphonamides are absorbed efficiently from the gastrointestinal tract. Their absorption permits systemic exposure and makes oral therapy an important route for administering several members of this antimicrobial class. Once absorbed, the drugs enter the bloodstream and become distributed throughout body tissues and fluids. The extent of distribution varies among individual sulphonamides and is influenced by properties such as lipid solubility, degree of ionization, protein binding, and tissue permeability. These characteristics affect both the duration of antimicrobial exposure and the extent to which a drug reaches particular anatomical sites.
Within the circulation, sulphonamides may associate with plasma proteins, particularly albumin. Protein binding creates a reversible reservoir of drug in the bloodstream, with the unbound fraction generally representing the portion that is immediately available for distribution into tissues and interaction with biological targets. Differences in protein binding among sulphonamides can therefore contribute to variation in their pharmacological behavior and duration of action.
Sulphonamides also undergo varying degrees of biotransformation, predominantly in the liver. Metabolic processes can modify the chemical structure of the parent compound and produce metabolites with different pharmacological characteristics. The extent of hepatic metabolism differs between individual agents and may influence their persistence within the body. Pharmacokinetic distinctions among sulphonamides are relevant when considering dosing intervals and the potential for accumulation.
Renal elimination represents a major pathway for the removal of many sulphonamides and their metabolites. After circulating through the body, these compounds are filtered and processed by the kidneys before being eliminated in the urine. Renal function can therefore influence the persistence of sulphonamides in the systemic circulation. Alterations in kidney function may affect drug clearance and, depending on the specific agent, may necessitate careful consideration of dosage and administration intervals. The pharmacokinetic behavior of sulphonamides reflects a coordinated sequence of gastrointestinal absorption, systemic distribution, metabolic transformation, and predominantly urinary excretion.
Side effects and toxicity of sulphonamides
Although sulphonamides are generally tolerated by many patients when administered at appropriate therapeutic doses, their use can be accompanied by a range of adverse reactions. The severity of these effects varies considerably among individuals and may depend on factors such as dosage, duration of treatment, age, concurrent medication, and individual susceptibility. The clinical use of sulphonamides requires awareness of their potential toxicological effects, particularly when treatment is prolonged or when the patient has a heightened sensitivity to these agents.
One of the more frequently encountered manifestations is cutaneous irritation, which may appear as a mild skin rash, redness, itching, or other forms of dermatological discomfort. In susceptible individuals, these reactions can become more pronounced and may be accompanied by fever or a general feeling of malaise. Such responses are often associated with hypersensitivity rather than with the direct pharmacological action of the drug. The appearance of unexplained skin changes during sulphonamide therapy therefore warrants clinical attention, especially if the symptoms progress rapidly.
Gastrointestinal disturbances may also occur during treatment. Patients can experience nausea, vomiting, abdominal discomfort, or diarrhoea, which may affect adherence to therapy when symptoms become persistent. These reactions can arise from intolerance to the medication and may vary in intensity from relatively minor discomfort to symptoms significant enough to require medical assessment.
A particularly important consideration is hypersensitivity to sulphonamides. Hypersensitivity reactions can develop following administration, even in individuals who have previously tolerated similar medication. The response may range from relatively mild manifestations, such as rash and fever, to more serious systemic reactions. For this reason, a history of previous drug reactions should be considered before therapy is initiated.
The toxicological profile of sulphonamides also emphasizes the importance of appropriate administration and patient monitoring. While adverse effects are not inevitable, their potential occurrence demonstrates that antimicrobial therapy involves a balance between therapeutic benefit and unwanted biological responses. Recognizing early symptoms can facilitate timely intervention and reduce the likelihood of complications.
The side effects associated with sulphonamides encompass dermatological, gastrointestinal, febrile, and hypersensitivity-related manifestations. Understanding these reactions is essential for responsible antimicrobial use and provides an important foundation for considering patient safety alongside the therapeutic effectiveness of sulphonamide treatment.
References
Ovung, A., & Bhattacharyya, J. (2021). Sulfonamide drugs: Structure, antibacterial property, toxicity, and biophysical interactions. Biophysical Reviews, 13(2), 259–272.
Brownlee, G. (1949). The sulphonamides and allied compounds. Nature, 163, 662.
Ball, A. P., Gray, J. A., & Murdoch, J. M. (1978). The sulphonamides. In Antibacterial drugs today. Springer.
Campbell, K. L. (1999). Sulphonamides: Updates on use in veterinary medicine. Veterinary Dermatology, 10, 205–215.
Mandell, G. L., & Petri, W. A., Jr. (1996). Sulfonamides, trimethoprim-sulfamethoxazole, quinolones, and agents for urinary tract infections. In J. G. Hardman, L. E. Limbird, P. B. Molinoff, R. W. Ruddon, & A. G. Gilman (Eds.), Goodman and Gilman’s the pharmacological basis of therapeutics (9th ed., pp. 1057–1072). McGraw-Hill.
Mandelbaum, M. (1941). Action of sulphonamides and their derivatives on bacteria. Nature, 147, 266–267.
Klagkou, K., Pullen, F., Harrison, M., Organ, A., Firth, A., & Langley, G. J. (2003). Fragmentation pathways of sulphonamides under electrospray tandem mass spectrometric conditions. Rapid Communications in Mass Spectrometry, 17(21), 2373–2379.
Scholer, H. J., Leimer, R., & Richle, R. (1984). Sulphonamides and sulphones. In W. Peters & W. H. G. Richards (Eds.), Antimalarial drug II (Handbook of Experimental Pharmacology, Vol. 68/2). Springer.
Axelsen P. H (2002). Essentials of Antimicrobial Pharmacology. Humana Press, Totowa, NJ.
Chemotherapy of microbial diseases. In: Chabner B.A, Brunton L.L, Knollman B.C, eds. Goodman and Gilman’s The Pharmacological Basis of Therapeutics. 12th ed. New York, McGraw-Hill; 2011.
Chung K.T, Stevens Jr., S.E and Ferris D.H (1995). A chronology of events and pioneers of microbiology. SIM News, 45(1):3–13.
Drusano G.L (2007). Pharmacokinetics and pharmacodynamics of antimicrobials. Clin Infect Dis, 45(suppl):89–95.
Engleberg N.C, DiRita V and Dermody T.S (2007). Schaechter’s Mechanisms of Microbial Disease. 4th ed. Lippincott Williams & Wilkins, Philadelphia, USA.
Finch R.G, Greenwood D, Norrby R and Whitley R (2002). Antibiotic and chemotherapy, 8th edition. Churchill Livingstone, London and Edinburg.
Discover more from Microbiology Class
Subscribe to get the latest posts sent to your email.