Penicillins are a class of β-lactam antibiotics that interfere with bacterial cell wall biosynthesis. They do this by disrupting the formation of peptidoglycan, a structural polymer essential for maintaining cellular shape, rigidity, and osmotic stability. Their antibacterial activity is primarily associated with the inhibition of penicillin-binding proteins (PBPs), particularly the transpeptidases responsible for the final cross-linking of peptidoglycan strands. This mechanism compromises the mechanical strength of the bacterial envelope, making susceptible organisms vulnerable to osmotic pressure and subsequent cell lysis.
The peptidoglycan network consists of alternating residues of N-acetylglucosamine (NAG) and N-acetylmuramic acid (NAM), interconnected by short peptide chains. These glycan strands form a mesh-like structure surrounding the bacterial cytoplasmic membrane. During cell wall assembly, transglycosylases extend the glycan chains, while transpeptidases establish peptide cross-links that reinforce the developing network. Penicillins target this coordinated process by interacting with the active sites of susceptible PBPs, thereby preventing the completion of peptide cross-linking and weakening the structural framework of the cell wall.
The molecular activity of penicillins depends on the characteristic β-lactam ring, which resembles the terminal D-alanyl-D-alanine substrate recognized by transpeptidases. This structural similarity enables the antibiotic to bind to the enzyme’s active site and form a stable, covalent acyl-enzyme complex. Unlike the natural substrate, which undergoes enzymatic processing, the penicillin molecule inactivates the enzyme, interrupting the normal progression of peptidoglycan maturation. Newly synthesized cell wall material becomes inadequately cross-linked, reducing the bacterium’s capacity to withstand internal osmotic pressure.
Penicillins generally exhibit bactericidal activity against susceptible bacteria, particularly when organisms are actively growing and synthesizing their cell walls. Their effectiveness is influenced by bacterial species, drug concentration, accessibility to PBPs, and the physiological state of the microorganism. Gram-positive bacteria are often susceptible because their thick peptidoglycan layer is exposed outside the cytoplasmic membrane. In Gram-negative bacteria, however, the outer membrane can restrict antibiotic entry, while porin permeability and β-lactamase production further influence susceptibility.
The discovery of penicillin by Alexander Fleming in 1928 established a foundation for the development of β-lactam antimicrobial therapy. Subsequent advances produced several penicillin derivatives with distinct antibacterial spectra, pharmacological properties, and resistance profiles. Examples include penicillin G, penicillin V, amoxicillin, ampicillin, oxacillin, and piperacillin. Structural modifications have enabled the development of agents with improved acid stability, broader activity against selected bacterial groups, or greater resistance to particular β-lactamases.
Despite their clinical importance, penicillins face challenges arising from bacterial resistance. Resistance mechanisms include β-lactamase-mediated hydrolysis of the β-lactam ring, alterations in PBPs that reduce drug affinity, and decreased antibiotic penetration. These adaptations can diminish therapeutic effectiveness and complicate the management of bacterial infections.
Source of penicillin
Penicillins are β-lactam antibiotics originally obtained from fungi belonging to the genus Penicillium. Their discovery established the foundation for the development of antibiotics used to treat a wide range of bacterial infections. Although early penicillin preparations were extracted directly from fungal cultures, modern production relies on controlled fermentation, strain improvement, and chemical modification to obtain compounds with specific pharmaceutical properties.
The principal industrial source of natural penicillin is Penicillium chrysogenum, historically associated with the production of substantial quantities of penicillin during fermentation. The species Penicillium notatum is also historically significant because of its association with Alexander Fleming’s discovery of penicillin in 1928. In contemporary fungal taxonomy, the industrial production organism is commonly identified as Penicillium rubens, a species closely related to and historically classified under P. chrysogenum. These fungi synthesize penicillin as a secondary metabolite during cultivation under suitable environmental and nutritional conditions.
Production of natural penicillins
Natural penicillins are produced through microbial fermentation, a process in which selected fungal strains are cultivated in nutrient-rich media under carefully regulated conditions. Industrial fermentation involves controlling parameters such as temperature, pH, aeration, agitation, and nutrient availability to promote fungal growth and penicillin biosynthesis. Carbon sources, including lactose or other suitable carbohydrates, provide energy, while precursor molecules influence the type of penicillin produced.
Penicillin G (benzylpenicillin) and penicillin V (phenoxymethylpenicillin) are important examples of naturally derived penicillins. Penicillin G production is associated with the availability of phenylacetic acid as a precursor, whereas phenoxyacetic acid can be supplied to support penicillin V formation. Following fermentation, the antibiotic is recovered from the culture broth through extraction, purification, and crystallization or other appropriate processing techniques. These procedures remove fungal biomass, residual nutrients, and unwanted metabolites, yielding a product suitable for pharmaceutical formulation.
Formation of semisynthetic penicillins
The development of semisynthetic penicillins expanded the therapeutic applications of the original compounds. These antibiotics are prepared by chemically modifying the penicillin nucleus obtained from fermentation-derived intermediates. A central intermediate is 6-aminopenicillanic acid (6-APA), which contains the characteristic β-lactam ring fused to a thiazolidine ring. This molecular framework is responsible for the principal antibacterial activity of penicillins.
During semisynthetic production, the naturally occurring side chain is removed to obtain 6-APA. A selected acyl side chain is then attached through chemical or enzymatic processes. Changes to this side chain can influence antibacterial spectrum, acid stability, resistance to certain β-lactamases, and pharmacokinetic characteristics.
Examples of semisynthetic penicillins include ampicillin, amoxicillin, oxacillin, methicillin, and cloxacillin. Ampicillin and amoxicillin possess activity against selected Gram-positive and Gram-negative bacteria, while oxacillin and cloxacillin were developed to resist certain staphylococcal penicillinases. Methicillin is historically important in the development of penicillinase-resistant agents, although it is no longer routinely used in clinical practice in many countries.
The production of penicillins illustrates how microbial biosynthesis and chemical engineering can be combined to improve antimicrobial medicines. Natural fermentation provides the essential molecular framework, while subsequent modification generates compounds with distinct properties. This approach has enabled the pharmaceutical industry to develop penicillins suited to different clinical requirements, although their effectiveness remains dependent on bacterial susceptibility, appropriate prescribing, and the responsible use of antibiotics.
Structure of penicillin
The fundamental structural framework of penicillins is 6-aminopenicillanic acid (6-APA), which constitutes the core nucleus of this important class of β-lactam antibiotics. This nucleus comprises three principal structural features: a β-lactam ring, a thiazolidine ring, and an amino-containing side-chain attachment site. The distinctive arrangement of these components determines the chemical stability, antibacterial properties, and susceptibility to enzymatic degradation of penicillin derivatives. Modifications to the side chain have facilitated the development of numerous semisynthetic penicillins with different pharmacological characteristics and antibacterial spectra.
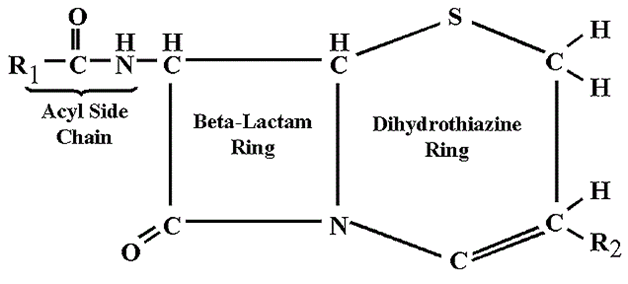
The β-lactam ring is a four-membered cyclic amide that plays a central role in the antibacterial mechanism of penicillins (Figure 1). Its structural strain and characteristic chemical reactivity enable penicillins to interact with penicillin-binding proteins (PBPs), particularly the enzymes responsible for the final stages of bacterial peptidoglycan synthesis. By inhibiting these enzymes, penicillins prevent effective cross-linking of the peptidoglycan network, thereby compromising bacterial cell wall integrity. This disruption can lead to cell lysis, particularly in actively growing and susceptible bacteria. The intact β-lactam ring is indispensable for the biological activity of penicillins.
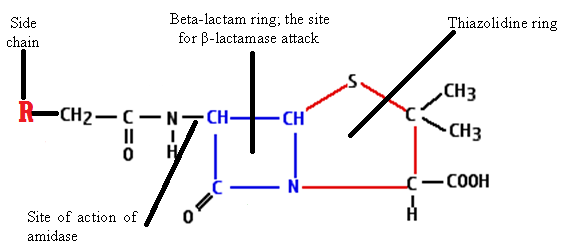
The thiazolidine ring, a five-membered heterocyclic structure containing sulfur and nitrogen, is fused to the β-lactam ring. This fused-ring configuration contributes to the characteristic three-dimensional architecture of the penicillin nucleus and influences its chemical reactivity and interaction with bacterial targets. The integrity of the fused-ring system is essential for maintaining the molecular configuration required for effective antibacterial action. Structural alterations that disrupt this arrangement can substantially diminish or abolish antimicrobial activity.
The side chain attached to the 6-APA nucleus provides an important site for chemical modification. Differences in side-chain composition influence several properties, including acid stability, resistance to β-lactamase enzymes, absorption, distribution, and antibacterial spectrum. For example, ampicillin and amoxicillin exhibit activity against selected Gram-positive and Gram-negative bacteria, whereas methicillin was historically developed to resist certain staphylococcal penicillinases. These differences demonstrate how modifications to the side chain can alter the performance of penicillins without eliminating their shared β-lactam pharmacophore.
Despite these structural adaptations, penicillins remain vulnerable to hydrolysis of the β-lactam ring by bacterial β-lactamases, enzymes that constitute an important mechanism of antimicrobial resistance. These enzymes catalyse the opening of the β-lactam ring, converting susceptible penicillins into penicilloic acid derivatives that lack the characteristic antibacterial activity of the intact parent compounds. Ring hydrolysis prevents effective engagement with PBPs and consequently interrupts the antibiotic’s ability to inhibit cell wall synthesis.
The biological effectiveness of penicillins depends on the preservation of their core molecular architecture, particularly the intact β-lactam ring and fused thiazolidine system. At the same time, side-chain engineering provides opportunities to improve specific chemical and pharmacological properties.
Clinical application of penicillin
Penicillins are a major group of β-lactam antibiotics employed in the treatment of susceptible bacterial infections. Their clinical utility arises from their ability to interfere with bacterial cell-wall biosynthesis, thereby compromising structural integrity and promoting bacterial death. Their therapeutic application depends on the infecting organism, its antimicrobial susceptibility, the site of infection, and the pharmacological properties of the selected compound. Individual penicillins differ in their clinical indications, antibacterial spectrum, routes of administration, and capacity to withstand bacterial resistance mechanisms.
Benzylpenicillin, also known as penicillin G, is administered primarily by injection because it is susceptible to degradation under acidic gastric conditions. It remains useful against susceptible Gram-positive bacteria, including several species of Streptococcus, as well as selected Gram-negative organisms, anaerobic bacteria, and spirochaetes. Depending on the clinical indication and susceptibility profile, penicillin G may be used in the treatment of syphilis, certain streptococcal infections, and selected clostridial infections. Its effectiveness against staphylococci is limited by the widespread production of penicillinase, an enzyme that inactivates the drug. Microbiological identification and susceptibility testing are important when selecting penicillin G for infections caused by potentially resistant organisms.
Phenoxymethylpenicillin, commonly called penicillin V, possesses greater acid stability than penicillin G, making oral administration feasible. It is principally used for susceptible Gram-positive infections, particularly selected streptococcal infections involving the throat, skin, and other tissues. Its suitability for outpatient treatment can reduce the need for parenteral administration when the infection is mild or otherwise appropriate for oral therapy. Nevertheless, penicillin V is not a universal treatment for bacterial disease, and its use should reflect the suspected pathogen, infection severity, and established clinical guidance.
The development of semisynthetic penicillins expanded the therapeutic possibilities of this antibiotic class. Chemical modification of the penicillin nucleus, particularly its side chain, produced compounds with altered antibacterial spectra, improved pharmacokinetic characteristics, or greater resistance to particular bacterial enzymes. Aminopenicillins, including ampicillin and amoxicillin, demonstrate activity against a broader range of organisms than natural penicillins.
They are used in selected respiratory, urinary, gastrointestinal, and other infections when the causative bacteria are susceptible. Resistance among organisms such as Escherichia coli and Klebsiella species can substantially limit their effectiveness. Amoxicillin is also commonly prescribed for certain ear infections and susceptible respiratory infections, while ampicillin has specific applications in conditions such as susceptible enterococcal infections and selected cases of listeriosis.
Antipseudomonal penicillins, including piperacillin and the historically used ticarcillin, were developed to address selected Gram-negative pathogens that are poorly covered by natural penicillins. Piperacillin, frequently administered with tazobactam, is used in hospital settings for serious infections when broader antibacterial coverage is required. These agents may be considered for susceptible Pseudomonas aeruginosa and other relevant Gram-negative organisms. Their clinical selection depends on local resistance patterns, infection source, severity, and microbiological findings. No penicillin reliably covers every Gram-negative bacterium, and resistance can occur even among organisms traditionally considered susceptible.
Another important development in penicillin therapy is the combination of selected antibiotics with β-lactamase inhibitors. Bacterial β-lactamase enzymes hydrolyse the β-lactam ring, reducing or abolishing the activity of susceptible antibiotics. Clavulanic acid, sulbactam, and tazobactam inhibit certain β-lactamases and can therefore protect an accompanying antibiotic from enzymatic destruction. Amoxicillin-clavulanate, marketed under the brand name Augmentin, is an established example used for selected infections involving susceptible β-lactamase-producing bacteria. Clavulanic acid is not used as an effective standalone antibacterial treatment; its principal role is to restore or extend the activity of amoxicillin against susceptible enzyme-producing organisms.
These combinations do not overcome every resistance mechanism, including all forms of altered penicillin-binding proteins or β-lactamase activity. The clinical application of penicillins requires rational antimicrobial selection rather than indiscriminate prescribing. Appropriate dosing, consideration of allergy history, assessment of renal function where relevant, and timely review of culture and susceptibility results help optimize treatment. Using the narrowest effective agent for the appropriate duration supports therapeutic success while reducing adverse effects and unnecessary selection pressure for antimicrobial resistance.
Spectrum of activity of penicillins
Penicillins are β-lactam antibiotics whose antibacterial activity varies according to their chemical structure, ability to penetrate bacterial envelopes, affinity for target proteins, and susceptibility to bacterial resistance mechanisms. Their spectrum of activity describes the range of bacterial species against which a particular penicillin can exert an inhibitory or bactericidal effect. Differences in this spectrum determine the clinical applications of individual penicillins and influence their selection for treating bacterial infections.
The differences in susceptibility between Gram-positive and Gram-negative bacteria are partly explained by their cell-envelope architecture. Gram-positive bacteria possess a relatively thick peptidoglycan layer outside the cytoplasmic membrane, whereas Gram-negative bacteria have a thinner peptidoglycan layer located within the periplasmic space between the inner membrane and an additional outer membrane. This outer membrane functions as a selective permeability barrier, restricting the entry of various antimicrobial agents. Some penicillins, including natural penicillin G (benzylpenicillin), have limited activity against many Gram-negative organisms because their access to the relevant target proteins may be restricted.
Penicillins exert their antibacterial effects by binding to penicillin-binding proteins (PBPs). PBPs are enzymes involved in the final stages of peptidoglycan synthesis and cross-linking. Interference with these enzymes weakens the bacterial cell wall and compromises its structural integrity. Actively growing bacteria are especially susceptible because they continuously synthesize and remodel their cell walls. Under suitable conditions, this disruption leads to cell lysis and bacterial death. Penicillins are generally classified as bactericidal rather than bacteriostatic antibiotics, although their effectiveness depends on the bacterial species, drug concentration, growth conditions, and resistance profile.
Natural penicillins, such as penicillin G and penicillin V, possess a relatively narrow spectrum of activity. They are particularly effective against susceptible Gram-positive organisms, including certain streptococci, as well as selected Gram-positive anaerobes and other susceptible bacteria. Penicillin G is also an established treatment for specific infections caused by susceptible organisms, including syphilis caused by Treponema pallidum. Their activity against many Gram-negative bacteria is limited, and penicillinase-producing organisms may inactivate these drugs through enzymatic hydrolysis of the β-lactam ring.
Penicillinase-resistant penicillins, including oxacillin, nafcillin, and dicloxacillin, were developed to withstand certain staphylococcal β-lactamases. Their principal application is the treatment of infections caused by susceptible methicillin-sensitive Staphylococcus aureus (MSSA). Despite their improved resistance to these enzymes, their antibacterial spectrum remains relatively narrow. Methicillin resistance in S. aureus is generally associated with altered penicillin-binding protein activity, particularly the production of PBP2a, rather than simply increased β-lactamase production. Methicillin-resistant S. aureus (MRSA) is resistant to most conventional β-lactam antibiotics, including the antistaphylococcal penicillins.
Aminopenicillins, such as ampicillin and amoxicillin, exhibit an expanded spectrum compared with natural penicillins. Their structural modifications improve activity against certain Gram-negative bacteria, including susceptible strains of Haemophilus influenzae, Escherichia coli, and Proteus mirabilis. Their effectiveness is frequently reduced by β-lactamase production and other resistance mechanisms. Combining an aminopenicillin with a β-lactamase inhibitor, such as clavulanic acid, can restore activity against selected β-lactamase-producing bacteria, although this combination does not overcome every mechanism of resistance.
Antipseudomonal penicillins, including piperacillin and the older agent ticarcillin, possess activity against a broader range of Gram-negative organisms, including susceptible strains of Pseudomonas aeruginosa. Piperacillin is commonly administered with tazobactam to extend its usefulness against certain β-lactamase-producing bacteria. Neither an expanded spectrum nor the presence of a β-lactamase inhibitor guarantees activity against resistant isolates.
The spectrum of activity of penicillins reflects the interaction between antibiotic structure, bacterial envelope permeability, target-protein affinity, and resistance determinants. Distinguishing narrow-spectrum, penicillinase-resistant, aminopenicillin, and antipseudomonal agents provides a practical framework for understanding their antibacterial coverage. Appropriate selection should be guided by the suspected pathogen, infection site, local resistance patterns, and microbiological susceptibility results whenever available.
Mechanism or mode of action of penicillin
Penicillins exert their antibacterial activity primarily by disrupting the biosynthesis and structural integrity of the bacterial cell wall. As members of the β-lactam class of antibiotics, they interfere with the final stages of peptidoglycan assembly, a process essential for maintaining bacterial shape, mechanical strength, and resistance to osmotic pressure. Their activity is most pronounced against susceptible bacteria undergoing active growth and cell division, when continuous cell wall synthesis is required. Penicillins are generally ineffective against wall-less microorganisms, such as Mycoplasma species, which lack the peptidoglycan structure targeted by these drugs.
The principal molecular targets of penicillins are PBPs, a group of bacterial enzymes associated with the cytoplasmic membrane. These proteins participate in the construction, maturation, and remodelling of the peptidoglycan network. Among their major functions are transpeptidation and other reactions required for the formation of a stable cell wall. Transpeptidase enzymes are particularly important because they catalyse the cross-linking of adjacent peptidoglycan peptide chains, thereby transforming the newly assembled cell wall into a mechanically resilient structure capable of withstanding internal osmotic pressure.
Following administration and access to susceptible bacteria, penicillins interact with their target PBPs. Their characteristic β-lactam ring reacts with the active-site serine residue of susceptible transpeptidases, forming a stable covalent acyl-enzyme complex. This interaction effectively inactivates the enzyme and prevents it from completing the cross-linking reactions necessary for normal peptidoglycan maturation. Although the precise affinity of penicillins varies among different PBPs and bacterial species, inhibition of essential cell wall-synthesising enzymes represents the central mechanism underlying their antibacterial effect.
When transpeptidation is disrupted, newly produced peptidoglycan cannot acquire its normal degree of cross-linking. The resulting cell wall becomes structurally defective and increasingly unable to maintain bacterial integrity during growth and division. At the same time, the normal balance between cell wall construction and degradation is disturbed. Endogenous bacterial autolysins, which participate in physiological cell wall remodelling, may continue to act even when effective wall synthesis has been inhibited. This imbalance can accelerate structural deterioration and contribute to bacterial lysis.
The consequences of cell wall damage are particularly significant because bacterial cytoplasm maintains a high internal osmotic pressure relative to the surrounding environment. Under normal conditions, the peptidoglycan layer counteracts this pressure and prevents uncontrolled cellular expansion. When the protective wall is weakened, the bacterial envelope may no longer withstand the resulting mechanical stress. Depending on the organism and environmental conditions, the cell may undergo swelling, membrane disruption, and eventual lysis, leading to the loss of viability.
Penicillins are therefore classified as bactericidal antibiotics because they kill susceptible bacteria rather than merely suppressing their multiplication. Their killing activity depends on several factors, including bacterial growth rate, drug concentration, the susceptibility of target PBPs, and the organism’s capacity to maintain or repair its cell wall. Slowly growing or metabolically inactive bacteria may exhibit reduced susceptibility because they have less active peptidoglycan synthesis. This growth dependence also explains why penicillins generally demonstrate limited activity against bacteria that are not actively constructing their cell walls.
The antibacterial action of penicillins involves selective inhibition of essential PBPs, interruption of peptidoglycan cross-linking, disruption of cell wall homeostasis, and subsequent loss of bacterial structural integrity. By targeting a fundamental feature of bacterial physiology that is absent from human cells, penicillins achieve selective toxicity against susceptible microorganisms. The development of β-lactamase enzymes, alterations in PBPs, and changes in bacterial permeability can reduce drug effectiveness and contribute to antimicrobial resistance.
Bacterial resistance to penicillin
Bacterial resistance to penicillin is a significant challenge in antimicrobial chemotherapy, arising from the capacity of pathogenic microorganisms to modify or circumvent the drug’s antibacterial activity. One major mechanism involves the production of β-lactamase enzymes. These enzymes hydrolyse the β-lactam ring of penicillins derived from 6-aminopenicillanic acid, thereby disrupting the structural integrity required for antibacterial activity. This enzymatic degradation reduces drug efficacy and may render conventional penicillin therapy ineffective against susceptible bacterial populations that have acquired resistance determinants.
Another mechanism involves alterations in PBPs, which serve as essential enzymes in bacterial peptidoglycan synthesis. Penicillins normally bind to these proteins and inhibit the cross-linking of peptidoglycan strands, weakening the bacterial cell wall and ultimately promoting cell lysis. However, mutations or the acquisition of genes encoding modified PBPs can reduce the affinity of these targets for β-lactam antibiotics. Bacterial cell-wall synthesis may continue despite the presence of therapeutically relevant drug concentrations.
The dissemination of resistance genes through mobile genetic elements further accelerates the emergence of penicillin-resistant bacteria. Plasmids, transposons, and integrons can facilitate the acquisition and spread of β-lactamase genes among bacterial populations. Of particular clinical importance are extended-spectrum β-lactamases (ESBLs), which hydrolyse penicillins and many extended-spectrum cephalosporins. Although ESBLs are frequently associated with Gram-negative organisms, including Escherichia coli and Klebsiella pneumoniae, their distribution varies among bacterial species and clinical settings. Some resistant organisms also produce AmpC β-lactamases or carbapenemases such as the metallo beta lactamases (MBLs), which expand the range of β-lactam agents affected.
Reduced antibiotic accumulation constitutes another resistance pathway, particularly among Gram-negative bacteria. Changes in outer-membrane porins can restrict antibiotic entry, while multidrug efflux pumps actively expel antimicrobial compounds from bacterial cells. When these mechanisms occur alongside β-lactamase production, they can substantially increase resistance by reducing the concentration of active antibiotic reaching its target.
Historically, methicillin was introduced as a penicillinase-resistant penicillin to address infections caused by β-lactamase-producing staphylococci. Nevertheless, methicillin-resistant Staphylococcus aureus (MRSA) emerged through the acquisition of the mecA gene, or less commonly mecC, which encodes an altered penicillin-binding protein with reduced affinity for most conventional β-lactam antibiotics. Oxacillin and nafcillin remain important antistaphylococcal penicillins for susceptible strains, but they are generally ineffective against MRSA.
Pharmacokinetics of penicillin
The pharmacokinetic properties of penicillins determine how these antimicrobial agents enter the systemic circulation, reach infected tissues, undergo biotransformation, and are eliminated from the body. Their pharmacokinetic behavior varies according to the specific penicillin compound, formulation, route of administration, and physiological condition of the patient. Penicillin pharmacokinetics depend on the interaction between absorption, distribution, metabolism, and renal elimination, which collectively determine the duration and intensity of antimicrobial exposure.
Absorption: The gastrointestinal absorption of penicillins differs considerably among individual agents. Some compounds, such as penicillin G, are acid-labile and may undergo degradation in the acidic environment of the stomach, resulting in reduced oral bioavailability. Penicillin V and aminopenicillins, including amoxicillin, demonstrate greater suitability for oral administration. Parenteral administration bypasses gastrointestinal absorption barriers and provides more predictable systemic drug exposure. Intravenous administration delivers the drug directly into the bloodstream, achieving immediate systemic availability, whereas intramuscular injection allows absorption from the injection site into the circulation. The rate and extent of absorption therefore depend on the drug’s physicochemical characteristics and the selected formulation.
Distribution: Following absorption, penicillins are transported through the bloodstream and distributed into various extracellular fluids and tissues. Their relatively hydrophilic nature facilitates distribution within extracellular compartments, although penetration into certain anatomical sites may be limited. Entry into cerebrospinal fluid is generally restricted under normal physiological conditions but may increase when the meninges become inflamed. Penicillin concentrations in tissues depend on factors such as vascular perfusion, capillary permeability, protein binding, and the integrity of biological barriers. Most penicillins exhibit relatively low to moderate plasma protein binding, although the degree varies among individual compounds. Differences in tissue penetration may influence their effectiveness against infections occurring in specific body compartments.
Metabolism: Penicillins generally undergo limited hepatic metabolism, with a substantial proportion of many compounds remaining chemically unchanged during elimination. However, metabolic pathways differ among individual agents, and some penicillins may undergo partial transformation before excretion. Their overall pharmacokinetic profiles are therefore influenced more strongly by renal clearance than by extensive hepatic biotransformation.
Excretion: The kidneys represent the principal elimination route for most penicillins. Renal clearance occurs through glomerular filtration and active tubular secretion, enabling the removal of circulating drug into the urine. This efficient elimination contributes to relatively short plasma half-lives for many preparations. In patients with impaired renal function, reduced clearance may prolong drug exposure and necessitate dosage adjustment. Certain formulations, such as benzathine penicillin G and procaine penicillin G, release the active compound gradually from intramuscular injection sites, producing prolonged therapeutic concentrations.
Side effect / toxicity of penicillin
Penicillins are widely used antibacterial agents characterized by a generally favorable safety profile when administered at appropriate doses. Their selective action against bacterial cell wall synthesis contributes to their relatively low toxicity in human cells. However, their use may be associated with adverse drug reactions ranging from mild gastrointestinal disturbances to severe, potentially life-threatening hypersensitivity responses. The occurrence and severity of these effects depend on individual susceptibility, dosage, route of administration, renal function, and the specific penicillin prescribed.
One of the most clinically significant adverse effects of penicillin therapy is hypersensitivity. In susceptible individuals, exposure to the drug may trigger immune-mediated reactions, including immediate responses associated with immunoglobulin E (IgE). These reactions may develop rapidly after administration and can manifest as urticaria, itching, facial swelling, wheezing, or respiratory difficulty. In severe cases, anaphylaxis may occur, resulting in airway obstruction, hypotension, circulatory collapse, and, without prompt treatment, death. Although anaphylaxis is uncommon, it represents a major safety concern and requires immediate medical intervention.
Cutaneous manifestations are among the frequently recognized reactions associated with penicillin administration. Patients may develop erythematous maculopapular eruptions, localized itching, or widespread skin rashes. Some delayed reactions arise through immune mechanisms that do not involve IgE. Not every rash occurring during penicillin therapy indicates an immediate-type allergic response. Nevertheless, suspected drug hypersensitivity requires appropriate clinical assessment to determine whether treatment should be discontinued and whether future exposure should be avoided.
Gastrointestinal disturbances may also accompany penicillin treatment, particularly following oral administration. Nausea, abdominal discomfort, and mild diarrhea can occur because of alterations in the normal intestinal microbiota. In some patients, antibiotic-associated diarrhea may become severe and require further investigation, including assessment for Clostridioides difficile infection. The risk varies according to the antimicrobial agent, duration of treatment, and individual patient characteristics.
Other adverse effects may occur under specific clinical circumstances. High doses of certain penicillins, particularly in patients with impaired renal function, can increase the risk of neurological toxicity, including confusion, myoclonus, and seizures. Renal impairment may also delay drug elimination, thereby increasing systemic exposure. In addition, uncommon hematological, hepatic, and renal abnormalities have been reported with particular agents, especially during prolonged treatment.
Fatal outcomes associated with penicillin toxicity are rare but may occur, most notably during severe anaphylactic reactions. Appropriate patient assessment, accurate dosing, monitoring for adverse symptoms, and timely recognition of hypersensitivity are therefore essential. Penicillins remain important therapeutic agents, and their benefits generally outweigh their risks when prescribed judiciously and administered under appropriate clinical supervision.
References
Baldwin, J. E., & Abraham, E. (1988). The biosynthesis of penicillins and cephalosporins. Natural Product Reports, 5, 129–145.
Ball, A. P., Gray, J. A., & Murdoch, J. M. (1978). The natural penicillins—Benzylpenicillin (penicillin G) and phenoxymethylpenicillin (penicillin V). In Antibacterial drugs today. Springer.
Bubna, A. K. (2025). Penicillins. In Therapeutics in dermatology: Essentials for clinical practice. Springer.
Campbell, B. A., & Cox, S. M. (1992). The penicillins. Obstetrics and Gynecology Clinics of North America, 19(3), 435–447.
Clarke, H. T., Johnson, J. R., & Robinson, R. (Eds.). (1949). Chemistry of penicillin. Princeton University Press.
Gaynes, R. (2017). The discovery of penicillin—New insights after more than 75 years of clinical use. Emerging Infectious Diseases, 23(5), 849–853.
Lobanovska, M., & Pilla, G. (2017). Penicillin’s discovery and antibiotic resistance: Lessons for the future? The Yale Journal of Biology and Medicine, 90(1), 135–145.
Raynor, B. D. (1997). Penicillin and ampicillin. Primary Care Update for OB/GYNS, 4(4), 147–152.
Wright, A. J., & Wilkowske, C. J. (1991). The penicillins. Mayo Clinic Proceedings, 66(10), 1047–1063.
Axelsen P. H (2002). Essentials of Antimicrobial Pharmacology. Humana Press, Totowa, NJ.
Beck R.W (2000). A chronology of microbiology in historical context. Washington, D.C.: ASM Press.
Chung K.T, Stevens Jr., S.E and Ferris D.H (1995). A chronology of events and pioneers of microbiology. SIM News, 45(1):3–13.
Denyer S.P., Hodges N.A and Gorman S.P (2004). Hugo & Russell’s Pharmaceutical Microbiology. 7th ed. Blackwell Publishing Company, USA. Pp.152-172.
Finch R.G, Greenwood D, Norrby R and Whitley R (2002). Antibiotic and chemotherapy, 8th edition. Churchill Livingstone, London and Edinburg.
Discover more from Microbiology Class
Subscribe to get the latest posts sent to your email.