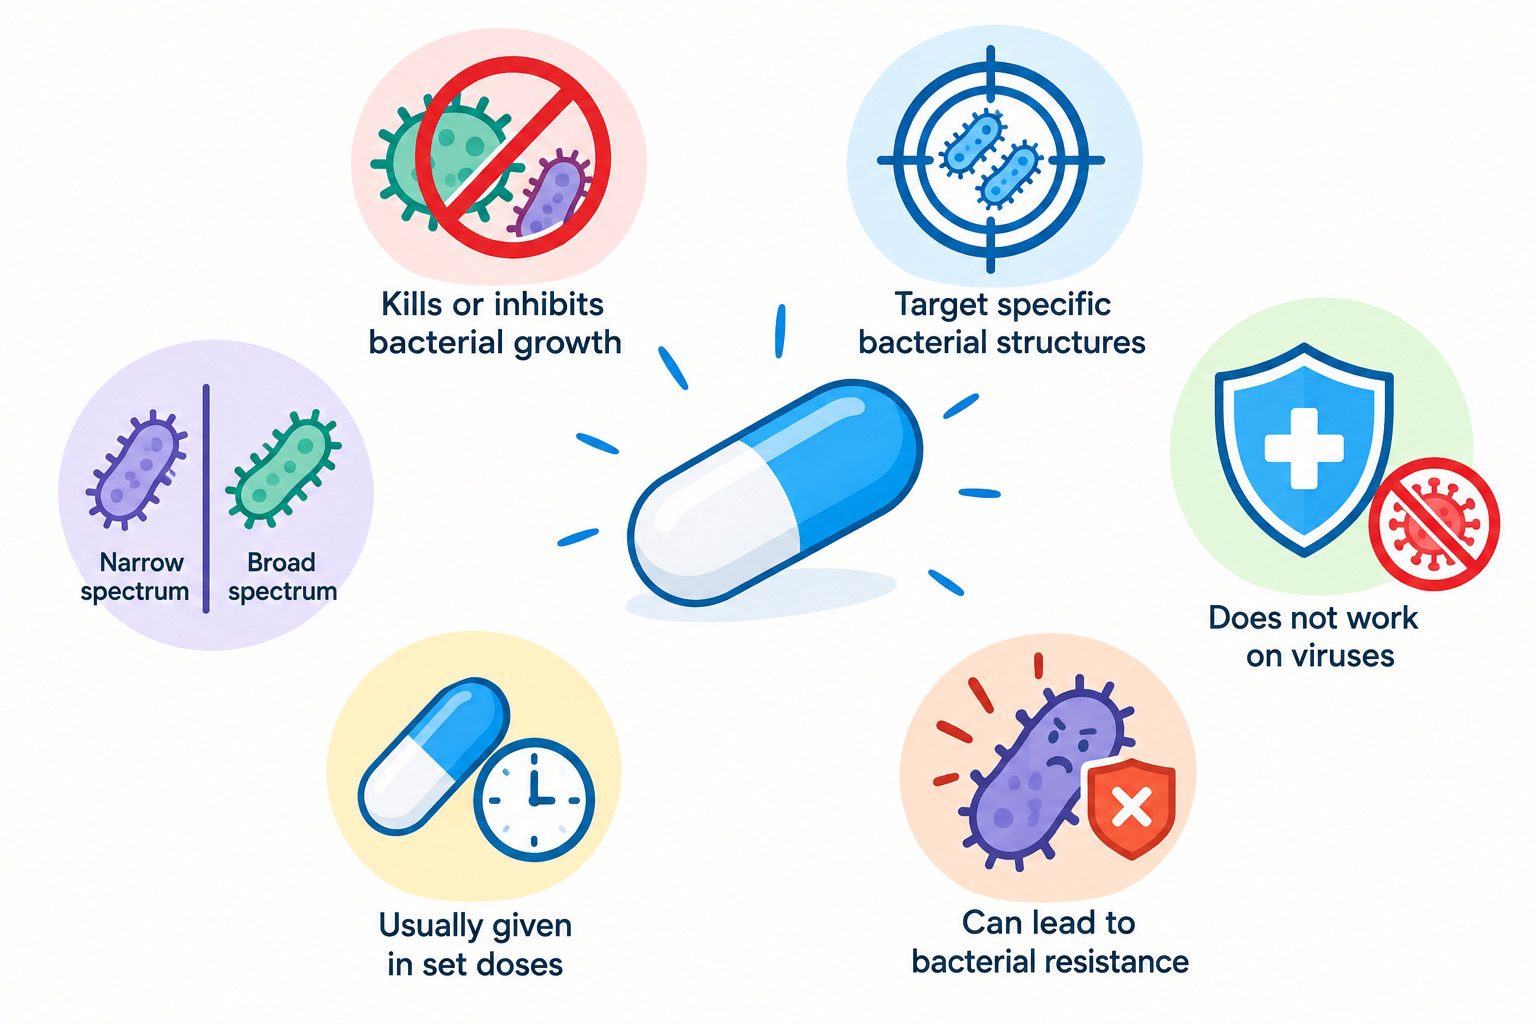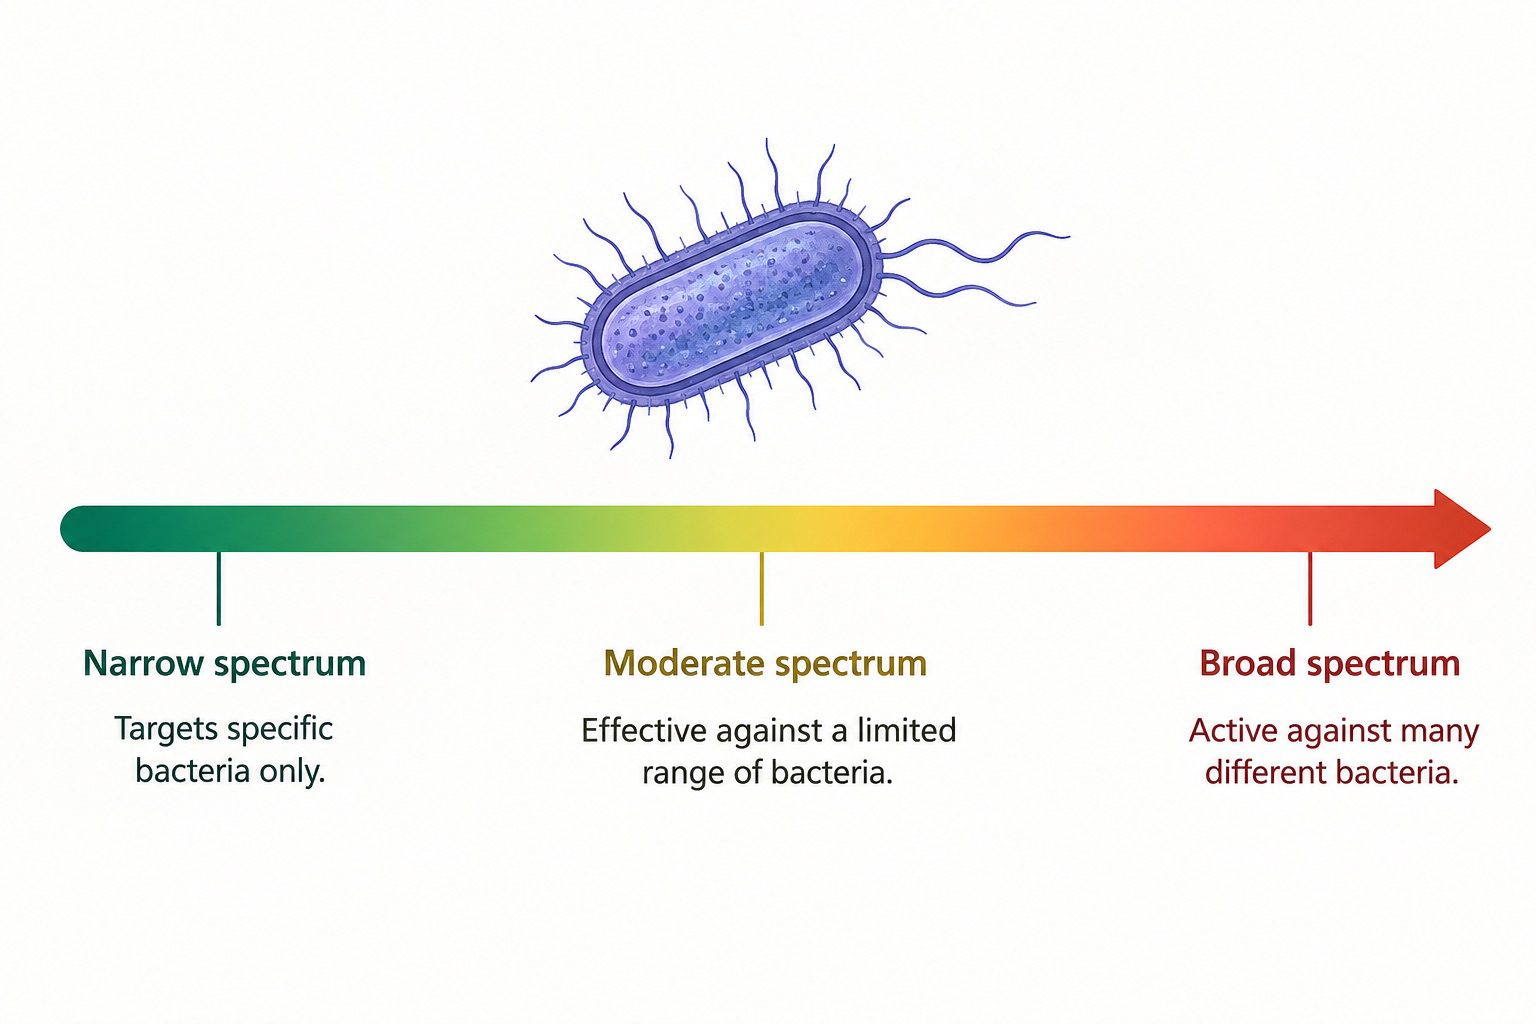
The spectrum of activity is a fundamental pharmacological characteristic that describes the range of bacterial microorganisms susceptible to the inhibitory or lethal effects of an antibacterial agent. Rather than representing a simple classification of drugs, the spectrum provides an important indication of how broadly or selectively a drug can act across different bacterial populations. Each antibacterial agent possesses a characteristic pattern of activity that is influenced by its molecular structure, mechanism of action, ability to reach its cellular target, and the biological characteristics of the organisms encountered.
Antibacterial agents differ considerably in the number and types of organisms they can affect. Some agents demonstrate activity against a relatively restricted group of bacteria and are consequently described as narrow-spectrum agents. These drugs may be particularly useful when the causative pathogen has been identified because treatment can be directed toward the specific organism without unnecessarily affecting unrelated bacterial populations. In contrast, broad-spectrum agents are capable of acting against a wider range of bacterial species, potentially including organisms with substantially different structural and physiological characteristics.
Between these categories are agents with an intermediate or extended spectrum, whose activity encompasses additional bacterial groups beyond their original range. The spectrum of an antibacterial agent is closely related to the structural diversity of bacteria. Differences in cell-wall composition, outer-membrane characteristics, ribosomal structure, metabolic pathways, and membrane permeability can determine whether a particular drug can reach and interact effectively with its target. An antibacterial agent that is highly effective against one bacterial group may demonstrate little or no activity against another. These differences also explain why antibacterial therapy cannot be selected solely on the basis of the general class to which a drug belongs.
The practical significance of spectrum extends beyond identifying whether a microorganism is susceptible to a drug. The breadth of antibacterial activity can influence the composition of the patient’s normal microbiota and may affect the likelihood of adverse ecological consequences, including disruption of protective bacterial populations and selection of resistant organisms. Broad activity can therefore be advantageous when the causative pathogen is unknown or when infections may involve multiple bacterial species, but unnecessary use of broad-spectrum therapy can increase selective pressure for antimicrobial resistance.
In contemporary antimicrobial therapy, the spectrum of activity is considered alongside microbiological evidence, site of infection, drug distribution, patient-specific factors, and the susceptibility profile of the pathogen. Initial treatment may sometimes require an agent with sufficient breadth to cover likely pathogens, particularly before laboratory identification is available. Once the causative organism and its susceptibility pattern are established, therapy can often be refined toward a more targeted antibacterial agent.
The spectrum of activity represents a bridge between the biological characteristics of bacteria and the pharmacological selection of antibacterial therapy. A clear understanding of this concept supports rational antimicrobial use by helping clinicians balance adequate pathogen coverage with preservation of the normal microbiological environment and reduction of unnecessary antimicrobial exposure.
Antimicrobial targets and the spectrum of activity of antibiotics
The growth and multiplication of pathogenic microorganisms depend on a coordinated series of biochemical and cellular processes. During active growth, microorganisms synthesize essential macromolecules, including DNA, RNA, proteins, lipids, and structural components of the cell envelope, while simultaneously acquiring nutrients and energy from their surrounding environment. These processes occur during microbial proliferation both in vivo, within a host, and in vitro, under laboratory or experimental conditions. Because the survival and replication of microorganisms depend on these fundamental processes, they provide important targets for antimicrobial therapy.
Antimicrobial agents are designed to interfere selectively with structures or metabolic pathways that are essential for the survival, growth, or reproduction of infectious microorganisms (Figure 1). Depending on the nature of the drug and its target, antimicrobial activity may result from inhibition of cell-wall formation, disruption of cell-membrane integrity, interference with nucleic-acid synthesis, inhibition of protein production, or alteration of essential metabolic pathways. The effectiveness of an antimicrobial agent therefore depends not only on its ability to reach the infectious organism but also on the presence and accessibility of an appropriate cellular target.
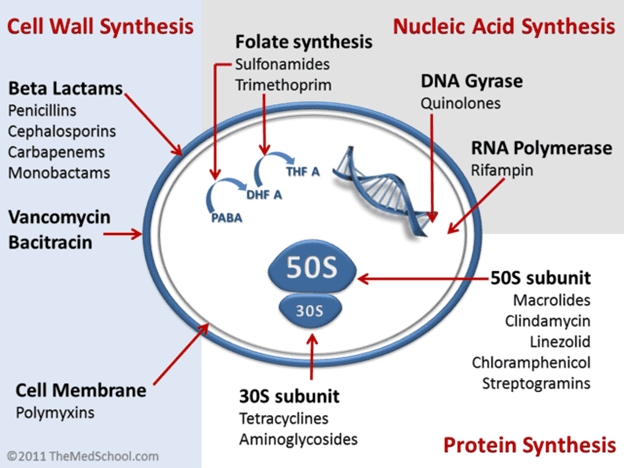
Different groups of microorganisms possess substantial biological and structural differences, which influence their susceptibility to antimicrobial agents. For example, bacteria possess distinctive cell-wall structures and ribosomal systems that can be selectively targeted by antibacterial drugs. Fungi have different membrane and cell-wall components, while viruses depend extensively on host-cell machinery for replication and consequently require antiviral agents directed toward specific stages of the viral life cycle. Protozoa similarly possess unique metabolic and cellular characteristics that provide potential targets for antiprotozoal therapy. An antimicrobial agent effective against one class of pathogen may have little or no activity against another.
An important pharmacological characteristic arising from these differences is the spectrum of activity. The spectrum of an antimicrobial agent refers to the range of pathogenic microorganisms against which the agent demonstrates clinically relevant inhibitory or lethal activity. It provides an indication of the breadth of microbial coverage offered by a particular drug and is an important consideration when selecting therapy for an infectious disease.
As aforesaid, antimicrobial agents are commonly categorized according to their spectrum as narrow-spectrum or broad-spectrum agents. Narrow-spectrum drugs primarily act against a limited group of microorganisms, making them particularly useful when the causative pathogen has been identified and its susceptibility is established. Broad-spectrum agents, in contrast, possess activity against a wider variety of microorganisms and may be useful when the specific pathogen is initially unknown or when an infection is suspected to involve multiple bacterial species.
The spectrum of activity is therefore an important bridge between the mechanism of antimicrobial action, microbial susceptibility, and therapeutic decision-making. Appropriate selection of antimicrobial therapy requires sufficient coverage of the likely pathogen while avoiding unnecessary exposure to agents with excessively broad activity. Such an approach supports effective treatment, minimizes disruption of the normal microbiota, and contributes to the responsible use of antimicrobial drugs.
Narrow-spectrum antibacterial agents
Narrow-spectrum antibacterial agents are antimicrobial drugs that demonstrate activity against a relatively restricted group of bacterial microorganisms. Unlike broad-spectrum agents, which can inhibit a wide variety of bacterial species, narrow-spectrum drugs are designed or naturally suited to act against particular bacterial groups or specific pathogens. Their selective activity makes them especially valuable when the causative organism has been identified through clinical assessment, culture, and antimicrobial susceptibility testing.
The principal advantage of narrow-spectrum therapy is microbial selectivity. By concentrating antibacterial activity on the suspected or confirmed pathogen, these agents generally exert less pressure on unrelated microorganisms that constitute the body’s normal microbiota. Preservation of the normal microbial population is clinically important because excessive disruption of commensal bacteria can contribute to complications such as secondary infections, gastrointestinal disturbances, and colonization by opportunistic organisms. Narrow-spectrum treatment is an important component of rational antimicrobial use.
The antibacterial effect of these agents depends on their specific molecular targets. Some interfere with bacterial cell-wall synthesis, whereas others inhibit protein synthesis, nucleic-acid metabolism, or other essential cellular processes. For example, penicillin G has strong activity against susceptible Gram-positive organisms and selected Gram-negative bacteria. It interferes with bacterial cell-wall formation by binding to penicillin-binding proteins and preventing the final stages of peptidoglycan synthesis. This ultimately compromises the structural integrity of actively growing bacterial cells.
Vancomycin represents another clinically important antibacterial agent with a comparatively focused spectrum. It primarily targets Gram-positive bacteria and inhibits cell-wall synthesis through a mechanism distinct from that of β-lactam antibiotics. Because vancomycin has limited activity against Gram-negative organisms, largely because of their outer membrane barrier, its clinical application is concentrated on susceptible Gram-positive infections.
The selection of a narrow-spectrum antibacterial agent is ideally based on microbiological evidence. When laboratory testing identifies the pathogen and demonstrates susceptibility to a particular drug, therapy can often be modified from an initial empirical broad-spectrum regimen to a more targeted treatment. This process, commonly described as de-escalation, helps maintain therapeutic effectiveness while reducing unnecessary antimicrobial exposure.
Narrow-spectrum therapy also contributes to antimicrobial stewardship. Unnecessary use of broad-spectrum antibiotics creates selective pressure that can favor the survival and proliferation of resistant microorganisms. Using the most specific effective agent reduces this ecological pressure and supports the preservation of antibiotic effectiveness for future patients.
However, narrow-spectrum agents are not universally appropriate. Their limited range can make them unsuitable for infections caused by unidentified organisms, polymicrobial infections, or pathogens that are resistant to the selected drug. In such circumstances, broader initial coverage may be necessary until microbiological information becomes available.
Narrow-spectrum antibacterial agents represent an important principle of precision in antimicrobial therapy. Their appropriate use combines accurate pathogen identification, susceptibility testing, pharmacological knowledge, and clinical judgment. When an effective narrow-spectrum option is available, choosing it can provide adequate treatment while minimizing collateral effects on the patient’s microbiota and reducing unnecessary selection for antimicrobial resistance.
Broad-spectrum antibacterial agents
Broad-spectrum antibacterial agents are antimicrobial drugs capable of inhibiting or eliminating a relatively large range of bacterial species. Their activity may extend across both Gram-positive and Gram-negative organisms, allowing them to provide therapeutic coverage when the exact causative pathogen has not yet been established. This broad antimicrobial reach makes them particularly valuable in empirical therapy, where treatment must begin before microbiological identification and susceptibility testing are completed.
The breadth of an antibacterial agent is determined by several pharmacological and microbiological characteristics. These include the drug’s ability to penetrate bacterial structures, reach its intracellular or extracellular target, resist bacterial inactivation, and maintain an effective concentration at the site of infection. Structural differences between Gram-positive and Gram-negative organisms also influence susceptibility. Consequently, a broad-spectrum drug does not necessarily act equally against every bacterial species.
Several important antibacterial classes demonstrate broad-spectrum activity. Tetracyclines, such as doxycycline, interfere with bacterial protein synthesis and exhibit activity against numerous Gram-positive and Gram-negative organisms as well as certain atypical bacteria. Fluoroquinolones, including ciprofloxacin and levofloxacin, inhibit bacterial DNA replication by targeting enzymes involved in nucleic-acid metabolism. Their extensive activity has made them useful in selected respiratory, urinary, gastrointestinal, and other bacterial infections. Certain cephalosporins, particularly later-generation agents, also possess expanded activity against diverse bacterial populations, although their individual spectra vary considerably.
Broad-spectrum therapy has an important role in the management of polymicrobial infections, serious infections involving multiple possible pathogens, and situations in which immediate treatment is necessary. For example, in a critically ill patient, delaying antimicrobial therapy while awaiting laboratory identification may increase the risk of disease progression. Initial broad coverage can therefore be justified when the potential consequences of inadequate treatment are substantial. Once culture results and antimicrobial susceptibility data become available, therapy should ideally be de-escalated to the narrowest effective agent.
Despite their therapeutic advantages, broad-spectrum antibacterial agents require careful prescribing. Extensive antimicrobial exposure can exert selective pressure on bacterial populations, favoring the survival and proliferation of resistant organisms. Repeated or inappropriate administration may therefore contribute to the development and dissemination of antimicrobial resistance. Broad-spectrum drugs can also disturb the normal microbial flora of the body. This ecological disruption may permit opportunistic organisms to proliferate, potentially resulting in superinfection, including infections caused by organisms that are naturally resistant to the administered drug.
Another consideration is the potential for adverse drug reactions and drug interactions. Because broad-spectrum agents may affect a larger portion of the patient’s microbial ecosystem, their use should be based on a rational assessment of the suspected infection, local resistance patterns, patient-specific factors, and the likely pathogens involved. Broad-spectrum antibacterial agents represent an important component of modern antimicrobial therapy, particularly when rapid and comprehensive initial coverage is required. Their effectiveness should be balanced against ecological consequences and resistance selection. Appropriate antimicrobial stewardship emphasizes using broad coverage when clinically justified, followed by targeted treatment once the responsible pathogen and its susceptibility profile are known.
Factors determining the antibacterial spectrum of antibiotics
The antibacterial spectrum of a drug is not determined by a single characteristic. It results from the interaction between the drug’s chemical properties, the structural features of the microorganism, the location of infection, and the organism’s susceptibility mechanisms.
1. Cellular entry and drug penetration
For an antibacterial agent to exert its effect, it must reach its site of action inside or around the bacterial cell. The ability of a drug to cross bacterial barriers strongly influences its spectrum. Gram-negative bacteria possess an outer membrane that can restrict the entry of many antibiotics. Hydrophilic drugs may require specific porin channels to enter these organisms, whereas lipid-soluble agents may cross biological membranes more readily. Changes in membrane permeability or porin expression can therefore alter bacterial susceptibility.
2. Availability of a suitable molecular target
Antibacterial activity depends on the presence of a cellular structure or biochemical pathway that can be disrupted by the drug. Antibiotics may act on targets such as bacterial ribosomes, cell-wall synthesis enzymes, DNA replication machinery, or metabolic pathways. If a bacterial species lacks the required target or possesses a structurally different version of it, the drug may have little or no activity. The distribution and characteristics of molecular targets contribute significantly to the antibacterial spectrum.
3. Intrinsic and acquired resistance
Resistance mechanisms can substantially narrow the effective spectrum of an antibacterial agent. Bacteria may produce enzymes that chemically modify or destroy antibiotics, alter drug-binding sites, reduce membrane permeability, or actively expel the drug through efflux systems. Some resistance mechanisms are intrinsic characteristics of a bacterial species, whereas others arise through mutation or acquisition of resistance genes. The presence of such mechanisms can transform an apparently broad-spectrum drug into a much less effective therapeutic option.
4. Drug concentration at the infection site
Antibacterial activity depends not only on whether a microorganism is inherently susceptible but also on whether an adequate drug concentration can be achieved where the infection occurs. Tissue penetration varies considerably among antibacterial agents. Factors such as poor blood supply, abscess formation, tissue barriers, and intracellular localization may prevent sufficient drug exposure. Effective treatment therefore requires drug concentrations that remain adequate for the relevant pathogen while avoiding excessive toxicity.
5. Pharmacokinetic and pharmacodynamic characteristics
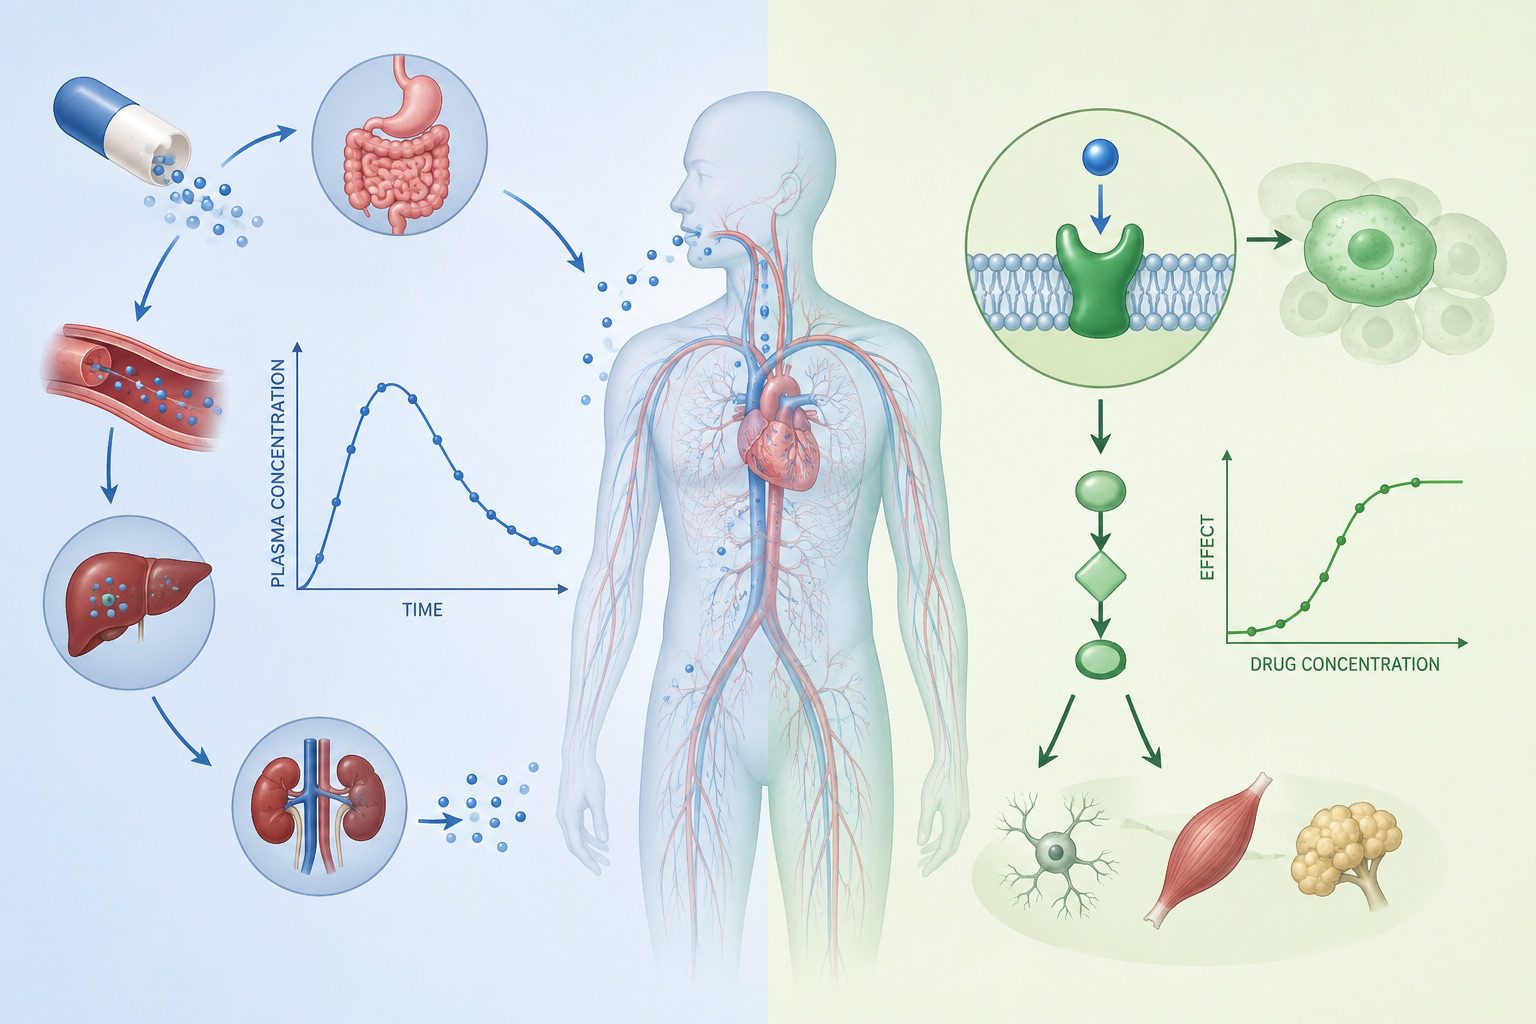
Pharmacokinetics describes how the body absorbs, distributes, metabolizes, and eliminates a drug, whereas pharmacodynamics describes the relationship between drug exposure and antibacterial effect. Parameters such as peak concentration, exposure over time, and duration above the organism’s minimum inhibitory concentration can influence therapeutic success. Differences in dosing schedules and drug disposition can therefore affect the practical spectrum of an antibacterial agent.
6. Structural differences among bacteria
Bacterial architecture is another major determinant of antibacterial susceptibility. Gram-positive organisms generally possess a thick peptidoglycan layer, whereas Gram-negative organisms have a thinner peptidoglycan layer surrounded by an outer membrane. These structural differences influence drug penetration and target accessibility. Additional variations in capsules, cell envelopes, metabolic pathways, and intracellular location further contribute to differences in susceptibility.
7. Bacterial growth and physiological state
The physiological condition of bacteria can modify their response to antibacterial drugs. Rapidly multiplying organisms are often more vulnerable to agents that interfere with cell-wall formation, DNA replication, or protein synthesis. Slowly growing or metabolically inactive bacterial populations may demonstrate reduced susceptibility to certain drugs. Biofilm formation can also decrease effective drug penetration and produce a specialized environment that promotes persistence.
8. Local environmental conditions
The microenvironment surrounding bacteria can influence antibacterial performance. Factors such as pH, oxygen availability, temperature, nutrient supply, and the presence of host proteins may modify drug activity. Some antibiotics function optimally only under particular physiological conditions. The antibacterial spectrum observed in laboratory testing may not always perfectly predict activity within a complex infected tissue.
Clinical importance of spectrum of activity of antibacterial agents
The spectrum of activity of an antibacterial agent represents the range of bacterial species against which the drug demonstrates clinically relevant inhibitory or bactericidal effects. Understanding this spectrum is fundamental to rational antimicrobial selection because therapeutic success depends on matching the pharmacological properties of a drug with the likely or confirmed pathogen. Appropriate spectrum selection allows clinicians to balance microbiological efficacy, patient safety, ecological impact, and resistance prevention.
1. Selection of initial antimicrobial therapy
In many clinical situations, treatment must begin before the causative organism has been definitively identified. This approach, known as empirical antimicrobial therapy, relies on information such as the site of infection, clinical presentation, epidemiological patterns, previous antimicrobial exposure, and locally prevalent resistance profiles. A drug with an appropriate spectrum can provide adequate initial coverage while laboratory investigations are pending. Once the pathogen has been identified, therapy can transition from empirical treatment to targeted antimicrobial therapy. Selecting an agent with activity specifically directed toward the isolated organism improves therapeutic precision and avoids unnecessary antimicrobial exposure.
2. Importance of spectrum in polymicrobial infections
Certain infections involve multiple bacterial species with different susceptibility patterns. Examples include intra-abdominal infections, diabetic wound infections, aspiration-associated infections, and some complicated pelvic infections. In such circumstances, spectrum selection becomes particularly important because treatment may need to cover several aerobic and anaerobic organisms simultaneously. The selected regimen should provide sufficient microbiological coverage without unnecessarily targeting organisms that are unlikely to contribute to the infection. This principle promotes an individualized therapeutic approach rather than indiscriminate broad-spectrum treatment.
3. Prevention of antimicrobial resistance
The clinical spectrum of a drug has important implications for the development and dissemination of antimicrobial resistance (AMR). Exposure to broad-spectrum agents can exert substantial selective pressure on bacterial populations, favoring survival and proliferation of resistant organisms. Repeated or inappropriate use may also disturb the patient’s normal microbiota, potentially facilitating colonization by resistant pathogens. Therefore, choosing the narrowest effective spectrum can reduce unnecessary ecological pressure while maintaining adequate treatment of the infection.
4. Contribution to antimicrobial stewardship
Spectrum selection is a central component of antimicrobial stewardship programs (ASPs). Stewardship emphasizes the appropriate choice, dose, route, and duration of antimicrobial therapy. When microbiological results become available, clinicians may perform de-escalation, replacing an empiric broad-spectrum regimen with a narrower agent that remains effective against the identified pathogen. This strategy improves prescribing efficiency and may reduce adverse drug reactions, drug interactions, healthcare-associated complications, and unnecessary healthcare expenditure.
5. Integration of microbiological data
Culture and antimicrobial susceptibility testing (AST) provide laboratory evidence regarding the identity and drug susceptibility of the causative organism. Results such as minimum inhibitory concentration (MIC) values and susceptibility categories can assist clinicians in determining whether continued treatment with a particular antibacterial agent is appropriate. Interpretation of these findings alongside the patient’s clinical response allows therapy to be refined according to pathogen susceptibility, infection site, tissue penetration, and pharmacokinetic/pharmacodynamic characteristics.
6. Improving therapeutic outcomes
An appropriately selected spectrum increases the probability of achieving clinical and microbiological resolution while limiting avoidable toxicity and ecological disruption. Inadequate coverage may result in persistent infection, treatment failure, complications, or progression of disease. Spectrum of activity is not merely a pharmacological characteristic; it is a practical determinant of therapeutic precision, resistance containment, patient safety, and responsible antimicrobial utilization. Its clinical interpretation should always be integrated with microbiological evidence and individual patient factors.
Therapeutic index of a drug
The therapeutic index (TI) of a drug is a measure of drug safety and dose selectivity. It is a ratio of the toxic dose of a drug to its therapeutic dose. The therapeutic index is an important pharmacological parameter used to describe the safety margin of a drug. TI provides an indication of how closely the dose required to produce a desired therapeutic response is related to the dose capable of producing harmful or toxic effects.
In antimicrobial therapy, the concept of TI is particularly important because an antibacterial agent must exert sufficient activity against pathogenic microorganisms while causing minimal injury to the patient. Both the therapeutic dosage and the toxic dosage of an antimicrobial agent determine the selective toxicity of a drug. Antibiotics with better selective toxicity always have higher therapeutic dosage than toxic dosage.
A good antimicrobial agent (inclusive of antibacterial, antifungal, antiprotozoal and antiviral agent) must have higher therapeutic index to be clinically effective for treating infectious diseases. Therefore, therapeutic index is the ratio of the toxic dosage of an antimicrobial agent compared to its therapeutic dosage. The toxic dosage of a drug is the concentration at which the agent becomes too poisonous to the recipient host, while the therapeutic dosage is the concentration of antimicrobial agent that is clinically relevant for treating a particular microbial disease.
The therapeutic index is calculated using the relationship: TI = TD50/ED50
where TD50 represents the dose that produces a defined toxic effect in 50% of the experimental population, while ED50 represents the dose that produces the desired therapeutic effect in 50% of the population. A larger ratio generally indicates a greater separation between effective and toxic doses and, therefore, a wider margin of safety.
Therapeutic window and clinical relevance of therapeutic index
The therapeutic index should be considered alongside the therapeutic window, which represents the range of drug concentrations that provides adequate therapeutic activity without producing unacceptable toxicity. A drug with a wide therapeutic window can usually be administered with less concern about minor variations in dose or blood concentration. Drugs with a narrow therapeutic window require greater precision in dosing.
For antibacterial agents, maintaining an appropriate drug concentration is essential. Concentrations that are too low may fail to suppress or eliminate the infecting organism and can contribute to treatment failure. Excessively high concentrations, however, may increase the likelihood of adverse effects. Therapeutic dosing aims to achieve adequate antibacterial exposure while remaining below clinically significant toxicity thresholds.
High and low therapeutic index
A high therapeutic index generally indicates that the effective dose is well separated from the toxic dose. Such drugs have a comparatively broad safety margin and are less likely to cause toxicity when appropriately administered. A low therapeutic index indicates that therapeutic and toxic doses are relatively close. Small changes in dosage, absorption, metabolism, renal elimination, or blood concentration may consequently produce clinically important changes in drug exposure. These medications often require individualized dosing and closer observation.
Therapeutic index in antibacterial therapy
The safety of antibacterial drugs is closely related to selective toxicity. This means that the drug preferentially damages or inhibits the microorganism while producing comparatively limited effects on human tissues. Structural and biochemical differences between bacterial cells and human cells provide opportunities for selective antimicrobial action.
Some antibacterial agents, such as aminoglycosides and vancomycin, may require particular attention to dosing because excessive systemic exposure can increase the risk of adverse effects. Renal function, patient age, body weight, hydration status, and drug interactions may influence drug concentrations and consequently affect safety.
Factors influencing the therapeutic margin of a drug
The practical safety of an antibacterial agent is not determined by TI alone. Pharmacokinetics, pharmacodynamics, organ function, route of administration, infection severity, bacterial susceptibility, and patient-specific characteristics can all influence therapeutic outcomes. In selected cases, therapeutic drug monitoring (TDM) is used to measure drug concentrations and guide dosage adjustments.
The therapeutic index provides a useful theoretical measure of drug safety, but clinical prescribing requires a broader assessment of the relationship between dose, exposure, antibacterial efficacy, and toxicity. Selecting an agent with an appropriate therapeutic margin is essential for achieving effective treatment while minimizing preventable adverse reactions.
Therapeutic margin, selective toxicity, and safety considerations in antibacterial therapy
The therapeutic index (TI) is an important pharmacological concept used to evaluate the relative safety of an antibacterial agent. It describes the relationship between the dose required to produce the desired therapeutic effect and the dose capable of producing toxic effects. An antibacterial drug with a wide therapeutic index generally provides a greater margin between effective and harmful concentrations, whereas an agent with a narrow therapeutic index requires more precise dosing and clinical supervision. The therapeutic index therefore contributes to the assessment of drug safety during antimicrobial treatment.
A fundamental characteristic of antibacterial chemotherapy is selective toxicity. Ideally, an antibacterial agent should act preferentially on structures or biochemical processes that are essential to bacterial survival but absent or sufficiently different in human cells. Examples include inhibition of bacterial cell-wall synthesis, disruption of bacterial protein synthesis, interference with nucleic-acid replication, and blockade of specific metabolic pathways. This selective action enables the drug to suppress or eliminate pathogenic bacteria while producing comparatively limited injury to the host.
The safety margin of an antibacterial agent is influenced by several pharmacological and clinical factors. These include the drug’s potency, pharmacokinetic profile, route of administration, tissue distribution, elimination rate, and therapeutic concentration. Renal or hepatic impairment may alter drug clearance and increase systemic exposure, potentially converting a normally safe dosage into a toxic one. Age, body weight, pregnancy, concomitant medications, and underlying disease may also modify the risk of adverse effects.
Some antibacterial agents have a relatively narrow therapeutic window, meaning that concentrations required for effective treatment are relatively close to concentrations associated with toxicity. Aminoglycosides, such as gentamicin and amikacin, are notable examples. Excessive exposure can result in nephrotoxicity and ototoxicity, with possible impairment of renal function and hearing or balance. Dosage regimens may need to be adjusted according to renal function and individual patient characteristics.
Vancomycin also requires careful consideration because excessive exposure can increase the likelihood of adverse effects, particularly kidney injury. Appropriate dosing may involve assessment of renal function and pharmacokinetic exposure. Modern therapeutic monitoring increasingly emphasizes exposure-based measures, such as the area under the concentration-time curve (AUC), rather than relying exclusively on isolated serum concentrations.
Toxicity associated with antibacterial therapy is not restricted to the kidneys or auditory system. Depending on the pharmacological class, adverse effects may involve the liver, gastrointestinal tract, nervous system, bone marrow, cardiovascular system, or skin. For example, some agents can produce hepatic injury, while others may cause hematological abnormalities or neurological effects. Recognizing these potential toxicities is essential for maintaining an appropriate balance between antimicrobial efficacy and patient safety.
Therapeutic drug monitoring (TDM) can be particularly valuable when an antibacterial agent has a narrow therapeutic range, substantial interpatient variability, or a strong relationship between drug exposure and clinical outcome. TDM involves measuring drug concentrations or estimating pharmacokinetic exposure and using these data to individualize treatment. It can help achieve adequate antimicrobial exposure while reducing unnecessary toxicity.
The therapeutic index should not be considered in isolation. Selection of an antibacterial agent requires simultaneous consideration of the causative organism, antimicrobial susceptibility, infection site, severity of disease, pharmacodynamic target, patient-specific factors, and potential adverse effects. Appropriate dosing and monitoring allow clinicians to maintain antibacterial exposure within an effective range while minimizing harm to the patient. Thus, therapeutic index and selective toxicity form important principles underlying the safe and rational use of antibacterial agents.
Relationship between spectrum and therapeutic safety
The spectrum of an antibacterial agent and its therapeutic safety are closely related considerations in antimicrobial therapy. The spectrum of activity describes the range of bacterial species that can be inhibited or eliminated by a drug, whereas therapeutic safety reflects the ability to achieve effective antibacterial concentrations without producing unacceptable toxicity in the patient. Selecting an appropriate agent therefore requires more than simply choosing a drug with the widest possible spectrum.
A broad-spectrum antibacterial agent acts against a large variety of bacterial organisms, which can be particularly valuable when the causative pathogen has not yet been identified. However, broad activity does not automatically indicate a superior safety profile. Such agents may affect susceptible members of the patient’s normal microbiota in addition to the pathogen. This disturbance can contribute to gastrointestinal complications, secondary infections, or selection of antimicrobial-resistant organisms. Extensive bacterial coverage should be used only when clinically justified.
In contrast, narrow-spectrum therapy is directed toward a more restricted group of microorganisms. When microbiological investigations have identified the causative organism and demonstrated its susceptibility, narrowing treatment to the most specific effective agent is generally advantageous. This approach can reduce unnecessary exposure to unrelated bacterial populations and supports the principles of antimicrobial stewardship. It may also decrease the ecological pressure that contributes to the emergence and dissemination of resistant bacteria.
Therapeutic safety is additionally influenced by the pharmacological characteristics of the antibacterial agent. Factors such as dose, route of administration, absorption, distribution, metabolism, elimination, tissue penetration, and duration of therapy can determine whether adequate drug concentrations are achieved at the site of infection. An antibacterial drug must reach a concentration sufficient to inhibit or eradicate the pathogen while remaining within a range that does not cause significant harm to host tissues.
The therapeutic index provides an important concept for understanding this balance. Drugs with a relatively wide therapeutic margin generally allow effective concentrations to be achieved with a lower risk of toxicity. Antibacterial agents with a narrow therapeutic margin require greater attention to dosing and, in some circumstances, monitoring of serum drug concentrations. Renal or hepatic impairment may further alter drug elimination and increase the risk of accumulation and adverse effects.
Another important consideration is that antibacterial effectiveness and toxicity are not determined solely by whether an agent is broad- or narrow-spectrum. A narrow-spectrum drug can still produce serious adverse reactions, while some broad-spectrum agents may be well tolerated when appropriately administered. Spectrum and safety must be evaluated independently as well as together.
The optimal antibacterial choice is therefore one that provides sufficient activity against the suspected or confirmed pathogen while exposing the patient and normal microbiota to the least unnecessary pharmacological burden. Culture results, antimicrobial susceptibility testing, patient-specific factors, infection severity, anatomical site, potential drug interactions, and toxicity risks should all contribute to therapeutic decisions.
Rational antibacterial therapy involves achieving a precise equilibrium between microbial eradication and host protection. Appropriate spectrum selection, individualized dosing, timely modification of empirical therapy, and therapeutic monitoring when indicated can improve clinical outcomes while reducing toxicity and limiting the development of antimicrobial resistance.
References
Ashutosh Kar (2008). Pharmaceutical Microbiology, 1st edition. New Age International Publishers: New Delhi, India.
Axelsen P. H (2002). Essentials of Antimicrobial Pharmacology. Humana Press, Totowa, NJ.
Chemotherapy of microbial diseases. In: Chabner B.A, Brunton L.L, Knollman B.C, eds. Goodman and Gilman’s The Pharmacological Basis of Therapeutics. 12th ed. New York, McGraw-Hill; 2011.
Denyer S.P., Hodges N.A and Gorman S.P (2004). Hugo & Russell’s Pharmaceutical Microbiology. 7th ed. Blackwell Publishing Company, USA. Pp.152-172.
Drusano G.L (2007). Pharmacokinetics and pharmacodynamics of antimicrobials. Clin Infect Dis, 45(suppl):89–95.
Finch R.G, Greenwood D, Norrby R and Whitley R (2002). Antibiotic and chemotherapy, 8th edition. Churchill Livingstone, London and Edinburg.
Hardman JG, Limbird LE, eds. Goodman and Gilman’s The Pharmacological Basis of Therapeutics. 10th ed. New York: McGraw-Hill; 2001.
Katzung, B. G. (2003). Basic and Clinical Pharmacology (9th ed.). NY, US, Lange.
Discover more from Microbiology Class
Subscribe to get the latest posts sent to your email.