Antibiotics constitute one of the most consequential groups of therapeutic agents in modern medicine. Its application in disease management and treatment has substantially transformed the management of bacterial infections and substantially reduced infection-associated morbidity and mortality around the globe. Their classification provides a systematic framework for understanding how individual agents differ in their antibacterial spectrum, cellular targets, pharmacological activity, and therapeutic applications. Among the several approaches used to organize antibiotics, classification according to spectrum of activity and mechanism of action is particularly informative because it connects the clinical range of an antibiotic with the biological processes it disrupts within susceptible bacteria.
The antibacterial spectrum describes the range of microorganisms against which an antibiotic demonstrates activity. On this basis, antibiotics may be broadly categorized as narrow-spectrum, broad-spectrum, or extended-spectrum agents. Narrow-spectrum antibiotics primarily target a restricted group of bacteria, allowing relatively selective treatment when the causative organism has been identified. Broad-spectrum antibiotics, in contrast, exhibit activity against diverse bacterial populations, often encompassing both Gram-positive and Gram-negative organisms. Extended-spectrum agents represent drugs whose activity has been expanded beyond that of their parent compounds, frequently through structural modification.
Spectrum-based classification is clinically important because antimicrobial selection should balance adequate pathogen coverage with the need to minimize unnecessary exposure and disruption of the normal microbiota. The mechanism of action provides a more fundamental biological classification by identifying the bacterial structure or physiological process targeted by an antibiotic. Bacteria possess several distinctive features that can be exploited selectively by antimicrobial agents. Antibiotics may interfere with cell wall construction, protein synthesis, nucleic acid replication or transcription, metabolic pathways, or cytoplasmic membrane integrity.
These mechanisms ultimately impair bacterial growth or viability, although the precise outcome depends on the drug, concentration, microorganism, and physiological state of the bacterial cell. Agents that inhibit cell wall synthesis interfere with the formation or organization of peptidoglycan, an essential component of the bacterial cell envelope. β-lactams and glycopeptides are prominent examples of this group. Protein synthesis inhibitors act primarily on bacterial ribosomes, targeting either the 30S or 50S subunit and disrupting translation. Aminoglycosides, tetracyclines, macrolides, and related agents belong to this mechanistic category. Nucleic acid inhibitors interfere with DNA replication or RNA transcription, thereby preventing bacterial reproduction and essential gene expression. Fluoroquinolones and rifamycins exemplify this group.
Another important category comprises antibiotics that disrupt essential metabolic pathways. Sulfonamides and trimethoprim, for example, interfere with sequential steps in bacterial folate metabolism, depriving microorganisms of metabolites required for nucleic acid synthesis. Membrane-active antibiotics represent a distinct mechanism in which disruption of bacterial membrane structure or function causes leakage of intracellular components and loss of cellular viability. Polymyxins and daptomycin illustrate this mode of antibacterial action.
Spectrum determines which organisms are likely to be susceptible, whereas mechanism explains how bacterial survival is compromised. These classifications facilitate informed antibiotic selection, interpretation of susceptibility patterns, recognition of potential resistance mechanisms, and optimization of antimicrobial stewardship. A mechanistic perspective also clarifies why antibiotics within the same class may share therapeutic characteristics while differing in spectrum, potency, resistance profile, and clinical utility. Classification by spectrum and mechanism provides an integrated foundation for understanding the diversity, therapeutic potential, and limitations of contemporary antibacterial agents.
Broad-spectrum antibiotics
Broad-spectrum antibiotics are versatile antibacterial agents with extensive microbial coverage. They are antimicrobial agents capable of acting against a relatively extensive range of bacterial pathogens, frequently encompassing organisms from both Gram-positive and Gram-negative groups. Their defining characteristic is breadth of antibacterial activity, rather than effectiveness against a particular bacterial species. This broad coverage makes them valuable in clinical situations where the responsible pathogen has not yet been identified or when an infection is suspected to involve multiple bacterial species.
These antibiotics are particularly important in empirical therapy, where treatment must begin before laboratory identification and antimicrobial susceptibility results are available. In severe or potentially life-threatening infections, delaying therapy until the causative organism is confirmed may increase the risk of complications. Broad-spectrum agents therefore provide initial coverage against several possible pathogens while microbiological investigations are underway. Once the organism and its susceptibility profile become available, therapy can often be modified to a more targeted antibiotic.
Several important antibiotic groups possess broad-spectrum activity. Tetracyclines, such as doxycycline, demonstrate activity against numerous Gram-positive and Gram-negative organisms as well as certain atypical bacteria. Fluoroquinolones, including ciprofloxacin and levofloxacin, interfere with bacterial DNA replication by targeting enzymes such as DNA gyrase and topoisomerase IV. Chloramphenicol also exhibits activity against a wide variety of bacterial organisms by inhibiting protein synthesis at the bacterial 50S ribosomal subunit. The actual spectrum of an individual drug varies considerably within each antibiotic class, so broad-spectrum classification should not be interpreted as identical coverage among all agents.
Despite their therapeutic advantages, broad-spectrum antibiotics require careful selection and administration. Because they affect numerous bacterial populations simultaneously, they may eliminate susceptible members of the normal microbiota along with pathogenic organisms. This ecological disturbance can produce consequences such as gastrointestinal symptoms, altered microbial balance, or increased susceptibility to opportunistic infections. The extent of these effects depends on the antibiotic, dose, duration of therapy, route of administration, and characteristics of the patient.
Another major concern is the development and dissemination of antimicrobial resistance. Exposure to broad-spectrum antibiotics creates selective pressure that can favor survival and proliferation of resistant bacterial populations. Repeated or inappropriate use may therefore reduce the future effectiveness of important antimicrobial agents. Resistance can arise through mechanisms such as enzymatic drug inactivation, modification of antibiotic targets, reduced permeability, and active drug efflux.
For these reasons, broad-spectrum antibiotics should generally be used according to principles of antimicrobial stewardship. Appropriate prescribing involves selecting an agent with sufficient initial coverage, using the correct dose and treatment duration, and reassessing therapy when microbiological information becomes available. When possible, treatment can subsequently be de-escalated to a narrower-spectrum antibiotic directed specifically against the identified pathogen.
Broad-spectrum antibiotics represent an important therapeutic resource because of their extensive bacterial coverage, particularly during uncertain or serious infections. However, their ecological impact and potential contribution to resistance make rational prescribing essential. Their greatest clinical value is achieved when broad initial coverage is followed by microbiologically informed, pathogen-directed treatment.
Narrow-spectrum antibiotics
Narrow-spectrum antibiotics are antimicrobial agents designed to act against a relatively restricted range of bacterial microorganisms. Unlike broad-spectrum antibiotics, which target numerous bacterial groups, narrow-spectrum drugs possess selective activity against particular bacterial species or closely related organisms. This focused action makes them especially valuable when the causative pathogen has been identified through clinical assessment, microbiological culture, and antimicrobial susceptibility testing. Their use represents an important principle of rational antibiotic therapy because treatment can be directed toward the pathogen without unnecessarily exposing other members of the body’s normal microbial flora.
The antimicrobial spectrum of a narrow-spectrum antibiotic is determined by its molecular target, ability to reach the bacterial site of infection, and susceptibility of the microorganism. For example, penicillin G demonstrates strong activity against several susceptible Gram-positive bacteria and selected Gram-negative organisms, particularly certain streptococci and spirochetes. Vancomycin, another important example, has a predominantly Gram-positive spectrum and is particularly useful against organisms that are resistant to many β-lactam antibiotics. These agents illustrate how antimicrobial therapy can be tailored according to the biological characteristics of the infecting organism.
A major advantage of narrow-spectrum therapy is microbiological precision. When the pathogen is known, selecting an antibiotic with the narrowest effective spectrum can eliminate the infection while producing less collateral damage to beneficial microorganisms. The human microbiota contributes to colonization resistance, metabolic functions, and maintenance of microbial balance. Excessive exposure to broad-spectrum antibiotics may disturb this ecosystem and facilitate the overgrowth of opportunistic organisms. Narrow-spectrum treatment can therefore help preserve microbial diversity and reduce unnecessary ecological disruption.
Another important benefit is its potential contribution to antimicrobial stewardship. Every unnecessary exposure to an antibiotic can create selective pressure that favors resistant bacterial populations. Broad-spectrum agents exert this pressure across a larger range of organisms, including bacteria that may not be responsible for the infection. In contrast, a well-selected narrow-spectrum antibiotic limits the number of bacterial populations exposed to the drug. Targeted therapy can help reduce the development and spread of antimicrobial resistance when used appropriately.
Narrow-spectrum antibiotics are particularly suitable when laboratory investigations have established the identity and susceptibility profile of the pathogen. Culture and sensitivity testing can provide valuable information about which antimicrobial agent is most likely to achieve therapeutic success. In situations where the causative organism is initially unknown, clinicians may begin with empirical therapy based on the probable pathogens, infection site, local resistance patterns, and patient-specific factors. Once microbiological results become available, treatment may be de-escalated to a narrower agent whenever clinically appropriate.
Narrow-spectrum antibiotics are not universally preferable from the beginning of treatment. In severe or life-threatening infections, delaying effective therapy while waiting for microbiological confirmation may place the patient at risk. Empirical broad-spectrum treatment may sometimes be justified initially, followed by modification to targeted therapy once the responsible organism is identified.
Narrow-spectrum antibiotics represent a cornerstone of targeted antimicrobial treatment. Their selective activity, reduced impact on normal microbiota, and potential to minimize unnecessary selection pressure make them valuable tools in modern infectious-disease management. Appropriate selection requires accurate diagnosis, microbiological evidence, knowledge of local resistance patterns, and careful consideration of the patient’s clinical condition.
Extended-spectrum antibiotics
Extended-spectrum antibiotics constitute an important category of antimicrobial agents. They are characterized by their ability to inhibit a wider range of bacterial pathogens than the earlier or parent members of their respective drug classes. The concept of an “extended spectrum” generally refers to the expansion of antibacterial activity beyond the organisms traditionally susceptible to a particular antibiotic group. This broader coverage may result from structural modification, improved penetration into bacterial cells, enhanced stability against bacterial enzymes, or greater affinity for specific microbial targets.
A major advantage of extended-spectrum antibiotics is their usefulness in infections involving multiple potential pathogens. In clinical practice, the causative organism may not be immediately identifiable, particularly during the initial stages of treatment. An agent with expanded activity can therefore provide appropriate empirical coverage while microbiological investigations are being performed. Once the responsible organism and its susceptibility profile are established, treatment can be refined to the most appropriate antimicrobial.
Chemical modification has played a significant role in the development of extended-spectrum agents. Altering the molecular structure of an established antibiotic can improve its activity against additional bacterial species or enhance its resistance to bacterial mechanisms of drug inactivation. For example, ampicillin and amoxicillin possess broader antibacterial activity than natural penicillin against several Gram-negative organisms. Similarly, successive generations of cephalosporins demonstrate progressively modified antibacterial profiles, with some later agents providing enhanced activity against selected Gram-negative bacteria.
The expansion of spectrum is particularly relevant to Gram-negative pathogens because these organisms possess structural and biochemical characteristics that can limit antibiotic penetration or promote antimicrobial resistance. Certain extended-spectrum agents can overcome some of these barriers through improved cellular entry, increased stability against selected β-lactamases, or stronger interaction with bacterial penicillin-binding proteins. Spectrum expansion does not necessarily imply effectiveness against every resistant organism. Bacterial susceptibility varies considerably according to species, resistance mechanisms, geographical patterns, and local antimicrobial exposure.
The selection of an extended-spectrum antibiotic should therefore be based on clinical indication, suspected pathogens, local resistance data, microbiological findings, and antimicrobial susceptibility testing. Although broad empirical coverage may be justified in severe or polymicrobial infections, unnecessarily prolonged use can exert selective pressure on bacterial populations. This may encourage the emergence and dissemination of resistant strains and can also disturb the normal microbiota.
Another important consideration is the distinction between extended-spectrum activity and universal antibacterial activity. An antibiotic may demonstrate enhanced coverage against particular Gram-negative or Gram-positive organisms while remaining ineffective against other clinically important pathogens. The term “extended-spectrum” should be interpreted in relation to the parent antibiotic and its specific microbiological profile rather than as an indication of unrestricted activity.
Extended-spectrum antibiotics represent an important advancement in antimicrobial therapy. Their expanded activity provides clinicians with valuable treatment options when the likely bacterial cause is uncertain or when infections involve organisms beyond the traditional range of an antibiotic class. The use of extended spectrum antibiotics should remain evidence-based and targeted. Appropriate antimicrobial stewardship ensures that these agents retain their clinical usefulness while minimizing unnecessary exposure, adverse effects, ecological disruption, and the development of antimicrobial resistance.
Major extended-spectrum antibiotics and what they do
Extended-spectrum antibiotics are antimicrobial agents developed or structurally modified to provide broader antibacterial activity than earlier members of their respective classes. They are particularly useful for treating infections involving diverse or initially unidentified pathogens, including selected Gram-negative organisms. Their use should be guided by the suspected or confirmed causative organism, antimicrobial susceptibility testing, clinical severity, local resistance patterns, and principles of responsible antimicrobial stewardship.
- Ampicillin: Ampicillin is an aminopenicillin that inhibits bacterial cell-wall synthesis by binding to penicillin-binding proteins (PBPs). It has expanded activity against several Gram-negative organisms in addition to susceptible Gram-positive bacteria.
- Amoxicillin: Amoxicillin is a semisynthetic aminopenicillin with a mechanism similar to ampicillin. It interferes with peptidoglycan cross-linking in the bacterial cell wall, ultimately causing bacterial cell death. It is active against a range of Gram-positive and selected Gram-negative bacteria.
- Piperacillin: Piperacillin is an extended-spectrum ureidopenicillin that interferes with bacterial cell-wall construction. It provides substantial activity against Gram-negative organisms, including Pseudomonas aeruginosa, and is commonly used in serious infections.
- Ticarcillin: Ticarcillin is an extended-spectrum carboxypenicillin that inhibits cell-wall synthesis. Its activity extends to several Gram-negative bacteria and historically included important activity against Pseudomonas species.
- Cefuroxime: Cefuroxime is a second-generation cephalosporin that disrupts bacterial cell-wall synthesis. Compared with first-generation cephalosporins, it provides improved activity against several Gram-negative organisms while retaining activity against selected Gram-positive bacteria.
- Cefotaxime: Cefotaxime is a third-generation cephalosporin that binds to PBPs and prevents effective cell-wall formation. It has strong activity against many Gram-negative bacteria and is used for a variety of serious bacterial infections.
- Ceftriaxone: Ceftriaxone is another third-generation cephalosporin that blocks peptidoglycan synthesis. Its broad activity against numerous Gram-negative and selected Gram-positive pathogens makes it an important agent for systemic bacterial infections.
- Ceftazidime: Ceftazidime is a third-generation cephalosporin with particularly useful activity against Pseudomonas aeruginosa. It exerts its bactericidal effect by inhibiting bacterial cell-wall synthesis.
- Cefepime: Cefepime is a fourth-generation cephalosporin that inhibits cell-wall synthesis and has broad activity against many Gram-negative organisms, including Pseudomonas aeruginosa, as well as selected Gram-positive bacteria.
- Aztreonam: Aztreonam is a monobactam that targets bacterial PBPs and disrupts cell-wall synthesis. It is primarily active against aerobic Gram-negative bacteria, including some Pseudomonas species.
Cell wall synthesis inhibitors
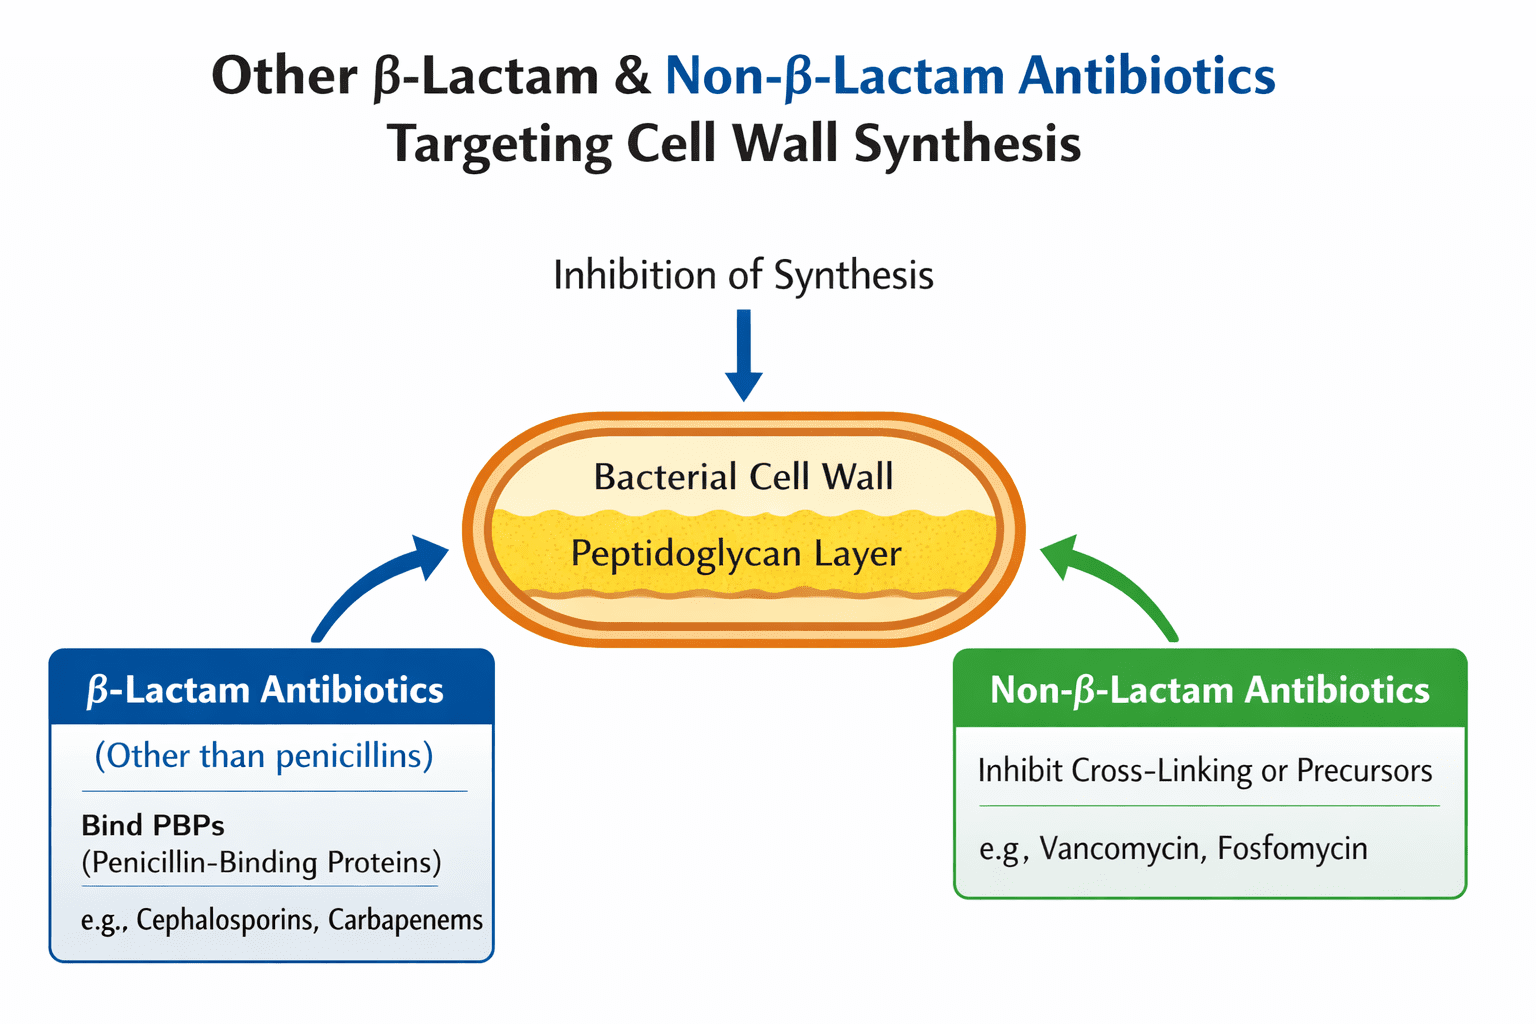
Cell wall synthesis inhibitors constitute one of the most important groups of antibacterial agents because they exploit a structural feature that is essential for bacterial survival but absent from human cells. The bacterial cell wall is primarily composed of peptidoglycan, a rigid, mesh-like polymer that surrounds the cytoplasmic membrane and provides mechanical strength. By interrupting the formation, assembly, or maturation of this structure, these antibiotics compromise the physical stability of the bacterial cell and can ultimately cause cellular rupture.
Peptidoglycan consists of alternating sugar residues, N-acetylglucosamine (NAG) and N-acetylmuramic acid (NAM), interconnected by short peptide chains. Its synthesis occurs through several coordinated stages, including the formation of precursor molecules in the cytoplasm, their transport across the cytoplasmic membrane, and the final incorporation and cross-linking of peptidoglycan units at the cell surface. Antibiotics that interfere with these stages prevent the bacterium from maintaining an intact cell wall, particularly during periods of rapid growth and cell division.
Major classes of cell wall synthesis inhibitors and their mechanisms
Cell wall synthesis inhibitors remain a cornerstone of antimicrobial pharmacology. Their ability to exploit a bacteria-specific structural pathway, combined with their predominantly bactericidal action, makes them particularly valuable against actively proliferating bacterial pathogens.
The principal cell wall synthesis inhibitors include penicillins, cephalosporins, carbapenems, monobactams, and glycopeptides. Penicillins, cephalosporins, carbapenems, and monobactams belong to the β-lactam family. Their antibacterial activity is associated with the β-lactam ring, which enables them to interact with specific bacterial enzymes known as penicillin-binding proteins (PBPs).
PBPs participate in the final stages of peptidoglycan assembly, particularly the transpeptidation reaction responsible for cross-linking adjacent peptide strands. β-lactam antibiotics bind to these enzymes and prevent effective cross-link formation. As a consequence, newly produced cell wall material becomes structurally defective. The growing bacterium is therefore unable to reinforce its cell envelope adequately, making it increasingly vulnerable to mechanical stress and osmotic pressure.
Penicillins represent one of the earliest and most extensively developed β-lactam groups. Their derivatives differ considerably in antibacterial spectrum and resistance characteristics. Cephalosporins have been developed through successive generations, with later members generally demonstrating enhanced activity against selected Gram-negative organisms and improved resistance to certain bacterial β-lactamases. Carbapenems, such as meropenem and imipenem, possess exceptionally broad antibacterial activity and are often reserved for serious infections involving resistant organisms. Monobactams, represented by aztreonam, have a distinctive monocyclic β-lactam structure and primarily target aerobic Gram-negative bacteria.
Glycopeptides, particularly vancomycin, act through a different molecular strategy. Rather than directly inhibiting PBPs, they bind to specific terminal peptide sequences of peptidoglycan precursors. This obstructs the enzymatic reactions required for proper cell wall construction. Their relatively large molecular structure limits penetration through the outer membrane of many Gram-negative bacteria, making them especially important in the treatment of susceptible Gram-positive infections.
A characteristic feature of many cell wall synthesis inhibitors is their bactericidal activity. Their effect is especially pronounced in bacteria undergoing active growth and division because these organisms continuously remodel and expand their peptidoglycan layer. When cell wall construction is interrupted during this process, endogenous bacterial enzymes involved in cell wall turnover may contribute to progressive structural damage.
The weakened envelope can eventually fail, producing osmotic lysis and bacterial death. This growth-dependent action also explains why these antibiotics may demonstrate limited activity against metabolically inactive or non-dividing bacterial populations. The effectiveness of therapy therefore depends not only on the susceptibility of the organism but also on its physiological state.
Cell wall synthesis inhibitors are fundamental to antibacterial therapy because of their selective toxicity. Human cells lack peptidoglycan and therefore do not possess the bacterial enzymes or structural pathways targeted by these drugs. Resistance can significantly reduce their effectiveness. Bacteria may produce β-lactamases, modify PBPs, alter antibiotic entry, or develop other mechanisms that prevent adequate drug activity.
Protein synthesis inhibitors
Protein synthesis inhibitors are a major class of antibiotics that suppress bacterial growth by interfering with the translation of genetic information into functional proteins. Bacteria depend on continuous protein production to maintain cellular structure, regulate metabolic reactions, replicate genetic material, and perform essential physiological functions. These antibiotics exploit structural differences between bacterial and human ribosomes to achieve selective toxicity, thereby impairing microbial activity while generally causing less damage to host cells at therapeutic concentrations.
Bacterial ribosomes are composed of two subunits: the 30S small subunit and the 50S large subunit. Together, they form the 70S ribosome, which coordinates the decoding of messenger RNA (mRNA), the recruitment of transfer RNA (tRNA), and the assembly of amino acids into polypeptide chains. Protein synthesis inhibitors act by binding to specific sites on either subunit, disrupting one or more stages of translation.
Their effects depend on the antibiotic involved, the bacterial species, the concentration achieved at the infection site, and the organism’s susceptibility. Protein synthesis inhibitors suppress bacterial growth by targeting distinct stages of ribosomal translation. Their classification according to ribosomal binding site, mechanism of action, and antibacterial effect provides a useful framework for understanding their therapeutic applications, limitations, and contribution to the treatment of bacterial infections.
Inhibition of the 30S ribosomal subunit
Antibiotics targeting the 30S subunit interfere with the accurate interpretation of mRNA or prevent the entry and positioning of aminoacyl-tRNA during translation. Aminoglycosides, including gentamicin, amikacin, and streptomycin, bind to the 30S subunit and promote misreading of genetic information. This produces abnormal proteins that compromise bacterial function.
Aminoglycosides are generally bactericidal, making them particularly valuable in selected serious infections caused by susceptible aerobic bacteria. Tetracyclines, such as doxycycline and tetracycline, also bind to the 30S subunit but act differently. They prevent aminoacyl-tRNA from attaching to the ribosomal acceptor site, thereby restricting the addition of new amino acids to the growing peptide chain. Their action is usually bacteriostatic, meaning that they inhibit bacterial multiplication rather than directly killing the organisms.
Inhibition of the 50S ribosomal subunit
The 50S subunit coordinates important stages of peptide formation and ribosomal movement. Antibiotics acting at this site interfere with peptide-bond formation, translocation, or the progression of the growing polypeptide chain. Macrolides, including erythromycin, azithromycin, and clarithromycin, bind to the 50S subunit and impede ribosomal translocation. They are commonly bacteriostatic, although their effects can vary with the organism and drug concentration.
Lincosamides, particularly clindamycin, inhibit protein synthesis by binding to the 50S subunit. They are useful against selected Gram-positive bacteria and anaerobic organisms. Oxazolidinones, such as linezolid, prevent the formation of the functional initiation complex required to begin bacterial translation. They are important in the treatment of certain resistant Gram-positive infections, including those caused by methicillin-resistant Staphylococcus aureus and vancomycin-resistant enterococci, when susceptibility and clinical circumstances support their use.
Antibacterial effects and clinical significance of protein synthesis of inhibitors
Protein synthesis inhibitors differ in their spectrum of activity, pharmacokinetic properties, tissue penetration, and clinical applications. Some primarily target Gram-positive bacteria, whereas others are active against selected Gram-negative organisms or atypical pathogens. Their selection depends on the suspected infection, microbiological findings, resistance patterns, and patient-specific factors.
Adverse effects also differ between drug groups. Aminoglycosides may cause nephrotoxicity and ototoxicity, while tetracyclines can cause photosensitivity and dental or bone effects in certain populations. Macrolides may produce gastrointestinal disturbances and, with some agents, prolongation of the QT interval. Clindamycin is associated with an increased risk of Clostridioides difficile infection, whereas linezolid may cause thrombocytopenia and clinically significant drug interactions.
Resistance and rational use of protein synthesis inhibitors
Bacteria can develop resistance to protein synthesis inhibitors through ribosomal target modification, reduced drug uptake, active efflux, enzymatic inactivation, or protection of the ribosomal binding site. These mechanisms can reduce antibiotic effectiveness and complicate infection management. Appropriate prescribing, susceptibility-guided treatment, correct dosing, and adherence to recommended treatment duration are therefore essential.
Nucleic acid synthesis inhibitors
Nucleic acid synthesis inhibitors constitute an important class of antibiotics that suppress bacterial growth by disrupting the molecular processes responsible for DNA replication and RNA transcription. Bacteria depend on the accurate duplication of their genetic material and the continuous transcription of DNA into RNA to maintain cellular activities, produce essential proteins, and reproduce. By targeting enzymes and molecular structures involved in these processes, nucleic acid synthesis inhibitors interfere with bacterial survival and proliferation.
Their selective activity arises from differences between bacterial and human cellular machinery, although selectivity and toxicity vary among individual drugs. Nucleic acid synthesis inhibitors act by targeting bacterial DNA replication or RNA transcription. Fluoroquinolones for example, primarily interfere with DNA gyrase and topoisomerase IV, whereas rifamycins inhibit DNA-dependent RNA polymerase. These distinct molecular targets explain their antimicrobial effects and establish their importance in modern antibacterial therapy.
Inhibition of DNA replication
DNA replication is essential for bacterial multiplication because each daughter cell requires a complete copy of the parental genome. During replication, bacterial enzymes unwind the DNA double helix, relieve torsional stress, and synthesize complementary DNA strands. Antibiotics that interfere with these processes prevent the accurate duplication of genetic information and impair bacterial cell division.
Fluoroquinolones, including ciprofloxacin, levofloxacin, and moxifloxacin, are prominent examples of antibiotics that inhibit bacterial DNA replication. They act primarily by targeting DNA gyrase and topoisomerase IV, enzymes responsible for controlling DNA topology and separating replicated chromosomes. DNA gyrase introduces negative supercoils that facilitate DNA replication and transcription, whereas topoisomerase IV plays a major role in separating interlinked daughter chromosomes.
Fluoroquinolones stabilize enzyme–DNA cleavage complexes, preventing the normal resealing of DNA strands. This process leads to DNA damage, chromosome fragmentation, and bacterial death. These agents are generally bactericidal, although their activity depends on the organism, drug concentration, and susceptibility profile.
Interference with RNA transcription
Transcription is the process through which genetic information encoded in DNA is converted into RNA. Bacteria require RNA molecules for protein synthesis, gene regulation, and numerous cellular functions. Inhibition of transcription therefore deprives bacterial cells of essential instructions needed to maintain metabolism, respond to environmental conditions, and reproduce.
Rifamycins, particularly rifampicin, inhibit bacterial DNA-dependent RNA polymerase. This enzyme catalyses the synthesis of RNA using DNA as a template. Rifampicin binds to the β-subunit of bacterial RNA polymerase and blocks the early stages of RNA chain formation. The production of messenger RNA and other essential RNA molecules is disrupted.
This interruption compromises protein synthesis and other fundamental cellular processes. Rifampicin is especially important in the treatment of tuberculosis and is also used in selected infections caused by susceptible bacteria. Resistance can emerge rapidly when it is used alone against active tuberculosis; therefore, combination therapy is essential.
Bactericidal activity and antimicrobial resistance of nucleic acid inhibitors
Many nucleic acid synthesis inhibitors exert bactericidal effects by producing irreversible genetic damage or severely disrupting essential cellular processes. Ttheir activity is not identical across all organisms or clinical circumstances. The effectiveness of treatment depends on bacterial susceptibility, drug penetration, dosage, and the infection site. Resistance may develop through mutations in antibiotic target enzymes, reduced intracellular drug accumulation, enhanced drug efflux, or other protective mechanisms.
For example, alterations in DNA gyrase or topoisomerase IV can reduce fluoroquinolone binding, while mutations affecting the rpoB gene, which encodes the β-subunit of RNA polymerase, can confer rifampicin resistance. These mechanisms highlight the importance of appropriate antibiotic selection, susceptibility testing, and adherence to recommended treatment regimens.
Clinical significance of nucleic acid inhibitors
Nucleic acid synthesis inhibitors are valuable in treating a range of bacterial infections because they act on fundamental processes required for microbial survival. Fluoroquinolones are used for selected urinary, gastrointestinal, respiratory, and other bacterial infections, depending on the drug and susceptibility results. Rifamycins have a central role in tuberculosis treatment and are used in certain other infections.
Metabolic pathway inhibitors (antimetabolites)
Metabolic pathway inhibitors, also known as antimetabolites, are a class of antibiotics that suppress bacterial growth by interfering with essential biochemical reactions. These agents target metabolic processes required for the synthesis of nucleotides, amino acids, and other cellular components necessary for bacterial survival and multiplication.
Unlike antibiotics that directly damage the cell wall or disrupt protein synthesis, antimetabolites primarily act by obstructing specific enzymatic steps within bacterial metabolic pathways. Their selective activity is based on differences between bacterial and human metabolism, which allows certain drugs to inhibit microbial growth while producing comparatively limited effects on host cells when appropriately administered.
Inhibition of folic acid synthesis
The principal mechanism of action of many antibacterial antimetabolites involves the inhibition of folate metabolism. Folic acid derivatives are essential for the synthesis of purines and thymidylate, which are required for DNA replication and cell division. Many bacteria synthesize folate through a pathway involving para-aminobenzoic acid (PABA), whereas humans cannot synthesize folate de novo and must obtain it from dietary sources. This metabolic distinction provides an important basis for selective antibacterial activity. By interrupting folate production or utilization, antimetabolites reduce the availability of essential intermediates required for bacterial growth and reproduction.
Sulfonamides: competitive inhibitors of folate synthesis
Sulfonamides are synthetic antibacterial agents that structurally resemble para-aminobenzoic acid (PABA). They competitively inhibit the enzyme dihydropteroate synthase, preventing the incorporation of PABA into dihydropteroate, an intermediate in bacterial folate synthesis. This inhibition reduces the formation of tetrahydrofolate precursors required for nucleotide production. Bacterial DNA synthesis and cellular multiplication become impaired. Sulfonamides are generally bacteriostatic when used alone, meaning they inhibit bacterial growth rather than directly killing the organisms. Their antibacterial spectrum varies by agent and susceptibility pattern, and resistance can develop through target-enzyme alterations, increased PABA production, or reduced drug uptake.
Trimethoprim: inhibition of dihydrofolate reduction
Trimethoprim acts at a different stage of the folate pathway. It selectively inhibits bacterial dihydrofolate reductase, the enzyme responsible for converting dihydrofolate into tetrahydrofolate. This reaction is essential for maintaining the pool of reduced folates needed for the synthesis of purines and thymidylate. By restricting tetrahydrofolate availability, trimethoprim impairs DNA synthesis and bacterial proliferation. Its greater affinity for bacterial dihydrofolate reductase than for the corresponding human enzyme contributes to its selective antibacterial action. When administered alone, trimethoprim is generally bacteriostatic, although its effectiveness depends on the organism, drug concentration, and susceptibility profile.
Synergistic action of sulfamethoxazole and trimethoprim
The combination of sulfamethoxazole and trimethoprim, commonly known as co-trimoxazole, demonstrates the principle of sequential blockade. Sulfamethoxazole inhibits an early step in folate synthesis, while trimethoprim inhibits a subsequent enzymatic reaction. Simultaneous interference at these consecutive stages produces a more pronounced reduction in folate-dependent metabolic activity than either agent may achieve alone. The combination can exert bactericidal activity against susceptible organisms, although this effect is not universal. Co-trimoxazole is used to treat selected urinary tract infections, certain respiratory infections, and specific opportunistic infections, including Pneumocystis jirovecii pneumonia.
Antibacterial spectrum and clinical significance of antimetabolites
The spectrum of antimetabolites depends on the drug, the bacterial species, and local resistance patterns. Sulfonamides and trimethoprim exhibit activity against various susceptible Gram-positive and Gram-negative bacteria. However, resistance has reduced their reliability against some common pathogens. Their clinical use therefore requires consideration of infection type, patient characteristics, and microbiological findings. These agents are also important in selected prophylactic regimens, particularly for patients at risk of opportunistic infections. Appropriate prescribing helps preserve their effectiveness and minimizes unnecessary antimicrobial exposure.
Resistance mechanisms and therapeutic limitations of antimetabolites
Bacteria may develop resistance to antimetabolites through several mechanisms, including mutations in target enzymes, acquisition of resistant enzyme variants, increased synthesis of PABA, and reduced intracellular drug accumulation. Some organisms can also obtain folate-related metabolites from their environment, diminishing the impact of pathway inhibition. Adverse effects and drug interactions must be considered during treatment; for example, co-trimoxazole may cause hypersensitivity reactions, bone marrow suppression, and disturbances in potassium levels in susceptible patients.
Monitoring is particularly important during prolonged therapy or in patients with renal impairment. Metabolic pathway inhibitors represent an important category of antibiotics because they exploit essential differences between bacterial and human biochemical processes. Sulfonamides inhibit dihydropteroate synthase, whereas trimethoprim blocks dihydrofolate reductase. These complementary mechanisms restrict folate-dependent nucleotide synthesis and ultimately suppress bacterial multiplication. Their therapeutic value depends on the organism’s susceptibility, appropriate drug selection, and careful monitoring for resistance and adverse effects.
Cell membrane-acting antibiotics
Cell membrane-acting antibiotics constitute an important category of antimicrobial agents that eliminate bacteria by interfering with the structural integrity and physiological functions of the bacterial cytoplasmic membrane. Unlike antibiotics that inhibit cell wall construction, protein synthesis, or nucleic acid replication, these agents directly compromise the membrane, which regulates the movement of substances into and out of the bacterial cell. The disruption of membrane function interferes with essential cellular processes and may result in rapid bacterial death.
The bacterial cytoplasmic membrane is composed primarily of a phospholipid bilayer containing embedded proteins. It maintains cellular homeostasis, supports nutrient transport, facilitates the removal of waste products, and participates in energy generation. The membrane also sustains the electrochemical gradient required for ATP production and other energy-dependent activities. When antibiotics damage this structure, bacterial cells lose their ability to preserve internal conditions and maintain normal metabolic activity.
Membrane-active antibiotics generally operate through interactions with membrane lipids or by altering membrane permeability. These interactions can produce pores, destabilize the lipid bilayer, or dissipate the electrical potential across the membrane. Essential ions and intracellular molecules may escape, while the cell becomes unable to sustain vital biochemical reactions. Depending on the antibiotic, its concentration, and the susceptibility of the organism, these effects may culminate in irreversible cellular injury.
Major classes and representative examples of cell membrane-acting antibiotics
Polymyxins: Polymyxins, including polymyxin B and colistin (polymyxin E), are membrane-active antibiotics primarily used against susceptible Gram-negative bacteria. Their positively charged chemical groups interact with negatively charged components of the bacterial outer membrane, particularly lipopolysaccharides. This interaction displaces stabilizing divalent cations and destabilizes the membrane structure.
Subsequent membrane damage increases permeability and disrupts cellular integrity. Polymyxins are particularly significant in the treatment of selected multidrug-resistant Gram-negative infections, including infections caused by susceptible strains of Pseudomonas aeruginosa and Acinetobacter baumannii. However, their clinical use is limited by potential nephrotoxicity and neurotoxicity, making careful patient assessment and monitoring important.
Daptomycin: Daptomycin is a cyclic lipopeptide antibiotic with activity against susceptible Gram-positive bacteria. In the presence of calcium ions, it interacts with the bacterial cytoplasmic membrane and causes membrane depolarization. This process disrupts the electrical potential required for essential cellular functions and interferes with processes associated with bacterial survival.
Daptomycin is bactericidal against many susceptible Gram-positive organisms and is used for selected serious infections, including those caused by Staphylococcus aureus. Unlike polymyxins, daptomycin is not used to treat Gram-negative infections because the outer membrane of these bacteria prevents effective access to its target. Its clinical administration also requires consideration of potential muscle toxicity.
Biological consequences of membrane disruption
The antimicrobial activity of these agents arises from their ability to interfere with several interconnected physiological functions. Loss of membrane permeability control causes the leakage of potassium ions, metabolites, and other essential intracellular constituents. Disruption of membrane potential compromises energy-dependent transport and cellular metabolism.
As membrane damage progresses, the bacterial cell can no longer maintain homeostasis, resulting in loss of viability. The relatively direct nature of membrane disruption can produce rapid bactericidal activity. Effectiveness depends on the organism’s membrane composition, the antibiotic’s ability to reach its target, and the presence of resistance mechanisms.
Clinical significance of membrane disruption
Cell membrane-acting antibiotics are valuable therapeutic options when infections involve susceptible organisms that are resistant to other antimicrobial classes. Their distinctive mechanisms provide alternatives to drugs targeting cell wall synthesis or ribosomal function. Resistance can emerge through alterations in membrane components, changes in surface charge, or other adaptive mechanisms that reduce antibiotic binding.
Cell membrane-acting antibiotics exert their antimicrobial effects by compromising membrane stability, permeability, and electrical function. Polymyxins primarily target susceptible Gram-negative bacteria, whereas daptomycin acts against susceptible Gram-positive organisms. Their distinct mechanisms, clinical applications, and toxicity profiles make accurate organism identification and appropriate antibiotic selection essential for effective treatment.
References
Ashutosh Kar (2008). Pharmaceutical Microbiology, 1st edition. New Age International Publishers: New Delhi, India.
Axelsen P. H (2002). Essentials of Antimicrobial Pharmacology. Humana Press, Totowa, NJ.
Chemotherapy of microbial diseases. In: Chabner B.A, Brunton L.L, Knollman B.C, eds. Goodman and Gilman’s The Pharmacological Basis of Therapeutics. 12th ed. New York, McGraw-Hill; 2011.
Denyer S.P., Hodges N.A and Gorman S.P (2004). Hugo & Russell’s Pharmaceutical Microbiology. 7th ed. Blackwell Publishing Company, USA. Pp.152-172.
Drusano G.L (2007). Pharmacokinetics and pharmacodynamics of antimicrobials. Clin Infect Dis, 45(suppl):89–95.
Finch R.G, Greenwood D, Norrby R and Whitley R (2002). Antibiotic and chemotherapy, 8th edition. Churchill Livingstone, London and Edinburg.
Gillespie S.H and Bamford K.B (2012). Medical Microbiology and Infection at a glance. 4th edition. Wiley-Blackwell Publishers, UK.
Hardman JG, Limbird LE, eds. Goodman and Gilman’s The Pharmacological Basis of Therapeutics. 10th ed. New York: McGraw-Hill; 2001.
Katzung, B. G. (2003). Basic and Clinical Pharmacology (9th ed.). NY, US, Lange.
Discover more from Microbiology Class
Subscribe to get the latest posts sent to your email.