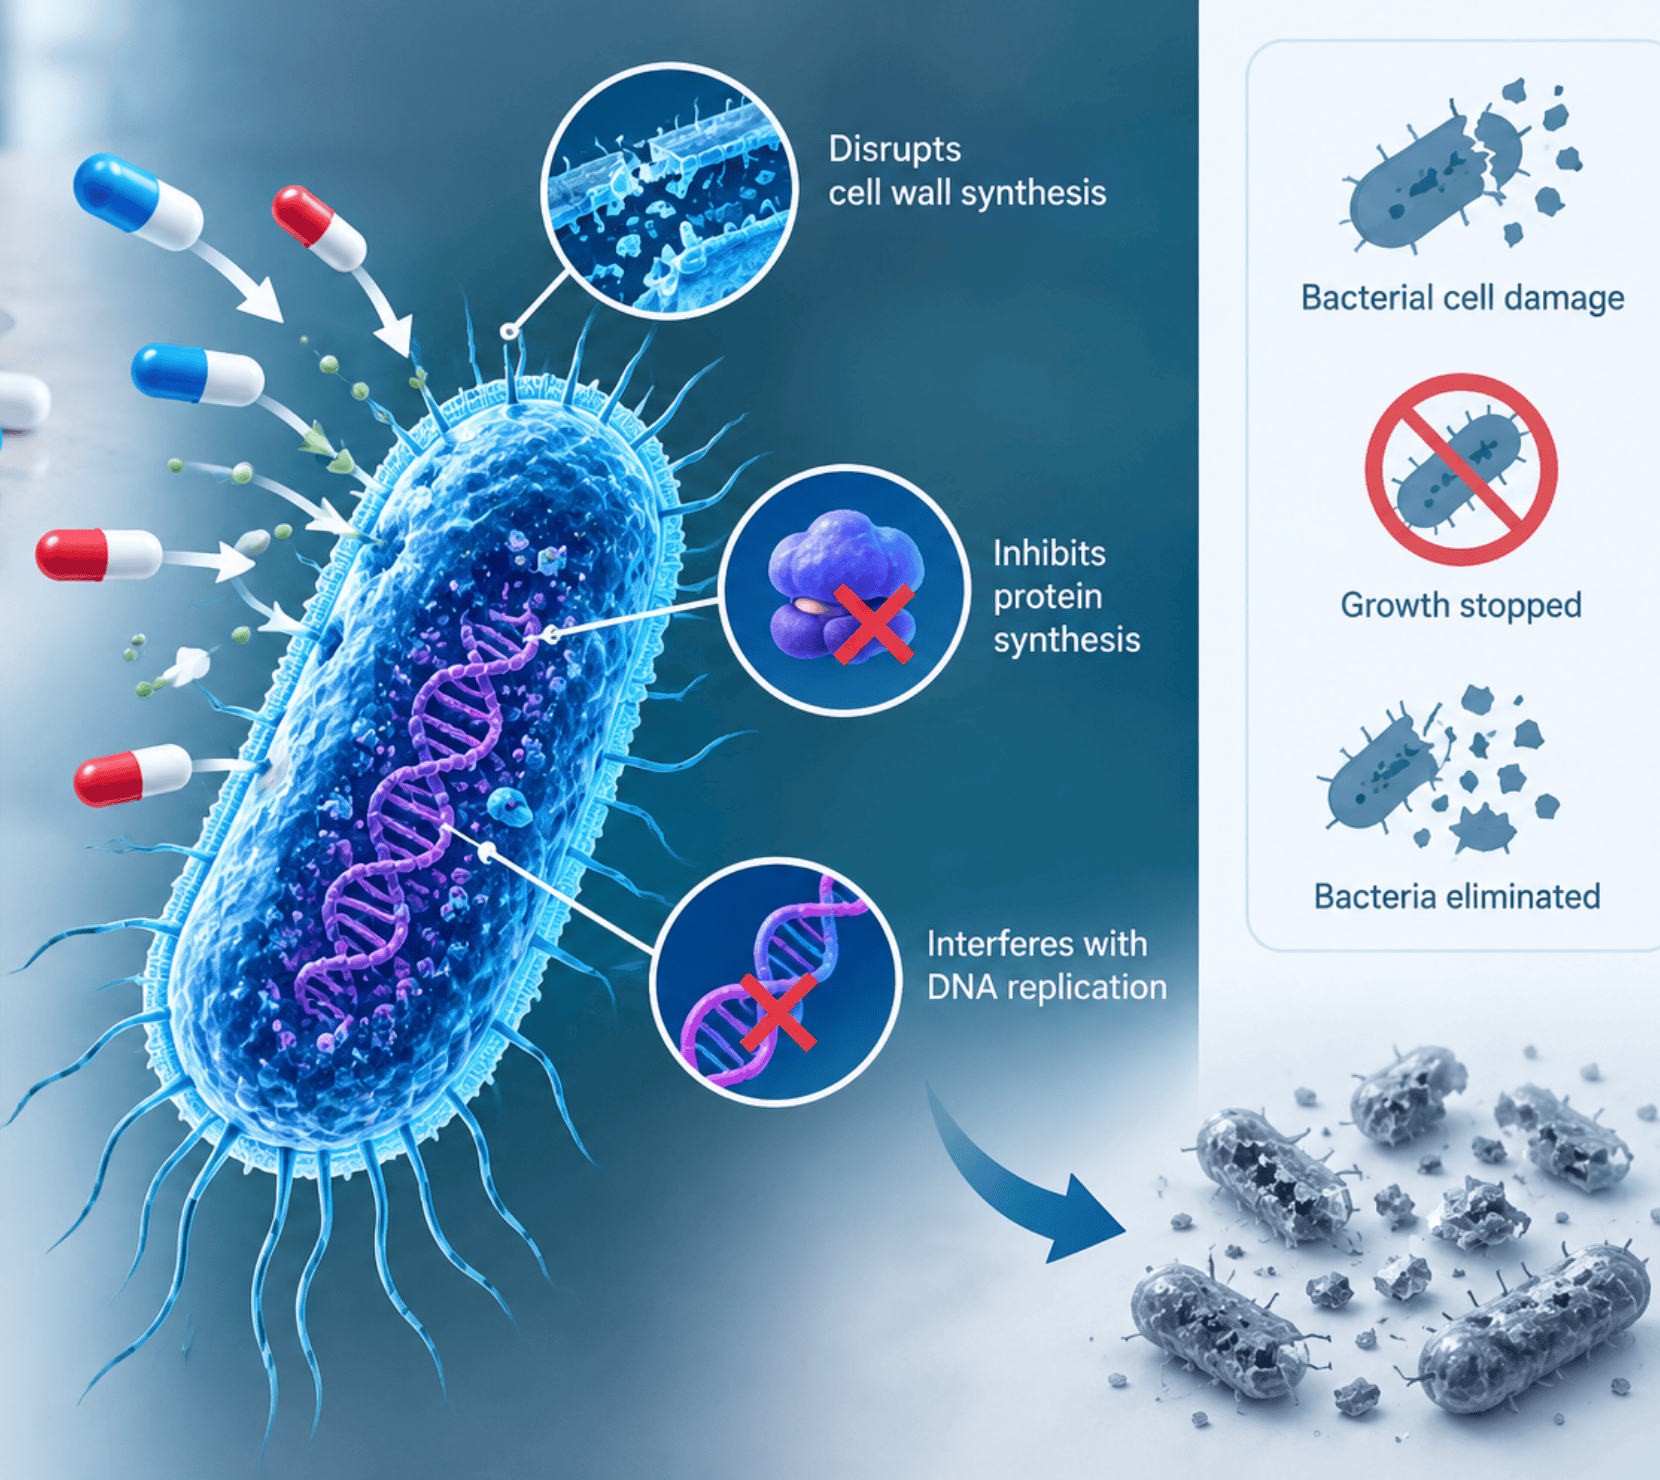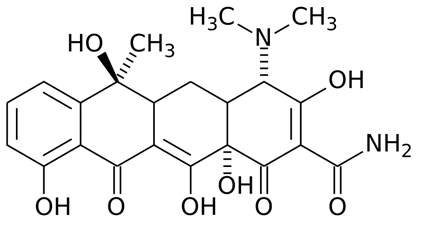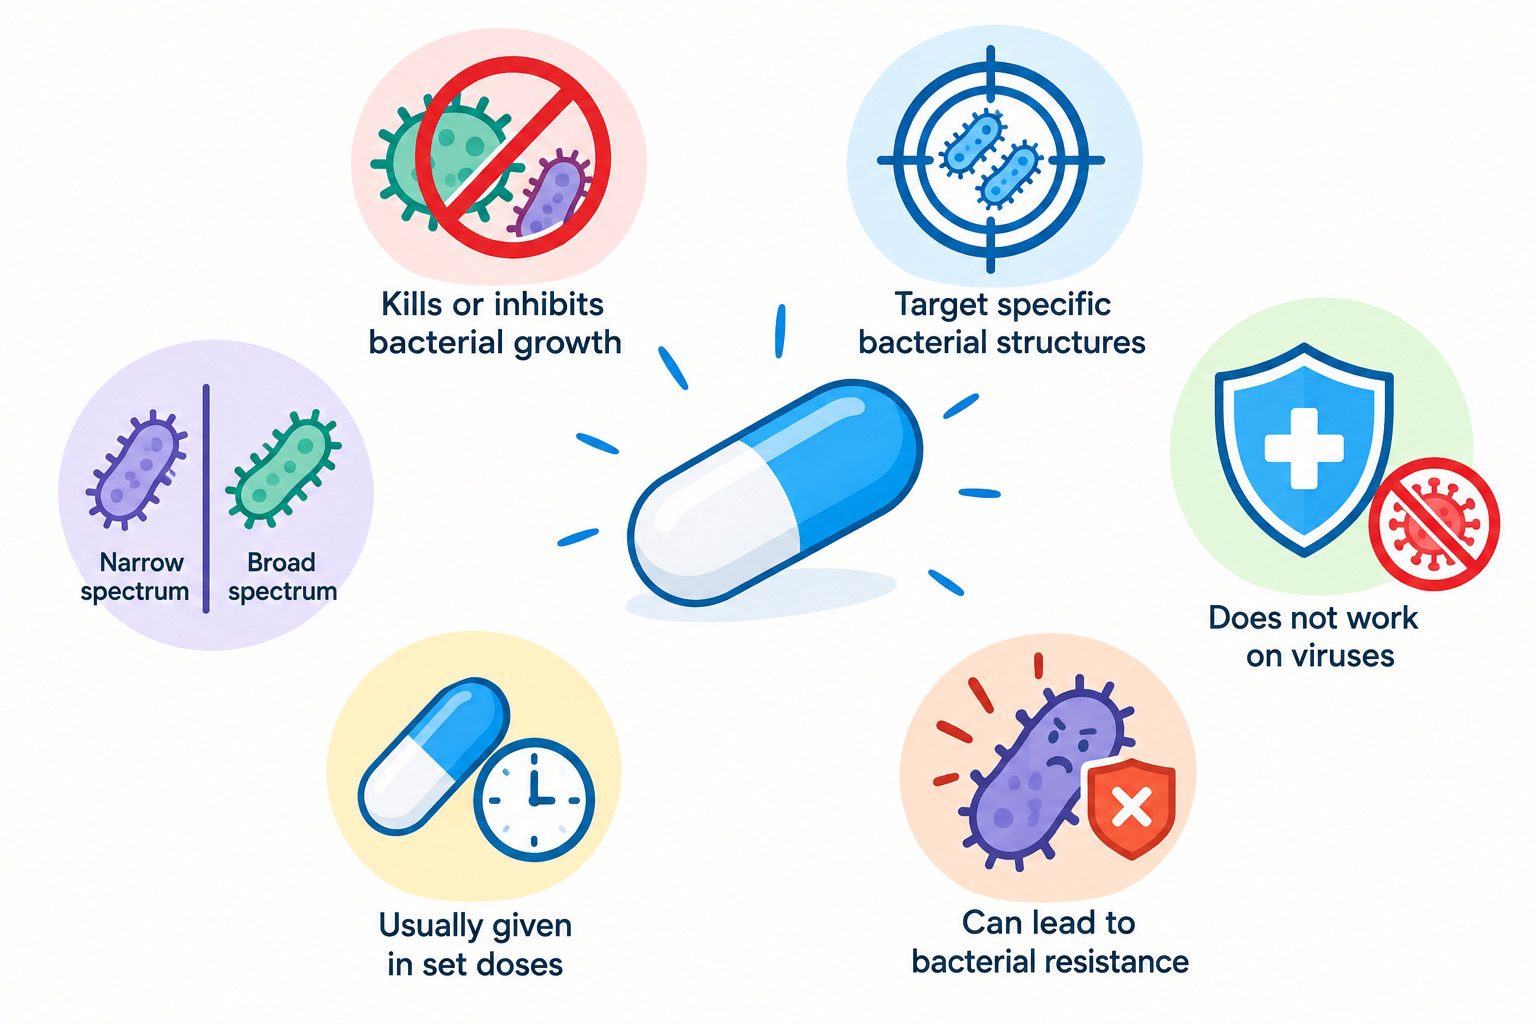
Antibiotics are medicinal substances used to treat bacterial infections by killing bacteria or inhibiting their growth and reproduction. They may be produced naturally by microorganisms or manufactured and modified synthetically. Examples include penicillin, amoxicillin, and azithromycin. Antibiotics are generally used specifically against bacteria and are not effective against viral infections such as influenza or most common colds.
Antimicrobial agents are a broader category of substances that act against microorganisms. They include agents effective against bacteria (antibacterials), fungi (antifungals), viruses (antivirals), and parasites (antiparasitics). Antibiotics are considered a subgroup of antimicrobial agents, although the terms are sometimes used interchangeably in general communication.
The key distinction is their target: antibiotics primarily refer to agents acting against bacteria, whereas antimicrobial agents encompass a wider range of microorganisms. This distinction is important for selecting appropriate treatment and preventing inappropriate antimicrobial use and resistance. Examples of antimicrobial agents include antibiotics, antivirals, antifungals, antiprotozoals, antiseptics, disinfectants, sanitizers, antimicrobial peptides, bacteriophages, and sterilizing agents.
Antimicrobial agents constitute an essential group of biologically active substances employed to prevent, control, and treat infections caused by microorganisms. Within this broad category, antibiotics and related therapeutic agents occupy an important position because of their ability to interfere with specific cellular structures and biochemical processes that are essential for microbial survival and replication. Depending on their target organism and mechanism of action, antimicrobial agents may include antibacterial, antiviral, antifungal, and antiprotozoal compounds. Although these agents share the general objective of reducing or eliminating infectious microorganisms, their biological targets, pharmacological properties, spectrum of activity, and therapeutic applications differ considerably.
Antibacterial agents are primarily directed against bacterial pathogens and commonly act by disrupting processes such as cell-wall synthesis, protein production, nucleic-acid replication, or essential metabolic pathways. Their selective activity is largely associated with differences between microbial cells and host cells, allowing therapeutic concentrations to inhibit bacterial growth while minimizing damage to the patient. Some antibacterial compounds exert a bactericidal effect by causing irreversible cellular damage and microbial death, whereas others are bacteriostatic and predominantly suppress bacterial multiplication, allowing host defense mechanisms to contribute to pathogen clearance. The distinction between these effects is influenced by the antimicrobial compound, microorganism, concentration achieved at the site of infection, and physiological conditions within the host.
Antiviral agents differ fundamentally from antibacterial drugs because viruses depend extensively on host-cell machinery for replication. Antiviral therapy generally targets virus-specific stages of the infectious cycle, including attachment, entry, genome replication, protein processing, assembly, or release. Antifungal agents, in contrast, are designed to act against fungal organisms and may target cellular components such as the fungal cell membrane or cell wall. Antiprotozoal agents similarly possess specialized mechanisms directed toward protozoan pathogens, whose cellular organization and metabolic requirements differ from those of bacteria and fungi. These biological distinctions explain why an antimicrobial compound effective against one class of microorganism may have little or no therapeutic activity against another.
The characteristics of antimicrobial agents also extend beyond their direct effects on pathogens. Factors such as absorption, distribution, metabolism, elimination, tissue penetration, dosing interval, toxicity, drug interactions, and the development of resistance influence their clinical utility. The effectiveness of treatment therefore depends not only on the intrinsic activity of an antimicrobial compound but also on achieving an appropriate concentration at the site of infection while maintaining acceptable safety for the host.
Antimicrobial substances may additionally be used outside systemic or clinical therapy. Certain compounds are incorporated into infection-control practices, sanitation procedures, pharmaceutical formulations, and environmental disinfection to reduce microbial contamination on inanimate surfaces. Such applications differ from therapeutic use because the objective is generally microbial reduction or elimination rather than selective treatment within a living host.
Antibacterial agents
Antibacterial agents are therapeutic compounds designed to suppress or eliminate bacterial pathogens while limiting injury to host tissues. Their activity depends on selective interactions with bacterial structures or biochemical pathways that differ sufficiently from those of human cells. Major targets include the peptidoglycan cell wall, cytoplasmic membrane, ribosomal machinery, nucleic-acid synthesis, and essential metabolic reactions. β-lactam antibiotics, including penicillins, cephalosporins, carbapenems, and monobactams, interfere with cell-wall assembly by binding penicillin-binding proteins.
Glycopeptides such as vancomycin disrupt peptidoglycan formation through a different molecular mechanism and are particularly important against susceptible Gram-positive organisms. Other antibacterial classes act primarily at the ribosome. Macrolides, tetracyclines, aminoglycosides, and oxazolidinones alter protein translation through interactions with bacterial ribosomal subunits. Fluoroquinolones inhibit DNA gyrase and topoisomerase IV, thereby compromising bacterial chromosome replication and repair. Sulfonamides and trimethoprim interfere with folate metabolism, reducing the availability of metabolites required for nucleic-acid synthesis.
The clinical effectiveness of antibacterial therapy depends on pathogen identification, antimicrobial susceptibility, infection site, pharmacokinetic exposure, and host characteristics. Resistance may emerge through enzymatic drug degradation, target modification, altered membrane permeability, active efflux, or acquisition of resistance genes. Antimicrobial stewardship emphasizes appropriate agent selection, dosing, duration, and de-escalation when microbiological information becomes available. Contemporary antibacterial research increasingly explores β-lactamase inhibitors, bacteriophage-derived approaches, antimicrobial peptides, narrow-spectrum compounds, and agents directed toward previously inaccessible bacterial targets. These strategies seek to expand therapeutic options while reducing unnecessary disruption of the human microbiome.
Antiviral agents
Antiviral agents differ fundamentally from conventional antibacterial drugs because viruses depend heavily on host-cell machinery for replication. Therapeutic development therefore focuses on viral proteins, replication intermediates, entry mechanisms, or virus-specific enzymes that provide opportunities for selective intervention. The antiviral pipeline encompasses compounds targeting attachment, fusion, penetration, uncoating, genome replication, protein processing, assembly, and virion release.
Nucleoside and nucleotide analogues represent an important category. After intracellular activation, these compounds can interfere with viral polymerases and may function as chain terminators or competitive substrates. Non-nucleoside polymerase inhibitors act through alternative binding sites and can modify enzyme conformation. Protease inhibitors prevent the cleavage of viral polyproteins into functional components, disrupting maturation of infectious particles. Integrase inhibitors block incorporation of viral genetic material into host chromosomes and constitute a major therapeutic strategy for retroviral infections.
Some antiviral therapies act at the earliest stages of the viral life cycle. Entry inhibitors can prevent receptor engagement or membrane fusion, while capsid-directed compounds may interfere with particle stability or intracellular trafficking. Neuraminidase inhibitors, for example, reduce the release of newly formed influenza virions from infected cells. Other approaches exploit host factors required for viral replication, although host-directed therapies require careful evaluation because interference with cellular pathways can produce toxicity.
Viral evolution creates an important challenge because replication errors and selective pressure can generate drug-resistant variants. Combination therapy can reduce the probability that a single resistant mutation will produce treatment failure. Current antiviral research also investigates long-acting formulations, broadly neutralizing antibodies, RNA-based technologies, targeted delivery systems, and compounds capable of suppressing persistent viral reservoirs. These approaches aim to improve adherence, increase antiviral breadth, and address infections for which eradication remains difficult.
Antifungal agents
Antifungal agents are used against pathogenic fungi whose cellular architecture shares several features with human cells, creating a narrower therapeutic window than that available for many antibacterial drugs. Fungi possess distinctive structures and biochemical pathways that can serve as pharmacological targets. The fungal cell membrane contains ergosterol rather than cholesterol as its principal sterol, while the cell wall incorporates polysaccharides such as glucan and chitin. These differences provide important opportunities for selective intervention.
Polyenes, including amphotericin B, bind ergosterol and increase membrane permeability, leading to leakage of intracellular components. Azole compounds inhibit enzymes involved in ergosterol biosynthesis, thereby altering membrane composition and impairing fungal growth. Echinocandins act on a different structure by inhibiting β-1,3-glucan synthesis, weakening the fungal cell wall. Flucytosine interferes with fungal nucleic-acid metabolism after conversion to active intracellular metabolites. These mechanistic differences allow clinicians to tailor treatment according to fungal species, disease location, severity, and susceptibility profile.
Clinically significant fungal infections range from superficial dermatological conditions to invasive diseases involving the bloodstream, lungs, central nervous system, or multiple organs. Opportunistic pathogens can produce severe disease in individuals with compromised immune defenses, implanted medical devices, or prolonged exposure to broad-spectrum antibiotics. Diagnostic uncertainty can complicate management because fungal cultures may require extended incubation and some infections occur at sites where obtaining tissue is difficult.
Resistance to antifungal therapy is increasingly important. Mechanisms include alterations in drug targets, increased efflux-pump activity, changes in sterol pathways, and modifications of cell-wall composition. Emerging strategies therefore investigate novel target classes, combination regimens, immunotherapeutic approaches, optimized drug delivery, and rapid molecular diagnostics. Development of antifungal agents must balance potency against toxicity, tissue penetration, drug interactions, and the possibility of resistance during prolonged treatment.
Antiprotozoal agents
Antiprotozoal agents target unicellular eukaryotic parasites responsible for diseases such as malaria, giardiasis, amoebiasis, trichomoniasis, and leishmaniasis. Because protozoa possess complex cellular machinery and substantial similarities to human cells, therapeutic selectivity can be challenging. Successful agents exploit distinctive metabolic pathways, organelles, transport systems, or life-cycle stages that are sufficiently different from those of the host.
Antimalarial therapy illustrates the diversity of antiprotozoal mechanisms. Artemisinin derivatives generate reactive intermediates within susceptible parasites and are commonly incorporated into combination regimens. Other antimalarial compounds interfere with heme detoxification, mitochondrial function, or parasite-specific metabolic processes. Combination therapy is particularly important because Plasmodium species can develop resistance when exposed to inadequate or prolonged monotherapy.
Nitroimidazoles such as metronidazole are widely used against several anaerobic protozoa. Their activity involves intracellular reduction and formation of reactive metabolites that damage essential cellular components. Other antiprotozoal compounds act against nucleic-acid synthesis, protein production, mitochondrial metabolism, or specialized parasite organelles. Treatment selection is therefore closely connected to parasite species, anatomical localization, disease stage, regional resistance patterns, and host factors.
Protozoal diseases frequently involve complex transmission cycles in which environmental reservoirs, vectors, contaminated water, food, or sexual contact contribute to dissemination. Pharmacological control therefore works most effectively when integrated with diagnostic surveillance, vector management, sanitation, preventive measures, and appropriate case identification. Drug resistance remains a major concern, particularly for malaria, where parasite populations can acquire mutations affecting multiple therapeutic targets.
Future antiprotozoal development is increasingly directed toward compounds with novel mechanisms, activity against multiple parasite stages, improved pharmacokinetic profiles, and reduced toxicity. Long-acting formulations and transmission-blocking therapies may also contribute to disease-control strategies. The discovery of stage-specific vulnerabilities, parasite-specific enzymes, and previously underexplored cellular pathways provides opportunities for developing treatments capable of addressing resistant organisms and persistent infection.
Characteristics of antibiotics
An ideal antibiotic is not defined simply by its ability to kill bacteria. Its therapeutic value depends on a combination of microbiological activity, pharmacological behavior, safety, accessibility, stability, and clinical effectiveness. Once administered to a patient, an antibiotic must reach the infected compartment in an adequate concentration, interact preferentially with bacterial targets, remain sufficiently active for an appropriate period, and ultimately be eliminated without producing unacceptable harm.
An ideal antibiotic combines selective toxicity, appropriate antimicrobial spectrum, effective tissue penetration, pharmacological stability, adequate potency, predictable disposition, tolerability, accessibility, and a relatively low propensity for resistance selection. These characteristics should be considered collectively rather than as isolated requirements.
The ultimate objective of antibacterial therapy is to achieve reliable pathogen control while minimizing toxicity, ecological disruption, resistance selection, and unnecessary treatment burden. The following characteristics describe the major properties expected of an effective and clinically useful antibacterial agent.
1. Selective toxicity
Selective toxicity is one of the fundamental requirements of antimicrobial chemotherapy. An antibiotic should preferentially damage or inhibit bacterial cells while producing minimal injury to the cells and tissues of the host. This selectivity is possible because bacteria possess structural and biochemical features that differ from those of human cells. Examples include peptidoglycan-containing cell walls, bacterial ribosomes, specific DNA-processing enzymes, and metabolic pathways that are absent or substantially different in humans.
The degree of selective toxicity is influenced by the antibiotic’s mechanism of action, dose, distribution, and duration of exposure. A drug that strongly inhibits bacterial growth but also interferes with essential human cellular processes may have limited therapeutic usefulness. The desirable antimicrobial agent should provide a sufficiently large therapeutic index, allowing effective concentrations to be achieved against the pathogen without producing clinically unacceptable toxicity.
2. Appropriate spectrum of activity
An antibiotic should possess an appropriate spectrum of antibacterial activity for the suspected or confirmed pathogen. A broad-spectrum antibiotic can act against organisms belonging to several bacterial groups, whereas a narrow-spectrum agent is directed toward a more restricted collection of microorganisms. Neither characteristic is inherently sufficient by itself; the appropriate spectrum depends on the clinical and microbiological circumstances.
When the causative organism is known, a targeted narrow-spectrum agent can reduce unnecessary exposure of unrelated microorganisms. In contrast, empirical treatment of a serious infection may initially require broader coverage when the pathogen has not yet been identified. Microbiological culture and antimicrobial susceptibility testing can subsequently permit modification of therapy toward a more specific agent.
An appropriate spectrum should therefore provide effective pathogen coverage without unnecessary antimicrobial exposure. Excessively broad treatment can disturb the host microbiota and contribute to selection pressure favoring resistant organisms.
3. Preservation of the normal microbiota
The human body supports diverse microbial communities on the skin, gastrointestinal tract, oral cavity, respiratory tract, and other anatomical sites. These organisms can contribute to colonization resistance, metabolic functions, immune development, and maintenance of ecological stability. An ideal antibiotic should therefore minimize unnecessary disruption of the normal microbiota.
Antibiotic-associated alterations of microbial communities can create opportunities for opportunistic organisms to proliferate and may contribute to complications such as Clostridioides difficile infection. Broad-spectrum agents may produce greater ecological disturbance because they affect susceptible organisms that are unrelated to the original pathogen.
Selective antimicrobial therapy, appropriate dosing, and the shortest effective duration can help reduce unnecessary microbiological disruption. The objective is not necessarily to preserve every microorganism but to achieve sufficient pathogen control while limiting collateral effects on beneficial or protective microbial populations.
4. Specificity and effective delivery to the infection site
An effective antibiotic must reach the site of infection in an active concentration. Microbiological potency demonstrated in laboratory testing does not automatically guarantee clinical success. The drug must be absorbed, distributed through relevant tissues or compartments, and maintained at concentrations capable of inhibiting or eliminating the pathogen.
Pharmacokinetic properties such as absorption, distribution, metabolism, protein binding, and elimination determine the amount of active drug available at the infected site. Some anatomical barriers, including the blood–brain barrier, can restrict penetration into particular tissues. Similarly, abscesses, necrotic tissue, biofilms, and poorly perfused regions may limit antimicrobial exposure.
An ideal antibiotic should therefore demonstrate favorable tissue penetration and compartmental distribution. Whenever possible, its pharmacological properties should allow convenient administration while maintaining effective concentrations at the anatomical location where bacterial replication occurs.
5. Adequate potency at therapeutic concentrations
Antibiotics should retain sufficient antibacterial activity after administration and remain effective at concentrations that can safely be achieved in the patient. The drug should be capable of producing a meaningful pharmacodynamic effect despite dilution within blood, extracellular fluid, and other biological compartments.
The relationship between antimicrobial concentration and bacterial response is commonly described using parameters such as the minimum inhibitory concentration (MIC) and minimum bactericidal concentration (MBC). Clinical pharmacology also considers exposure measures such as the area under the concentration–time curve, peak concentration, and the duration for which drug levels remain above the MIC.
An effective antibiotic should therefore possess an appropriate pharmacokinetic-pharmacodynamic profile. Its concentration at the infection site should be sufficient to inhibit or eradicate the pathogen without requiring doses that create unacceptable toxicity.
6. Chemical and biological stability in vivo
An antibiotic should remain chemically intact and microbiologically active long enough to perform its therapeutic function. Premature degradation, enzymatic inactivation, excessive metabolic transformation, or rapid removal from the body can reduce effective exposure.
Some antibiotics are vulnerable to degradation under particular physiological conditions, whereas others may be modified by host enzymes or bacterial resistance mechanisms. A desirable compound should possess adequate stability within relevant biological environments and should maintain its active configuration during the period required for treatment.
Prolonged persistence is not automatically advantageous. Excessive retention may increase toxicity or produce unnecessary antimicrobial exposure. The desired characteristic is therefore controlled persistence: the drug should remain active for an appropriate therapeutic interval and subsequently undergo predictable elimination.
7. Favorable pharmacokinetic properties
The ideal antibiotic should have predictable pharmacokinetics and a dosing regimen that can reliably maintain therapeutic exposure. Absorption should be adequate when oral administration is appropriate, while intravenous or other routes should be available when rapid or reliable systemic exposure is required.
The compound should also have predictable distribution, metabolism, and elimination. Renal or hepatic impairment may alter drug exposure, making dose adjustment necessary for some agents. Drug-drug interactions should be limited whenever possible, particularly in patients receiving multiple medications.
A convenient pharmacokinetic profile can improve treatment adherence. An antibiotic requiring unnecessarily frequent administration may increase the likelihood of missed doses, whereas an appropriately designed formulation may simplify therapy.
8. Limited adverse effects and allergic reactions
An antibiotic should have a favorable safety profile. Although no pharmacologically active compound is completely free of adverse effects, undesirable reactions should be infrequent, predictable, and manageable relative to the therapeutic benefit. Potential adverse effects may involve the gastrointestinal tract, liver, kidneys, nervous system, blood-forming tissues, or other organs.
Some antibiotics can also produce hypersensitivity reactions ranging from mild skin manifestations to severe systemic responses. The possibility of toxicity becomes particularly important when prolonged treatment, high doses, or vulnerable patient populations are involved.
A clinically useful antibiotic should therefore provide an appropriate balance between antimicrobial efficacy and host tolerance. Patient-specific factors such as age, pregnancy, renal function, hepatic function, allergy history, and concomitant medications should be considered when selecting therapy.
9. Low propensity for resistance development
An important characteristic of an effective antibiotic is a low tendency to select or promote clinically significant resistance. Bacterial populations can develop resistance through spontaneous genetic changes, horizontal gene transfer, target modification, enzymatic drug inactivation, reduced permeability, or active efflux.
No antibiotic can be expected to remain permanently unaffected by bacterial evolution. Nevertheless, agents with novel mechanisms, appropriate target specificity, and pharmacological characteristics that reduce prolonged subtherapeutic exposure may contribute to more sustainable therapy.
Antimicrobial stewardship is essential in this context. Correct drug selection, appropriate dosing, microbiological diagnosis, and avoidance of unnecessary treatment can reduce selective pressure. Combination therapy may also be useful for particular infections in which resistance can emerge rapidly, although combining drugs is not universally necessary or appropriate.
10. Compatibility with host immune defenses
Antibiotic therapy should work in concert with the host immune system rather than functioning as an isolated intervention. Antimicrobial drugs may reduce bacterial populations sufficiently to allow innate and adaptive immune mechanisms to complete pathogen clearance. This interaction is particularly important in patients with impaired immunity, where antimicrobial treatment may need to compensate for reduced host defense.
Some antibiotics are primarily bacteriostatic, inhibiting bacterial multiplication and allowing immune mechanisms to eliminate the remaining organisms, whereas bactericidal agents directly produce bacterial death. The clinical outcome therefore reflects an interaction between the antimicrobial agent, pathogen, infection site, and immune response.
11. Reasonable cost and accessibility
An antibiotic must also be economically and practically accessible. A highly effective drug has limited public-health value if its cost, availability, storage requirements, or administration demands prevent appropriate use. Affordable formulations can improve access to treatment, particularly where healthcare resources are limited. Availability should also include reliable manufacturing, appropriate storage conditions, adequate supply chains, and consistent product quality.
Cost should not be considered independently of clinical value. A less expensive drug may be unsuitable if the pathogen is resistant, whereas a more expensive agent may be necessary for a particular infection. The relevant principle is cost-effective antimicrobial therapy, in which expenditure is considered alongside efficacy, safety, resistance, administration, and patient outcomes.
12. Adequate shelf stability
An ideal antibiotic should possess sufficient chemical stability and shelf life to retain its potency during storage and distribution. Stability can be influenced by temperature, humidity, light, oxygen, formulation, and packaging. A drug that rapidly loses potency under ordinary storage conditions may become unreliable even if its intrinsic antibacterial activity is excellent. Stable formulations facilitate transportation, stock management, and routine clinical use. This is especially important in settings where refrigeration or specialized storage facilities may be unavailable.
References
Denyer S.P., Hodges N.A and Gorman S.P (2004). Pharmaceutical Microbiology. 7th ed. Blackwell Publishing Company, USA.
Fernandes Prabhavathi (2006). Antibacterial discovery – the failure of success? Nature Biotechnology, 24(12):1.
Finch R.G, Greenwood D, Norrby R and Whitley R (2002). Antibiotic and chemotherapy, 8th edition. Churchill Livingstone, London and Edinburg.
Hutchings, M. I., Truman, A. W., & Wilkinson, B. (2019). Antibiotics: Past, present and future. Current Opinion in Microbiology, 51, 72–80.
Katz, L., & Baltz, R. H. (2016). Natural product discovery: Past, present, and future. Journal of Industrial Microbiology & Biotechnology, 43, 155–176.
Clardy, J., Fischbach, M. A., & Currie, C. R. (2009). The natural history of antibiotics. Current Biology, 19(11), R437–R441.
Clardy, J., & Walsh, C. (2004). Lessons from natural molecules. Nature, 432, 829–837.
Currie, C. R. (2001). A community of ants, fungi, and bacteria: A multilateral approach to studying symbiosis. Annual Review of Microbiology, 55, 357–380.
Pancu, D. F., Scurtu, A., Macasoi, I. G., Marti, D., Mioc, M., Soica, C., Coricovac, D., Horhat, D., Poenaru, M., & Dehelean, C. (2021). Antibiotics: Conventional therapy and natural compounds with antibacterial activity—A pharmaco-toxicological screening. Antibiotics, 10(4), 401.
Discover more from Microbiology Class
Subscribe to get the latest posts sent to your email.