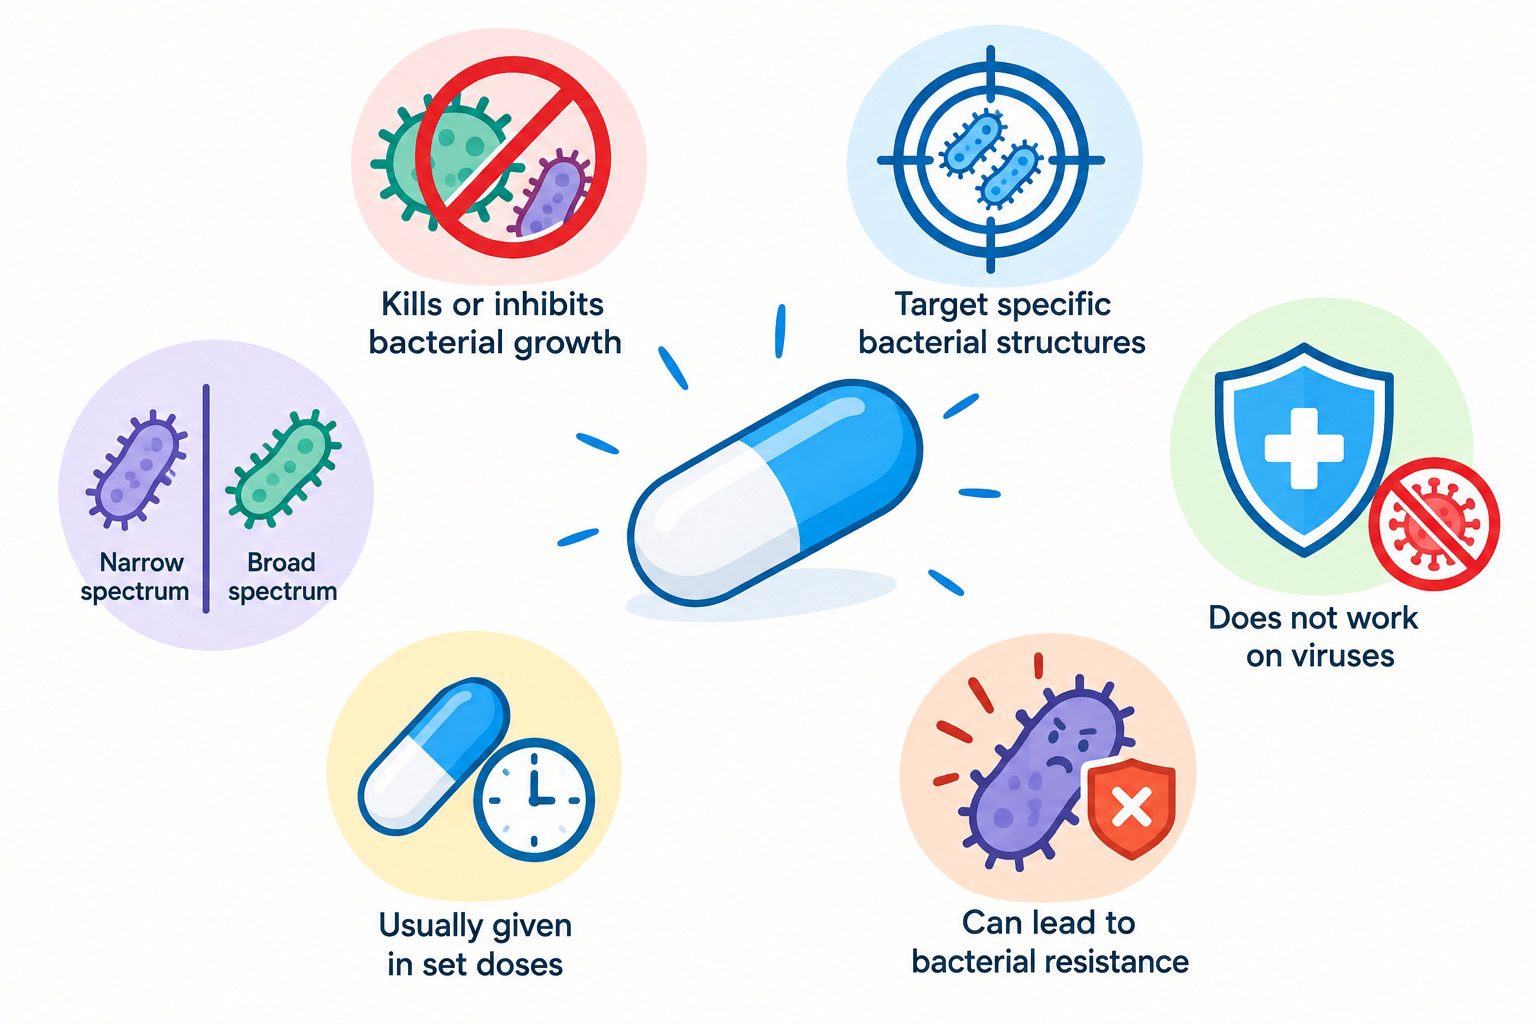
There is no universally accepted definition of an antibiotic, largely because the concept has evolved alongside advances in microbiology, pharmacology, and pharmaceutical chemistry. Till date, two fundamental concepts: killing and inhibition of microbial growth remain central to any meaningful definition of antibiotics. Historically, an antibiotic was defined as a substance produced by one microorganism that, even at low concentrations, inhibits the growth or destroys other microorganisms.
This early definition primarily referred to naturally occurring substances produced by microorganisms. However, advances in chemical synthesis and drug development have expanded the concept considerably. Today, an antibiotic may be broadly defined as a substance produced by a microorganism, either naturally or with subsequent chemical modification, which at relatively low concentrations can kill or inhibit the growth of susceptible microorganisms in vivo or in vitro.
The discovery of antibiotics and their subsequent introduction into clinical medicine represent one of the most significant scientific and medical achievements of the twentieth century. Often described as “magic bullets,” antibiotics have transformed the treatment and management of bacterial diseases and have contributed substantially to reductions in morbidity and mortality associated with bacterial infections.
Over the past several decades, antibiotics have been used extensively in the treatment of diseases such as tuberculosis (TB), pneumonia, gonorrhea, urinary tract infections (UTIs), respiratory tract infections, syphilis, and numerous other bacterial infections. Their effectiveness has made antibacterial therapy an essential component of modern clinical medicine, enabling the successful treatment of infections that were once associated with considerable morbidity and mortality.
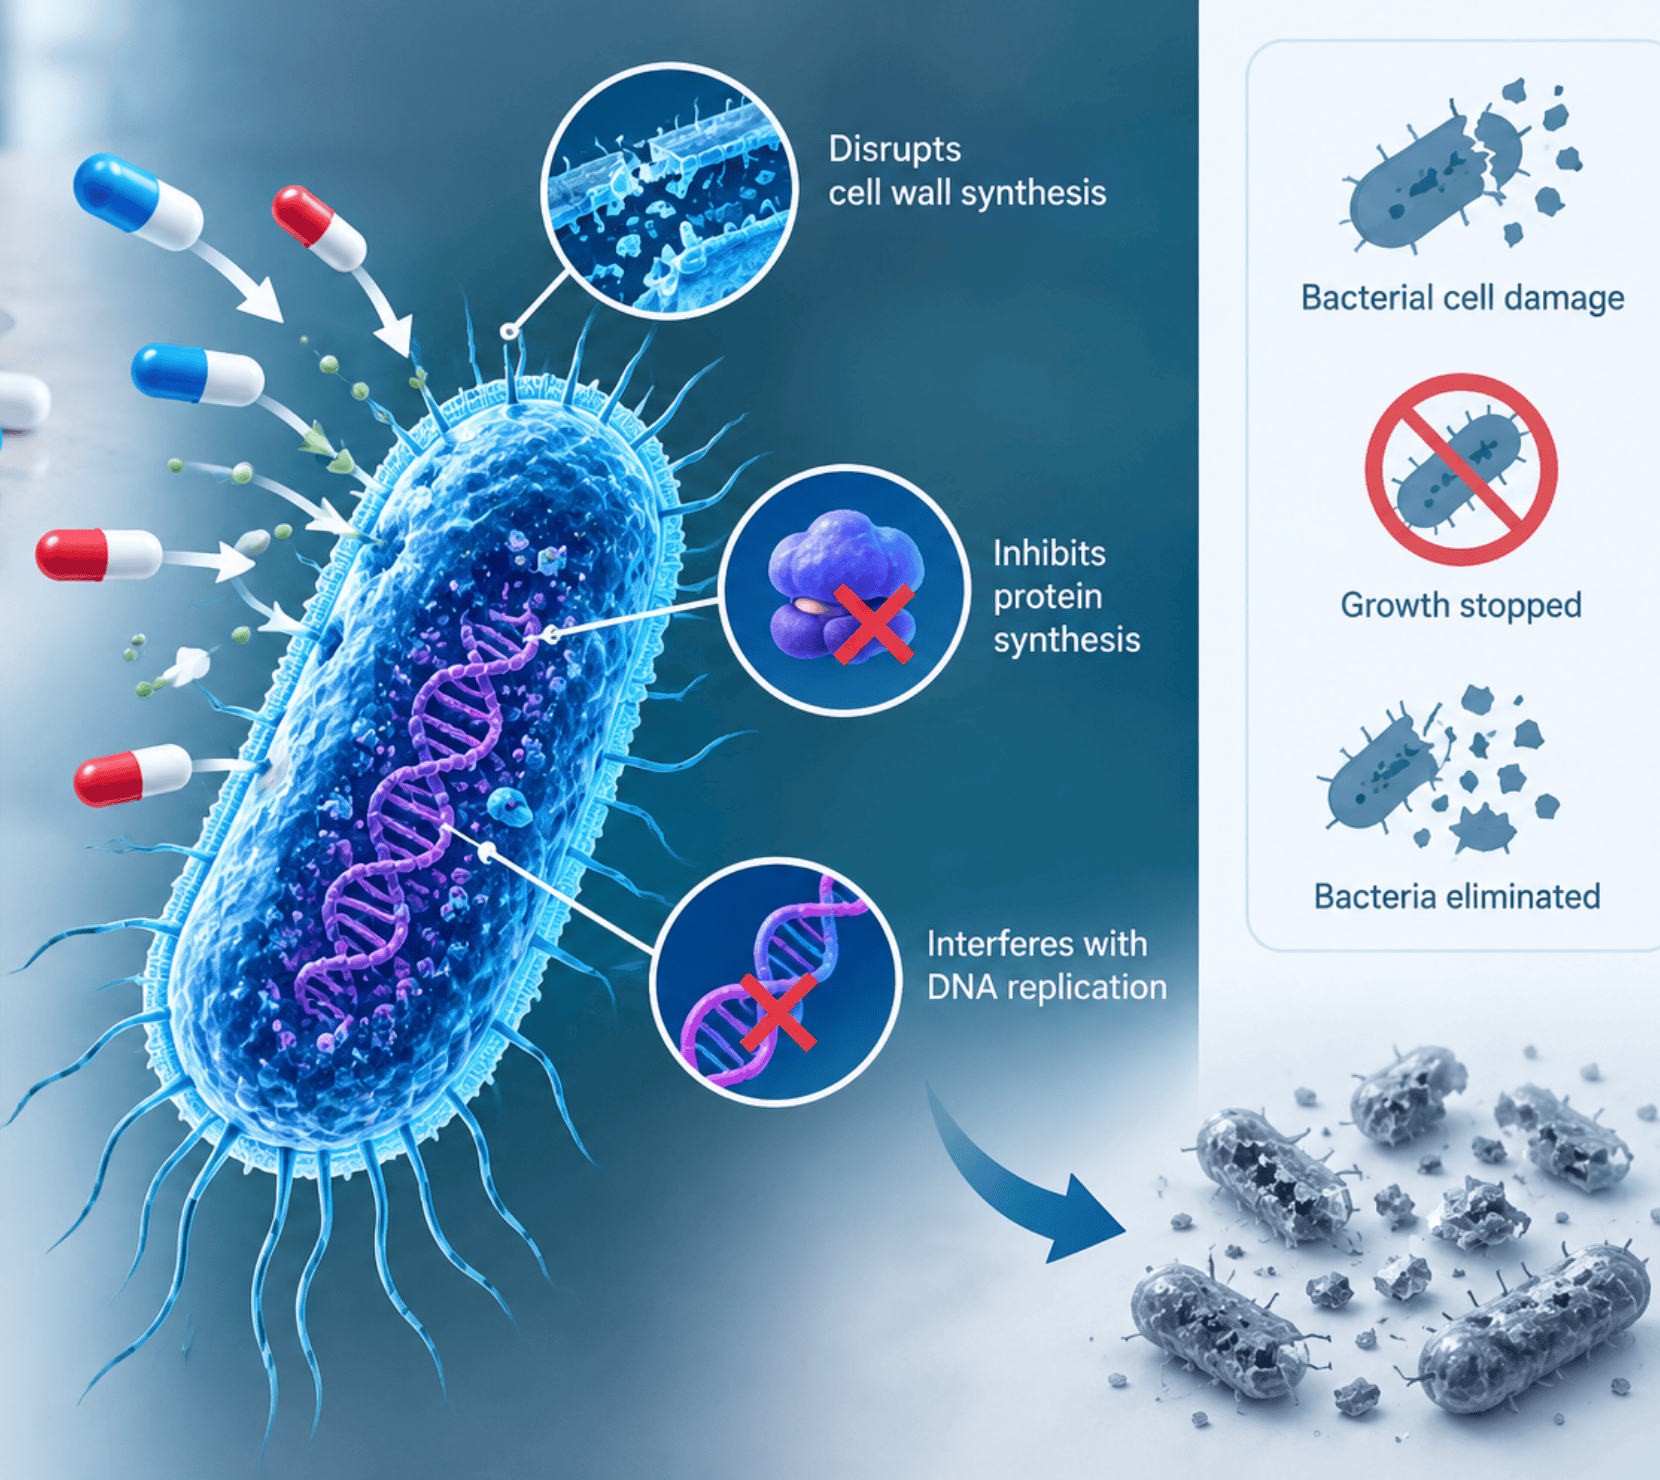
Antibiotics exert their therapeutic effects by selectively interfering with essential cellular processes in bacteria. Depending on their mechanism of action, they may inhibit cell-wall synthesis, disrupt protein synthesis, interfere with nucleic acid replication or transcription, alter cell membrane integrity, or inhibit essential metabolic pathways.
Based on their effects on bacterial cells, antibiotics are broadly classified as bactericidal or bacteriostatic. Bactericidal antibiotics directly kill susceptible bacteria, whereas bacteriostatic antibiotics primarily inhibit bacterial growth and multiplication, allowing the host immune system to eliminate the remaining organisms. The distinction, however, may vary depending on the bacterial species, antibiotic concentration, and site of infection.
Antibiotics also differ in their spectrum of activity. Broad-spectrum antibiotics are active against a relatively wide range of bacterial species, whereas narrow-spectrum antibiotics target a more limited group of bacteria. Selection of an appropriate antibiotic therefore depends on factors such as the causative organism, antimicrobial susceptibility, site and severity of infection, patient characteristics, pharmacokinetic properties, and potential adverse effects.
Despite their enormous therapeutic benefits, the effectiveness of antibiotics is increasingly threatened by antimicrobial resistance (AMR). The inappropriate use, misuse, overuse, and, in some circumstances, underuse of antibiotics in healthcare, agriculture, livestock and poultry production, and the wider environment have contributed to the emergence and spread of resistant microorganisms. Some previously effective antibiotics have become less reliable for treating infections.
Definition of antibiotics
Antibiotics are a specialized group of antimicrobial substances used primarily to combat infections caused by susceptible bacteria. They represent an essential component of modern medicine because they can selectively interfere with vital bacterial processes while, at appropriate concentrations, causing considerably less harm to human cells. Their use has transformed the management of bacterial diseases and has substantially improved the outcomes of many previously serious or life-threatening infections.
The term antibiotic traditionally refers to substances produced by microorganisms that inhibit or destroy other microorganisms. In contemporary pharmacology, the concept is broader and includes naturally derived compounds as well as chemically modified and fully synthetic antibacterial agents. Natural antibiotics may originate from organisms such as bacteria and fungi, whereas semisynthetic and synthetic drugs are developed or modified to improve characteristics such as potency, stability, absorption, tissue penetration, or resistance to bacterial defense mechanisms.
A defining feature of antibiotics is their activity against bacterial pathogens. They can target structures or biochemical pathways that are essential for bacterial survival and multiplication. Depending on their pharmacological properties, antibiotics may interfere with bacterial cell-wall formation, protein production, nucleic-acid replication, metabolic reactions, or other cellular functions. This targeted activity provides the foundation for their therapeutic application in conditions such as bacterial pneumonia, urinary tract infections, bacterial skin infections, and certain bloodstream infections.
Antibiotics are not generally effective against viral infections. Viruses differ fundamentally from bacteria because they depend heavily on host cells for replication and do not possess many of the cellular structures targeted by antibacterial medicines. Using an antibiotic for an uncomplicated viral illness does not normally accelerate recovery and may expose the patient to unnecessary adverse effects while contributing to the development of antimicrobial resistance.
Antibiotics can also be distinguished according to their effect on bacterial cells. Bactericidal antibiotics directly kill susceptible bacteria, whereas bacteriostatic antibiotics primarily inhibit bacterial growth and reproduction, allowing the body’s immune system to eliminate the restrained organisms. The distinction is clinically relevant, although the response may vary according to the microorganism, drug concentration, infection site, and patient’s immune status.
Antibiotics are pharmacologically active agents designed to control bacterial disease through selective interference with essential microbial functions. Their effectiveness depends not only on the intrinsic activity of the drug but also on appropriate selection, dosage, administration, and duration of therapy. Responsible antibiotic use is therefore fundamental to achieving therapeutic benefit while limiting adverse reactions and the emergence of resistant bacterial strains.
Characteristics of antibiotics
Antibiotics are pharmacologically active substances distinguished by their ability to interfere with essential biological processes in susceptible bacteria. Their clinical usefulness depends not only on their ability to inhibit or eliminate bacterial pathogens but also on their selectivity, concentration, mechanism of action, spectrum, and safety profile.
1. Selective Toxicity: A fundamental characteristic of antibiotics is selective toxicity, meaning that the drug is designed to damage bacterial cells more than the cells of the human host. This selectivity is possible because bacteria possess structures and biochemical pathways that differ from those of human cells. For example, certain antibiotics target bacterial cell-wall synthesis, a process absent in human cells. Others act on bacterial ribosomes or metabolic pathways. Selective toxicity is relative rather than absolute, and some antibiotics can still affect host tissues or produce unwanted reactions.
2. Therapeutic effectiveness: Antibiotics must achieve sufficient concentrations at the site of infection to exert their intended biological effect. Their effectiveness is influenced by factors such as absorption, distribution, metabolism, elimination, tissue penetration, and the susceptibility of the infecting organism. The relationship between drug concentration and bacterial susceptibility is therefore important when determining an appropriate dosage regimen. Maintaining adequate exposure helps suppress bacterial growth or produce bacterial killing while limiting unnecessary toxicity.
3. Specific mechanisms of action: Each antibiotic class acts through one or more defined molecular targets. Some inhibit the formation of the bacterial cell wall, whereas others interfere with protein synthesis, nucleic-acid replication, or essential metabolic reactions. Because these mechanisms differ among drug classes, antibiotics may have distinct clinical applications and resistance profiles. Knowledge of the mechanism of action also helps explain why a particular antibiotic is appropriate for a specific bacterial infection.
4. Variation in antibacterial spectrum: Antibiotics vary considerably in the range of bacteria they affect. A narrow-spectrum antibiotic acts against a relatively limited group of organisms, whereas a broad-spectrum antibiotic can affect a wider range of bacterial species. Spectrum selection should correspond as closely as possible to the suspected or confirmed pathogen. Appropriate spectrum selection can reduce unnecessary exposure of other microorganisms and may help limit the development of antimicrobial resistance.
5. Potential for adverse effects: Although antibiotics are intended to act selectively on bacteria, they may produce undesirable effects in patients. Common reactions can include gastrointestinal disturbances, skin manifestations, or localized irritation, depending on the drug and route of administration. Some agents can produce more serious organ-specific toxicity. The likelihood and severity of adverse effects vary between antibiotic classes and individual patients.
6. Possibility of hypersensitivity reactions: Certain antibiotics can trigger immune-mediated reactions, ranging from mild skin eruptions to severe hypersensitivity. A patient’s previous history of antibiotic allergy is therefore clinically relevant when selecting therapy. Careful assessment of suspected allergies can help distinguish genuine hypersensitivity from non-allergic adverse reactions and support safer antimicrobial selection.
Classification of antibiotics
Antibiotics constitute a diverse group of antimicrobial medicines that differ substantially in their chemical structures, antibacterial spectra, pharmacological properties, and mechanisms of action. Classifying antibiotics into major groups provides a systematic framework for understanding how individual agents act against bacterial pathogens and why particular drugs are selected for specific infections. The principal classes include penicillins, cephalosporins, macrolides, tetracyclines, aminoglycosides, and fluoroquinolones. Each class possesses characteristic properties that influence its clinical application.
Penicillins: Penicillins are β-lactam antibiotics characterized by the presence of a β-lactam ring. Their principal antibacterial effect arises from interference with bacterial cell-wall synthesis. By binding to penicillin-binding proteins (PBPs), these agents impair the formation of peptidoglycan, an essential structural component of the bacterial cell wall. This ultimately promotes bacterial cell disruption, particularly in actively dividing organisms.
Examples of penicillins include amoxicillin, penicillin V, and ampicillin. Penicillins are widely used for susceptible respiratory, urinary, gastrointestinal, and skin infections. Their therapeutic usefulness may be limited by bacterial production of β-lactamases, enzymes capable of inactivating certain β-lactam antibiotics. Some penicillins are combined with β-lactamase inhibitors to extend antibacterial coverage.
Cephalosporins: Cephalosporins are another important β-lactam family and are structurally related to penicillins. They interfere with bacterial cell-wall construction by targeting PBPs. Their classification into generations reflects differences in antibacterial spectrum and pharmacological characteristics. Examples of cephalosporins include cefalexin, cefuroxime, ceftriaxone, and cefepime.
Earlier-generation cephalosporins generally demonstrate substantial activity against Gram-positive organisms, whereas later generations often provide broader activity against selected Gram-negative bacteria. Cephalosporins are used in numerous clinical settings, including respiratory infections, urinary tract infections, skin infections, and serious systemic bacterial infections.
Macrolides: Macrolides possess a distinctive macrocyclic lactone structure and primarily inhibit bacterial protein production. They bind to the 50S ribosomal subunit, interfering with peptide elongation and consequently restricting bacterial growth. Common examples include azithromycin, erythromycin, and clarithromycin.
Macrolides are particularly useful against several respiratory pathogens and certain atypical bacteria. They can also serve as alternatives for patients who cannot receive particular β-lactam antibiotics. Their use requires attention to potential drug interactions and adverse effects, including gastrointestinal disturbances and, with some agents, cardiac rhythm abnormalities.
Tetracyclines: Tetracyclines are broad-spectrum antibiotics that inhibit bacterial protein synthesis by binding to the 30S ribosomal subunit. This action prevents the attachment of aminoacyl-tRNA to the bacterial ribosome, thereby interrupting protein production. Doxycycline, tetracycline, and minocycline are representative members of the tetracyclines.
Tetracyclines have applications in several respiratory, dermatological, vector-borne, and sexually transmitted bacterial infections. Their absorption can be reduced when taken with certain minerals, particularly calcium, magnesium, and iron. Specific tetracyclines also have age- and pregnancy-related restrictions because of potential effects on developing teeth and bones.
Aminoglycosides: Aminoglycosides are potent antibiotics that act primarily on the 30S ribosomal subunit, producing errors in bacterial protein synthesis. Their antibacterial action is generally bactericidal and is particularly important against many aerobic Gram-negative organisms. Examples of aminoglycosides include gentamicin, amikacin, and tobramycin.
Because these medicines can produce significant nephrotoxicity and ototoxicity, their administration often requires careful dosage adjustment and monitoring, especially during prolonged treatment or in patients with impaired renal function. Aminoglycosides are therefore commonly reserved for specific clinical circumstances where their antibacterial properties provide substantial therapeutic value.
Fluoroquinolones: Fluoroquinolones are synthetic antibacterial agents that interfere with bacterial DNA replication. They inhibit essential enzymes such as DNA gyrase and topoisomerase IV, preventing normal chromosome replication and repair. Representative drugs that are fluoroquinolone include ciprofloxacin, levofloxacin, and moxifloxacin.
Their activity encompasses numerous Gram-negative and selected Gram-positive pathogens, although their clinical use has become more selective because of bacterial resistance and potentially serious adverse effects. Tendon injury, peripheral neuropathy, and effects on the central nervous system are among the important safety considerations associated with this class.
Mechanisms of action of antibiotics
Antibiotics exert their therapeutic effects by interfering with biological processes that are essential for bacterial survival, multiplication, or structural integrity. Although different antibiotic classes act through distinct molecular targets, their common objective is to exploit differences between bacterial cells and human cells.
This selective toxicity allows an antibiotic to inhibit or destroy pathogenic bacteria while causing comparatively limited damage to the host. The principal mechanisms involve interference with bacterial cell-wall construction, protein production, nucleic-acid metabolism, essential biochemical pathways, and membrane integrity.
The diversity of antibiotic mechanisms allows clinicians to select treatments according to the suspected or confirmed bacterial pathogen, site of infection, susceptibility profile, and patient-specific considerations. Bacteria may alter target structures, produce drug-inactivating enzymes, reduce drug entry, or increase drug efflux, thereby weakening the activity of particular antibiotics.
Effective antibacterial therapy involves more than simply selecting a drug that can inhibit bacteria. Appropriate antimicrobial selection requires consideration of the organism, mechanism of action, susceptibility, pharmacological properties, infection site, dosage, and potential adverse effects.
1. Inhibition of bacterial cell-wall synthesis
The bacterial cell wall provides mechanical strength and protects bacteria from osmotic rupture. Its major structural component is peptidoglycan, a polymer that forms a strong network around the bacterial cytoplasmic membrane. Because human cells do not possess peptidoglycan cell walls, this structure provides an important target for selective antibacterial therapy.
Some antibiotics interfere with different stages of peptidoglycan formation. β-lactam antibiotics, including penicillins, cephalosporins, and related agents, bind to bacterial enzymes involved in the final stages of cell-wall assembly. This prevents proper cross-linking of the peptidoglycan structure and weakens the cell wall. Growing bacteria may subsequently undergo cell lysis, particularly when exposed to concentrations sufficient to inhibit cell-wall construction.
Other agents, such as glycopeptide antibiotics, interfere with the incorporation of peptidoglycan building blocks into the developing cell wall. The precise target and stage of inhibition vary among drug classes. The effectiveness of these agents is therefore influenced by bacterial species, growth rate, and the structural characteristics of the organism.
2. Inhibition of bacterial protein synthesis
Proteins are essential for virtually every aspect of bacterial physiology, including metabolism, replication, transport, and cellular repair. Bacteria manufacture proteins using ribosomes that differ structurally from those found in human cells. Antibiotics can exploit these differences by binding to bacterial ribosomal subunits and interfering with translation.
Some antibiotics bind to the 30S ribosomal subunit and interfere with the accurate reading of messenger RNA or the incorporation of amino acids into newly forming proteins. Others act primarily on the 50S subunit and inhibit peptide-chain formation or movement along the messenger RNA template. By disrupting translation, these drugs reduce the production of proteins required for bacterial growth and maintenance.
Depending on the antibiotic and its concentration, inhibition of protein synthesis may primarily suppress bacterial multiplication or contribute to bacterial death. The clinical activity of these agents also depends on the susceptibility of the infecting organism and the drug’s ability to reach adequate concentrations at the site of infection.
3. Interference with DNA and RNA synthesis
Bacterial survival depends on accurate replication and expression of genetic information. Antibiotics can target enzymes involved in DNA replication, DNA repair, or RNA transcription. Interference with these processes prevents bacteria from reproducing normally and can produce extensive cellular damage.
For example, fluoroquinolones interfere with bacterial enzymes involved in controlling DNA structure during replication. By disrupting these enzymes, they prevent normal chromosome duplication and can generate lethal DNA damage. Other antibacterial agents interfere with bacterial RNA polymerase, an enzyme required for transcription.
Blocking transcription prevents the production of messenger RNA and consequently limits the synthesis of essential proteins. These mechanisms illustrate how antibiotics can affect bacteria at the genetic and molecular levels without directly attacking human DNA. Their use must be guided by bacterial susceptibility, appropriate dosing, and consideration of potential adverse effects.
4. Disruption of essential metabolic pathways
Certain bacteria depend on biochemical pathways that are either absent from human cells or sufficiently different to permit selective inhibition. Antibiotics can exploit these metabolic differences by blocking enzymes required for the synthesis of essential cellular compounds.
A classic example involves the bacterial production of folate-related metabolites. Bacteria require these compounds for processes such as nucleotide synthesis and cellular growth, while humans obtain folate primarily through the diet. Drugs that interfere with bacterial folate metabolism can therefore restrict the organism’s ability to produce essential cellular components.
This mechanism is particularly important because metabolic inhibition does not necessarily destroy the bacterial cell immediately. Instead, it can create a biochemical deficiency that prevents continued growth and reproduction. The therapeutic outcome depends on the drug concentration, bacterial susceptibility, and ability of the host to tolerate the treatment.
5. Disruption of bacterial cell-membrane integrity
The bacterial cell membrane regulates the movement of ions and molecules into and out of the cell and contributes to energy production and cellular homeostasis. Certain antibiotics act directly on this membrane, altering its permeability or physical organization.
Membrane-active antibiotics can cause leakage of essential intracellular components and disturb electrochemical gradients required for normal cellular function. Severe membrane damage may rapidly compromise bacterial metabolism and lead to cell death. Because membrane integrity is fundamental to survival, these agents can demonstrate potent antibacterial activity against susceptible organisms.
Membrane-targeting mechanisms require careful therapeutic consideration because compounds capable of interacting strongly with biological membranes may also produce toxicity in human tissues. Their clinical application therefore depends on achieving an appropriate balance between antibacterial activity and host safety.
Therapeutic applications of antibiotics in clinical practice
Antibiotics constitute a major component of modern antimicrobial therapy and are employed primarily to manage infections caused by susceptible bacteria. Their therapeutic application depends on the causative organism, anatomical site of infection, severity of disease, antimicrobial susceptibility, and individual patient factors. Appropriate selection is essential because different antibiotics possess distinct spectra of activity, tissue penetration, pharmacokinetic properties, and safety profiles.
Antibiotics have an important prophylactic role in selected surgical procedures. Perioperative administration can reduce the likelihood of infection when a procedure carries a recognized risk of bacterial contamination. Prophylactic antibiotics are generally administered at an appropriate time before or around the procedure and are not intended to substitute for sterile technique or other infection-prevention measures. Their use should remain targeted to situations in which the expected preventive benefit outweighs the risks of antimicrobial exposure.
Antibiotics are applied or used to treat several bacterial (microbial) infections as follows:
Respiratory bacterial infections represent an important area of antibiotic therapy. Bacterial conditions such as community-acquired pneumonia, certain cases of bacterial sinusitis, streptococcal pharyngitis, and selected exacerbations of chronic respiratory disease may require antimicrobial treatment. The choice of agent is influenced by the suspected pathogen and local resistance patterns. Effective therapy aims to eliminate the infecting organism while limiting unnecessary exposure to antibiotics.
Urinary tract infections (UTIs) are another common indication. Antibiotics may be prescribed for bacterial cystitis, complicated urinary infections, and, when appropriate, infections involving the kidneys. Selection depends on factors such as the location and severity of infection, previous antimicrobial exposure, renal function, and susceptibility results. In recurrent or complicated cases, microbiological investigation can assist in identifying an appropriate therapeutic option.
Skin and soft-tissue infections may also require antimicrobial intervention. Conditions including bacterial cellulitis, infected wounds, abscesses, and certain postoperative infections can involve organisms such as Staphylococcus aureus and Streptococcus species. Management may combine antibiotic therapy with procedures such as drainage when a localized collection of pus is present. The extent and depth of infection influence the route and duration of treatment.
Gastrointestinal bacterial infections constitute another therapeutic category. Certain bacterial forms of enteritis, dysentery, cholera, and other gastrointestinal infections may benefit from antibiotics, although antimicrobial treatment is not necessary for every episode of bacterial diarrhea. Clinical assessment is important because inappropriate treatment can expose patients to adverse effects without providing meaningful benefit.
Sexually transmitted bacterial infections are treated with antibiotics selected according to the identified or suspected pathogen. Conditions such as chlamydia, gonorrhea, and syphilis require specific antimicrobial regimens. Prompt treatment can reduce symptoms, prevent complications, and decrease transmission to sexual partners. Partner management and follow-up testing may also form part of comprehensive care.
Routes of administration of antibiotics
The route of administration of an antibiotic determines how an antibiotic enters the body, reaches the site of infection, and produces its therapeutic effect. Selection of an appropriate route depends on the location and severity of infection, the patient’s clinical condition, the pharmacokinetic properties of the drug, and the ability of the patient to tolerate or absorb medication. Antibiotics may be administered through enteral, parenteral, or localized routes.
1. Oral administration: Oral therapy is commonly used when the patient is clinically stable and the antibiotic has adequate gastrointestinal absorption. Tablets, capsules, suspensions, and other oral formulations provide a convenient and relatively inexpensive method of treatment. Oral antibiotics are particularly useful for mild to moderate infections and for continuing therapy after initial parenteral treatment. However, absorption may be influenced by food, gastric conditions, intestinal disorders, or interactions with other medicines. Poor adherence to the prescribed dosage schedule may also reduce treatment effectiveness.
2. Intravenous administration: Intravenous administration delivers the antibiotic directly into the bloodstream, producing rapid and predictable systemic exposure. This route is frequently selected for severe, complicated, or life-threatening bacterial infections, especially when immediate therapeutic concentrations are required. It is also valuable when oral administration is unsuitable because of vomiting, impaired consciousness, gastrointestinal dysfunction, or inadequate absorption. Intravenous therapy requires appropriate clinical monitoring because incorrect administration can result in complications such as phlebitis, infiltration, or medication-related adverse reactions.
3. Intramuscular administration: Intramuscular injection introduces the antibiotic into muscle tissue, from which the drug is gradually absorbed into systemic circulation. This approach can be useful when oral treatment is inappropriate and intravenous access is unnecessary or unavailable. Certain long-acting antibiotic formulations are specifically designed for intramuscular use, allowing sustained drug exposure. Injection-site discomfort, inflammation, or localized tissue reactions may occur following administration.
4. Topical administration: Topical antibiotics are applied directly to affected skin or superficial tissues. This route can provide a high concentration of the medication at the treatment site while limiting systemic exposure. It may be employed for selected localized bacterial skin conditions, minor wounds, or superficial infections. Appropriate selection is important because topical therapy is not suitable for deep, extensive, or systemic infections.
5. Ophthalmic and otic administration: Ophthalmic antibiotics are formulated for application to the eyes, whereas otic preparations are designed for the external or middle ear when clinically appropriate. These localized routes deliver medication directly to the affected anatomical site and are useful for selected bacterial eye or ear infections. Sterility, formulation compatibility, and correct administration technique are essential to minimize irritation and prevent contamination.
Adverse effects and precautions associated with antibiotic therapy
Antibiotics should be used according to appropriate clinical guidance. The choice of agent, dosage, treatment duration, and administration route should correspond to the suspected or confirmed bacterial infection and the patient’s clinical circumstances. Responsible use reduces preventable complications and supports effective antimicrobial therapy. Self medication with antibiotics should be avoided as much as is possible.
Antibiotics are essential therapeutic agents for managing bacterial infections, but their administration requires careful consideration of potential adverse effects and patient-specific precautions. Although many antibiotics are well tolerated, unwanted reactions may occur depending on the drug, dose, duration of therapy, route of administration, and individual patient characteristics.
Gastrointestinal disturbances are among the most frequently encountered adverse effects. Patients may experience nausea, abdominal discomfort, vomiting, loose stools, or diarrhea. These effects can result from direct gastrointestinal irritation or disruption of the normal intestinal microbiota. Persistent or severe diarrhea during or after antibiotic therapy requires medical evaluation because it may indicate an antibiotic-associated intestinal infection.
Hypersensitivity reactions represent another important concern. Mild manifestations may include itching, urticaria, or localized skin eruptions, whereas severe reactions can involve facial swelling, breathing difficulty, or anaphylaxis. Patients with a documented allergy to a particular antibiotic or related drug class should inform healthcare professionals before treatment begins.
Cutaneous reactions may range from mild rashes to more serious dermatological conditions. New or rapidly progressing skin abnormalities during therapy should therefore be assessed promptly rather than being dismissed as a routine side effect.
Drug interactions can influence both the effectiveness and safety of treatment. Certain antibiotics may alter the metabolism or activity of other medicines, potentially increasing toxicity or reducing therapeutic efficacy. A complete medication history, including non-prescription medicines and supplements, is therefore important.
Some antibiotics may produce organ-specific toxicity, particularly when used at high doses or in vulnerable patients. Depending on the drug, the kidneys, liver, nervous system, hearing apparatus, or bone marrow may be affected. Dose adjustment and laboratory monitoring may be necessary for selected patients.
Antibiotic resistance and rational therapy
In the era of increasing antibiotic resistance, evidence-based antimicrobial therapy can contribute to mitigating the emergence and spread of resistance. Antibiotic resistance is a major challenge in modern healthcare because bacteria can adapt to antimicrobial exposure and gradually develop mechanisms that reduce or eliminate the effectiveness of medicines. Resistance may emerge when antibiotics are used unnecessarily, incorrectly, or for inappropriate durations. It can also arise naturally through genetic changes and the transfer of resistance genes between bacteria. Once resistant organisms become established, infections may require alternative medicines, prolonged treatment, or more intensive clinical management.
Rational antibiotic therapy is therefore based on using an antimicrobial agent only when there is a clear clinical indication. Antibiotics should not be routinely used for conditions caused by viruses, such as many uncomplicated respiratory infections, because antibacterial medicines do not act against viral pathogens. Avoiding unnecessary exposure reduces selective pressure on bacterial populations and helps limit the emergence and spread of resistant strains.
An important principle of rational therapy is appropriate drug selection. The chosen antibiotic should have activity against the suspected or confirmed pathogen while providing adequate penetration into the infected tissue. Clinicians may initially select treatment empirically when the causative organism is not yet known. Once laboratory information becomes available, therapy can be modified to a narrower and more targeted agent when appropriate. This approach can reduce unnecessary exposure to broad-spectrum antibiotics.
The dose and route of administration are equally important. An insufficient dose may fail to achieve effective concentrations at the site of infection and can contribute to treatment failure. Conversely, excessive dosing may increase the risk of toxicity without providing additional therapeutic benefit. The route of antibiotic administration (oral, intravenous, intramuscular, topical, or another formulation) should be selected according to the severity and location of infection, the patient’s clinical condition, and the pharmacological properties of the medicine.
The duration of treatment should also be carefully considered. Antibiotics should generally be administered for a duration supported by clinical evidence and appropriate treatment guidelines. Extending therapy unnecessarily can increase adverse effects and antimicrobial selection pressure. At the same time, treatment should not be shortened without appropriate clinical justification, particularly when the infection requires sustained antimicrobial exposure.
Laboratory investigations can strengthen antibiotic selection. Culture and antimicrobial susceptibility testing can identify the organism responsible for an infection and determine which antibiotics are likely to be effective. These results are particularly valuable in severe, recurrent, healthcare-associated, or treatment-resistant infections. They can allow clinicians to replace broad empirical therapy with a more specific antimicrobial regimen.
Antibiotic stewardship provides a structured framework for promoting responsible antimicrobial use. Stewardship programs encourage accurate diagnosis, appropriate prescribing, review of ongoing therapy, dose optimization, and de-escalation when laboratory findings permit. They also promote surveillance of resistance patterns and education of healthcare professionals and patients.
Rational antibiotic therapy requires balancing effective infection control with the preservation of antimicrobial activity for future patients. Appropriate diagnosis, evidence-based drug selection, optimized dosing, microbiological testing, and responsible treatment duration collectively reduce avoidable antimicrobial exposure. These practices help maintain the clinical usefulness of existing antibiotics while supporting safer and more sustainable infection management.
References
Ashutosh Kar (2008). Pharmaceutical Microbiology, 1st edition. New Age International Publishers: New Delhi, India.
Denyer S.P., Hodges N.A and Gorman S.P (2004). Pharmaceutical Microbiology. 7th ed. Blackwell Publishing Company, USA.
Fernandes Prabhavathi (2006). Antibacterial discovery – the failure of success? Nature Biotechnology, 24(12):1.
Finch R.G, Greenwood D, Norrby R and Whitley R (2002). Antibiotic and chemotherapy, 8th edition. Churchill Livingstone, London and Edinburg.
Acar, J. F. (2000). Antibiotic synergy and antagonism. Medical Clinics of North America, 84(6), 1391–1406.
Alikhani, M. S., Nazari, M., & Hatamkhani, S. (2025). Enhancing antibiotic therapy through comprehensive pharmacokinetic/pharmacodynamic principles. Frontiers in Cellular and Infection Microbiology, 15, 1521091.
Apley, M. D. (2022). Antimicrobial chemotherapy and antimicrobial resistance. Veterinary Microbiology, 69, 771–802.
Burgess, A., & MacGowan, A. (2026). Antimicrobial therapy: Principles of use. Medicine, 54(1), 31–39.
Dhara, A. K., Nayak, A. K., & Chattopadhyay, D. (Eds.). (2023). Antibiotics: Therapeutic spectrum and limitations. Academic Press.
Halawa, E. M., Fadel, M., Al-Rabia, M. W., Behairy, A., Nouh, N. A., Abdo, M., Olga, R., Fericean, L., Atwa, A. M., El-Nablaway, M., & Abdeen, A. (2024). Antibiotic action and resistance: Updated review of mechanisms, spread, influencing factors, and alternative approaches for combating resistance. Frontiers in Pharmacology, 14, 1305294.
Kollef, M. H., Shorr, A. F., Bassetti, M., et al. (2021). Timing of antibiotic therapy in the ICU. Critical Care, 25, 360.
Livermore, D. M. (2011). Discovery research: The scientific challenge of finding new antibiotics. Journal of Antimicrobial Chemotherapy, 66(9), 1941–1944.
Sengupta, S., Chattopadhyay, M. K., & Grossart, H.-P. (2013). The multifaceted roles of antibiotics and antibiotic resistance in nature. Frontiers in Microbiology, 4, 47.
Discover more from Microbiology Class
Subscribe to get the latest posts sent to your email.