Antimicrobial resistance (AMR) refers to the ability of microorganisms to survive or continue multiplying despite exposure to an antimicrobial agent that would ordinarily inhibit or eliminate (kill) them. The term ‘antimicrobial’ encompasses several classes of anti-infective agents including antibiotics, disinfectants, antiseptics, and sterilants. AMR includes resistance in bacteria, fungi, viruses, and parasites against their respective therapeutic agents.
Antibiotic resistance (ABR) is a narrower concept that specifically describes the ability of bacteria to withstand the effects of antibiotics. It is a major component of AMR, but the two terms are not interchangeable. This distinction is important because the biological mechanisms, transmission patterns, clinical consequences, and control strategies associated with bacterial antibiotic resistance may differ substantially from resistance occurring in fungal, viral, or parasitic pathogens, as well as microbial resistance to disinfectants and other antimicrobial agents.
Antibiotics remain fundamental to modern medicine, providing effective treatment for bacterial infections and enabling procedures such as major surgery, organ transplantation, cancer chemotherapy, and intensive care. Their effectiveness, however, depends on the continued susceptibility of bacterial pathogens. When resistance develops, an antibiotic may become less effective or completely ineffective, potentially resulting in prolonged illness, treatment failure, increased healthcare utilization, and greater dependence on alternative therapies. The emergence of resistance therefore threatens not only the treatment of individual infections but also the reliability of medical interventions that depend on effective antimicrobial therapy.
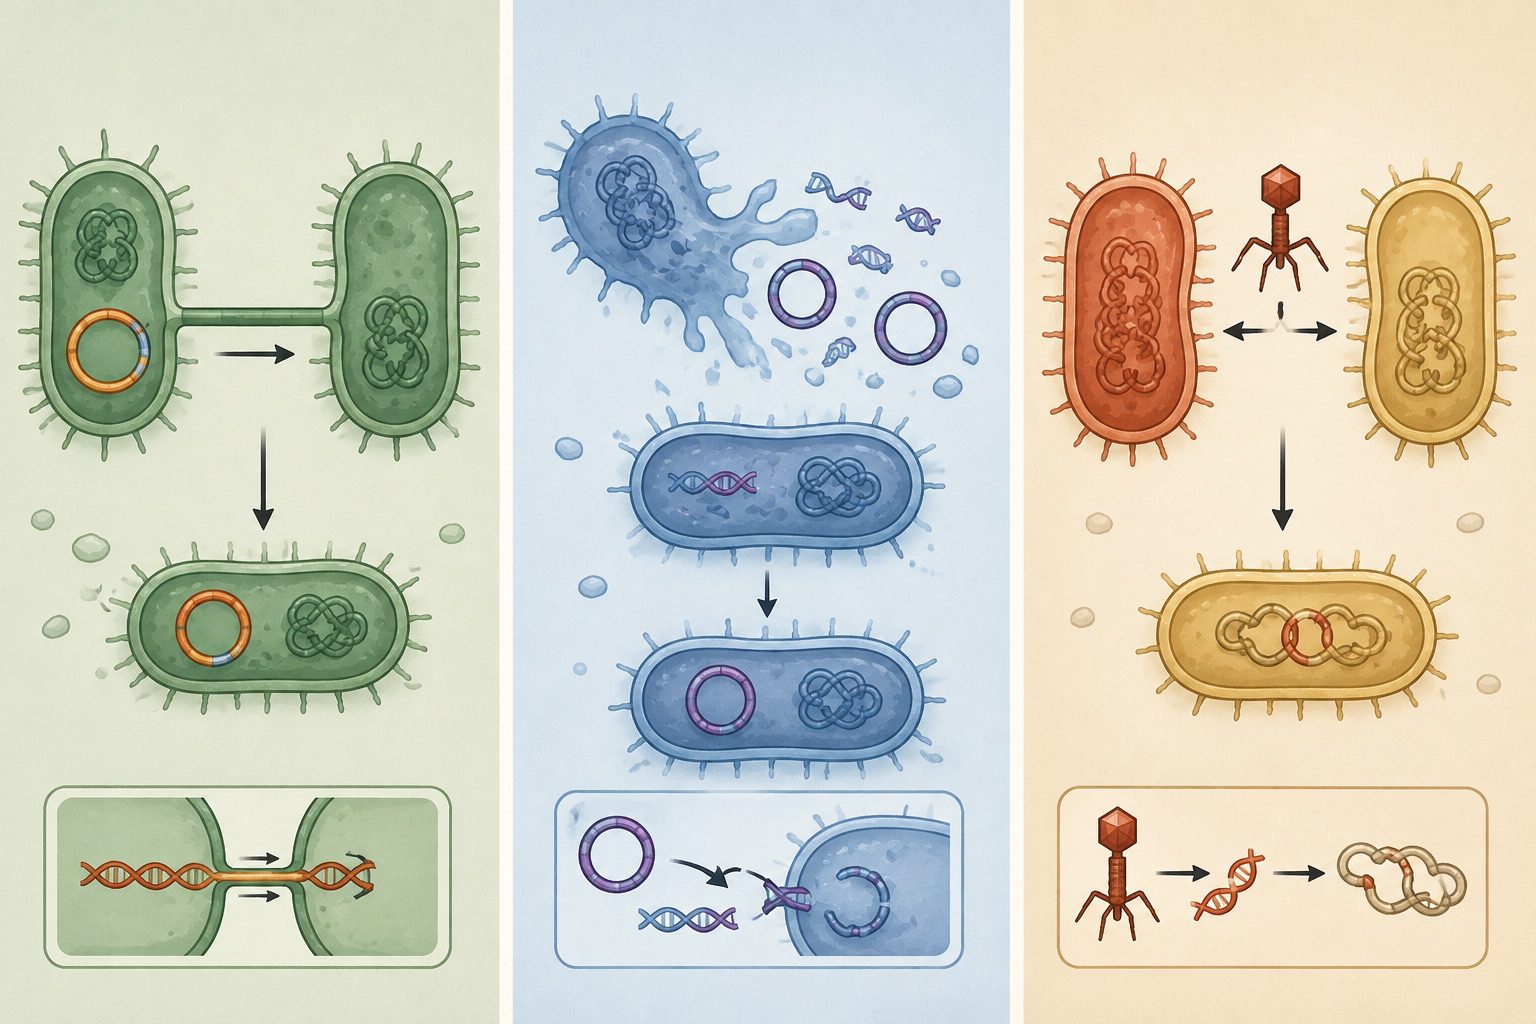
At the biological level, antibiotic resistance represents an evolutionary adaptation arising from genetic variation and selection. Bacteria can develop resistance through chromosomal mutations or acquire resistance determinants from other microorganisms through horizontal gene transfer. Once resistance traits are present, exposure to antibiotics creates selective conditions in which susceptible bacteria are inhibited or eliminated while resistant organisms have a relative survival advantage. Resistance genes can subsequently spread within bacterial populations through mobile genetic elements such as plasmids, transposons, and integrons. This process allows resistance to emerge and disseminate rapidly, particularly when multiple resistance determinants become associated within the same bacterial population.
The problem becomes more complex when bacteria accumulate mechanisms against several antibiotic classes. Resistance may result from enzymatic degradation or modification of antibiotics, alteration of antimicrobial targets, reduced permeability of the bacterial cell envelope, active efflux of drugs, or physiological adaptations associated with biofilm formation. These mechanisms can occur simultaneously, producing multidrug-resistant organisms for which conventional treatment options are increasingly constrained. Importantly, resistance is not generated solely by inappropriate antibiotic prescribing. Antibiotic exposure creates selection pressure, but resistance can subsequently persist and spread through healthcare-associated transmission, community transmission, food systems, animals, wastewater, and environmental reservoirs.
This broader connectivity distinguishes AMR as an ecological and public-health phenomenon rather than exclusively a clinical problem. Resistant microorganisms and resistance genes can move among humans, animals, food-production systems, healthcare environments, and natural ecosystems. The One Health framework therefore provides an important basis for understanding AMR, emphasizing the interconnectedness of human, animal, and environmental health.
The distinction between ABR and AMR consequently has practical significance. ABR focuses specifically on bacterial adaptation to antibiotics, whereas AMR captures the wider spectrum of resistance affecting multiple types of microorganisms and antimicrobial therapies. AMR, particularly antibiotic resistance, is a major challenge in clinical and microbiological settings because it reduces the effectiveness of commonly used antimicrobial agents and can complicate the treatment of bacterial infections. Antimicrobial susceptibility testing (AST) is therefore essential for identifying resistance patterns and supporting appropriate antibiotic selection.
Susceptibility testing is an important tool for understanding and responding to antimicrobial resistance (AMR), particularly antibiotic resistance (ABR). The inhibition zones observed around antibiotic discs provide at least a preliminary data on AMR, and it is an indication of whether bacterial isolates are susceptible, less susceptible, or resistant to specific antibiotics (Figure 1). This information is important because bacteria with reduced or absent inhibition zones may be more difficult to treat with those agents, limiting the available therapeutic options.
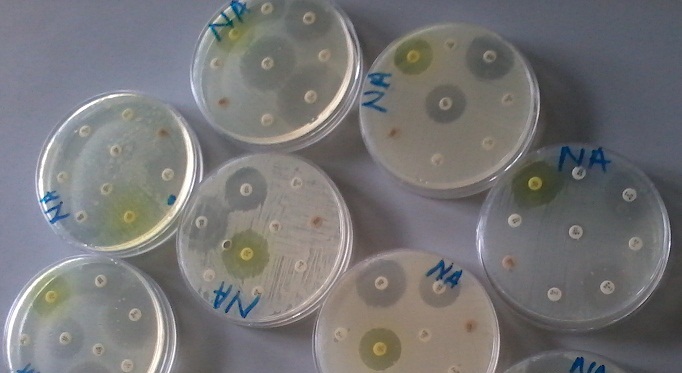
Differences in inhibition-zone diameters between isolates also demonstrate that resistance is not uniform. Individual bacterial isolates can have different resistance profiles, meaning that an antibiotic that is effective against one isolate may be ineffective against another. This variability highlights the importance of AST in identifying appropriate treatment options rather than relying solely on empirical antibiotic selection.
From an AMR perspective, AST is therefore valuable not only for guiding effective antimicrobial therapy but also for identifying resistance patterns within bacterial populations. When resistance is detected across multiple antibiotics, it can indicate increasing pressure on available treatment options and reinforces the need for responsible antimicrobial use. Continued AST and resistance surveillance are consequently essential for detecting emerging resistance, supporting antimicrobial stewardship, and helping to preserve the effectiveness of existing antibiotics.
The expanding clinical consequences of antibiotic resistance
The therapeutic reliability of antibiotics has progressively become less predictable as resistant bacterial populations become established in both healthcare facilities and community settings. This development is particularly consequential because antibacterial therapy underpins the management of infections that range from uncomplicated community-acquired disease to severe healthcare-associated infections. The problem is no longer confined to isolated treatment failures. Increasing resistance can alter the trajectory of infection by prolonging the period during which patients remain symptomatic and infectious, increasing the probability of complications, and narrowing the interval between an initially manageable infection and one requiring highly specialized care.
Antibiotic resistance should be considered a dynamic threat to the durability of routine clinical practice rather than simply a laboratory characteristic of individual bacterial isolates. The clinical implications become more pronounced when resistance involves antimicrobial classes that have historically provided broad therapeutic coverage. β-lactam antibiotics illustrate this vulnerability particularly well because they include numerous agents used across primary care, emergency medicine, surgery, pediatrics, and critical care.
The emergence of extended-spectrum β-lactamase (ESBL)-producing organisms has complicated this therapeutic landscape by allowing bacteria to hydrolyze a wide range of β-lactam compounds. Infections caused by such organisms may consequently require alternative agents, prolonged treatment, additional laboratory investigation, or more intensive clinical monitoring. When resistance determinants accumulate within the same bacterial population, therapeutic decisions become increasingly dependent on accurate susceptibility information rather than empirical assumptions about likely drug activity.
The consequences also extend beyond the individual patient. Resistant infections can increase hospital occupancy, laboratory workload, expenditure on antimicrobial therapy, and the requirement for infection-prevention measures. At the community level, resistant organisms may circulate silently among individuals without producing immediate clinical disease, creating reservoirs from which subsequent infections can arise. The distinction between community and hospital resistance is therefore becoming progressively less absolute. Patients, healthcare workers, food products, animals, wastewater, and contaminated environments can participate in interconnected transmission pathways.
This changing epidemiology challenges the assumption that antimicrobial effectiveness is a permanent attribute of a drug. Every antibiotic is introduced into an ecological environment containing bacterial populations capable of genetic adaptation. Once selective pressure favors resistant organisms, their persistence depends not only on continued antimicrobial exposure but also on transmission efficiency, bacterial fitness, environmental survival, and the mobility of resistance determinants. Preserving antibiotic effectiveness therefore requires interventions that address both treatment practices and the broader conditions that allow resistant bacteria to emerge, persist, and disseminate.
Selective pressure, antimicrobial exposure, and resistance dissemination
Selective pressure is an environmental force that causes organisms with certain traits to survive and reproduce more successfully than others. In the context of antibiotic resistance, selective pressure occurs when antibiotics expose a bacterial population to conditions in which susceptible bacteria are inhibited or killed, while bacteria carrying resistance traits survive and reproduce. Repeated or inappropriate antibiotic exposure can therefore increase the relative proportion of resistant bacteria in the population.
For example, If a population of bacteria contains 99% antibiotic-susceptible bacteria and 1% resistant bacteria, treatment with an antibiotic may eliminate most susceptible bacteria while allowing the resistant bacteria to survive. The survivors can then multiply, making the resistant phenotype more common. Antibiotics do not necessarily create resistance directly. Rather, they can select for resistant bacteria that already possess resistance through mutation or acquired genetic determinants. This distinction is important when explaining the evolutionary basis of antibiotic resistance.
The development and dissemination of antibiotic resistance are closely associated with the intensity, frequency, and context of antimicrobial exposure. Antibiotic use does not operate as a simple binary event in which bacteria are either exposed or unexposed. Concentration, duration of exposure, pharmacokinetic variability, tissue penetration, adherence, dosing accuracy, and the susceptibility profile of the organism collectively influence the selective environment experienced by bacterial populations.
Inadequate exposure can fail to eliminate susceptible organisms while providing conditions under which organisms carrying advantageous resistance traits survive. At the population level, repeated antimicrobial exposure can consequently reshape microbial communities by changing the relative abundance of susceptible and resistant organisms. This selection process is not restricted to therapeutic antibiotics. Antimicrobial compounds used in sanitation, agriculture, food production, animal health, and other settings may contribute to the wider ecological pressure surrounding microorganisms.
The movement of bacteria and resistance determinants across these environments creates opportunities for resistance to persist outside the immediate site of antibiotic administration. Human and veterinary medicine are therefore connected through shared microbial ecosystems. Resistant organisms selected in one setting may subsequently reach another through direct contact, food chains, animal movement, wastewater, contaminated surfaces, or environmental pathways.
The situation is further complicated by horizontal gene transfer. Bacteria do not depend exclusively on reproduction to acquire adaptive characteristics. Resistance determinants can be exchanged between microorganisms through mobile genetic elements, allowing particular resistance traits to move across bacterial populations. Plasmids, transposons, and integrons can carry combinations of resistance genes, creating opportunities for the simultaneous dissemination of resistance to several antimicrobial classes. Such genetic mobility helps explain why resistance can spread rapidly once an advantageous determinant becomes established in a bacterial population.
The contribution of antimicrobial exposure is especially important where antibiotics are used without adequate microbiological guidance. Self-medication, incomplete treatment courses, inappropriate drug selection, unnecessary prescriptions, and the use of antibiotics for non-bacterial illnesses can expose bacterial communities to selection pressure without providing corresponding therapeutic benefit. In some settings, antibiotics may also be obtained without appropriate clinical assessment, facilitating use based on symptoms rather than microbiological or clinical evidence.
A relevant example is the empirical treatment of febrile illness. In malaria-endemic regions, fever may be incorrectly attributed simultaneously to multiple infectious causes, resulting in antibacterial treatment alongside antimalarial therapy without adequate evidence of bacterial infection. Such practices expose commensal and potentially pathogenic bacteria to unnecessary antibiotics. The resulting ecological effect may be subtle at the individual level but substantial when repeated across large populations. Addressing this problem therefore requires more than reducing antibiotic consumption; it requires improving diagnostic confidence, prescribing practices, access to qualified healthcare, and public understanding of when antibacterial therapy is appropriate.
The growing gap between resistance evolution and therapeutic innovation
A central difficulty in addressing antibiotic resistance is the imbalance between the adaptability of bacterial populations and the comparatively limited introduction of new antibacterial therapies. Bacteria possess short generation times, large population sizes, extensive genetic diversity, and multiple pathways through which advantageous traits can be acquired. These characteristics allow resistance to emerge under appropriate selective conditions and, once established, to disseminate through bacterial populations. Pharmaceutical innovation, by contrast, involves lengthy processes of discovery, optimization, toxicological assessment, clinical evaluation, regulatory review, manufacturing, and post-marketing surveillance. The resulting difference in timescale creates a persistent vulnerability within the antimicrobial therapeutic pipeline.
The problem is not simply the absence of new antibiotics. New compounds may also encounter resistance soon after introduction if their use generates strong selective pressure or if pre-existing resistance mechanisms provide cross-resistance. Therapeutic innovation cannot be separated from antimicrobial stewardship. Preserving the activity of newly introduced agents requires their deployment within treatment strategies that minimize unnecessary exposure and maintain appropriate dosing. The objective should therefore extend beyond replacing ineffective antibiotics with newer ones; it should include prolonging the useful clinical lifespan of existing and emerging agents.
Resistance mechanisms themselves demonstrate the adaptability of bacterial populations. Enzymatic degradation or modification of antibiotics can neutralize drug activity, while mutations or acquired genes can alter antimicrobial targets. Changes in membrane permeability may reduce intracellular drug accumulation, whereas efflux systems can actively remove antimicrobial compounds from bacterial cells. Biofilm formation introduces another layer of complexity because bacteria embedded within structured microbial communities may exhibit altered physiological states and reduced susceptibility to antimicrobial treatment. When several mechanisms occur simultaneously, organisms can acquire resistance profiles that severely restrict therapeutic options.
The emergence of ESBL-producing Enterobacterales exemplifies the clinical consequences of this evolutionary flexibility. ESBL enzymes can compromise the activity of several extended-spectrum β-lactam antibiotics, while the same bacterial isolates may carry additional determinants affecting other antimicrobial classes. Resistance therefore frequently occurs as a network of linked traits rather than as an isolated response to a single drug. This phenomenon complicates empirical treatment and increases the importance of laboratory-based susceptibility information.
The widening gap between bacterial adaptation and antimicrobial development also emphasizes the importance of prevention. Infection prevention, vaccination, rapid diagnosis, appropriate antimicrobial selection, optimized dosing, surveillance, and environmental control can reduce the number of infections requiring antibiotic treatment in the first place. Prevention consequently functions not merely as a public-health adjunct but as a mechanism for reducing the selective landscape in which resistance evolves. Maintaining antibiotic effectiveness will require simultaneous progress in therapeutic discovery and in the systems that determine how, where, and when antimicrobial agents are used.
Diagnostic surveillance and laboratory-based control of resistance
The containment of antibiotic resistance depends substantially on the ability to recognize resistant organisms before therapeutic failure becomes clinically apparent. In this context, the microbiology laboratory occupies a strategic position between individual patient management and population-level surveillance. Routine antimicrobial susceptibility testing can provide information about the activity of available agents against bacterial isolates, while systematic analysis of these results can reveal emerging resistance patterns within hospitals and communities. Without reliable laboratory data, antimicrobial prescribing may remain heavily dependent on empirical expectations that become progressively less accurate as resistance patterns change.
Laboratory detection is particularly important for organisms expressing clinically significant resistance mechanisms, including ESBL-producing bacteria and other multidrug-resistant pathogens. Their identification can influence antimicrobial selection and trigger appropriate infection-prevention measures. However, the usefulness of susceptibility testing depends on standardized procedures, quality assurance, appropriate specimen collection, and interpretation using recognized laboratory criteria. Internationally established standards, including those developed by the Clinical and Laboratory Standards Institute (CLSI), provide structured approaches for antimicrobial susceptibility testing and interpretation. Consistent application of such standards facilitates comparability between laboratories and improves the reliability of resistance surveillance.
Laboratory surveillance should nevertheless extend beyond reporting individual susceptibility results. Aggregated microbiological data can identify changes in resistance prevalence, detect unusual resistance phenotypes, characterize local susceptibility profiles, and support antimicrobial stewardship programs. When linked with clinical information, these data can contribute to hospital antibiograms and inform empirical treatment protocols. At the community level, surveillance can provide evidence about the circulation of resistant organisms that may otherwise remain undetected until they produce difficult-to-treat infections.
Effective surveillance also requires communication. Laboratory findings have limited public-health value when they remain isolated within individual diagnostic reports. Resistance information should move efficiently between microbiologists, clinicians, pharmacists, infection-prevention personnel, hospital administrators, public-health authorities, and other relevant stakeholders. Integration of these data can support targeted interventions rather than generalized restrictions that may not correspond to local epidemiology.
The long-term objective is therefore not simply to identify resistant bacteria but to establish a responsive surveillance system capable of connecting detection with action. A resistant isolate identified in the laboratory should contribute to decisions concerning treatment, infection control, antimicrobial stewardship, and epidemiological monitoring. At the same time, surveillance data can identify areas in which prescribing practices, diagnostic capacity, sanitation, or infection-prevention procedures require strengthening. Antibiotic resistance will not be controlled through a single intervention because its emergence reflects interactions among microbial evolution, antimicrobial exposure, healthcare practices, animal health, environmental conditions, and population behavior.
A sustainable response requires these components to be addressed simultaneously. Strengthening diagnostic capacity, rationalizing antimicrobial use, improving infection prevention, expanding surveillance, limiting unnecessary exposure, and supporting the development of new therapeutic options can collectively reduce the opportunities available for resistant organisms to emerge and spread. The central challenge is consequently to preserve the clinical utility of antibiotics while recognizing that their effectiveness is a finite biological resource that must be actively protected.
References
Bisht R., Katiyar A., Singh R and Mittal P (2009). Antibiotic Resistance – A Global Issue of Concern. Asian Journal of Pharmaceutical and Clinical Research, 2 (2):34-39.
Courvalin P, Leclercq R and Rice L.B (2010). Antibiogram. ESKA Publishing, ASM Press, Canada.
Denyer S.P., Hodges N.A and Gorman S.P (2004). Pharmaceutical Microbiology. 7th ed. Blackwell Publishing Company, USA.
Finch R.G, Greenwood D, Norrby R and Whitley R (2002). Antibiotic and chemotherapy, 8th edition. Churchill Livingstone, London and Edinburg.
Hart C.A (1998). Antibiotic Resistance: an increasing problem? BMJ, 316:1255-1256.
Jayaramah R (2009). Antibiotic Resistance: an overview of mechanisms and a paradigm shift. Current Science, 96(11):1475-1484.
Mascaretti O.A (2003). Bacteria versus antibacterial agents: An integrated approach. Washington: ASM Press.
Mazel D and Davies J (1998). Antibiotic Resistance: The Big Picture. In B. Rosen and S. Mobashery (Eds). Resolving the antibiotic paradox: progress in understanding drug resistance and developments of new antibiotics. New York: Plenum Press.
Russell A.D and Chopra I (1996). Understanding antibacterial action and resistance. 2nd edition. Ellis Horwood Publishers, New York, USA.
Sundsfjord A., Simonsen G.S., Haldorsen B.C., Haaheim H., Hjelmevoll S., Littauer P and Dahl K.H (2004). Genetic methods for detection of antimicrobial resistance. APMIS, 112:815-37.
Discover more from Microbiology Class
Subscribe to get the latest posts sent to your email.