Gene therapy represents one of the most transformative frontiers in modern biomedical science, offering the potential to treat, prevent, or even cure diseases by directly modifying genetic material. Despite its promise, gene therapy remains a highly complex and carefully regulated field, largely due to the inherent risks associated with altering the human genome. Consequently, the development and implementation of gene therapy require a rigorous, multi-stage process that ensures safety, efficacy, and ethical compliance. These prerequisites encompass extensive pre-clinical investigations, optimization of delivery systems, and carefully designed clinical trials, among other considerations.
The development and implementation of gene therapy involve a comprehensive and highly structured sequence of steps, each designed to ensure the highest standards of safety and efficacy. From initial target identification and vector design to pre-clinical testing, clinical trials, and long-term monitoring, every stage plays a critical role in translating experimental concepts into viable medical treatments. Despite significant challenges particularly in delivery efficiency, immune responses, and long-term safety advances in molecular biology, genome editing technologies, and biomaterials continue to accelerate progress in this field. As these hurdles are progressively overcome, gene therapy is poised to become a cornerstone of precision medicine, offering hope for the treatment of previously incurable diseases.
The following are important steps to be considered in gene therapy development
Conceptual Foundation and Target Identification
The first prerequisite in gene therapy is a clear understanding of the disease at the molecular and genetic levels. This involves identifying the specific gene or genetic mutation responsible for the disease phenotype. Diseases suitable for gene therapy are often monogenic disorders (such as cystic fibrosis or sickle cell disease), but increasingly, complex conditions like cancers and neurodegenerative disorders are also being targeted.
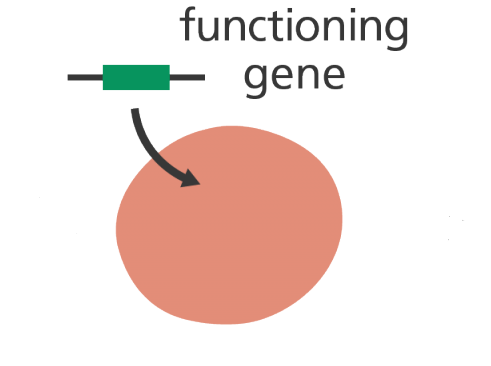
At this stage, researchers must determine whether the therapeutic goal is gene replacement, gene silencing, gene editing, or gene augmentation. For example, loss-of-function mutations may require gene replacement, whereas gain-of-function mutations may necessitate gene silencing strategies using RNA interference or CRISPR-based approaches. A detailed understanding of gene expression patterns, regulatory elements, and tissue specificity is essential before progressing further.
Vector Design and Development
Once the therapeutic gene or genetic strategy is identified, the next critical step is the design of an appropriate vector for gene delivery. Vectors serve as carriers that transport the therapeutic genetic material into target cells. They can be broadly classified into viral and non-viral systems.
Viral vectors, such as adenoviruses, adeno-associated viruses (AAV), and lentiviruses, are commonly used due to their high efficiency in gene transfer. However, they come with challenges, including immunogenicity, insertional mutagenesis, and limitations in cargo capacity. Non-viral vectors, including liposomes, nanoparticles, and electroporation techniques, offer improved safety profiles but often suffer from lower delivery efficiency.
Vector design must address several parameters as follows:
- Target cell specificity (tropism)
- Duration of gene expression (transient vs. stable)
- Minimization of immune response
- Scalability for clinical-grade production
Optimization of these factors is essential before proceeding to experimental validation. Vector design in gene therapy is a highly critical and technically demanding process that directly influences the overall success, safety, and translational potential of the therapeutic strategy. An effective vector must be engineered to meet several key parameters, each of which requires careful optimization and validation.
First, target cell specificity (tropism) is essential to ensure that the therapeutic gene is delivered precisely to the intended cell type or tissue. This can be achieved through modification of viral capsids, incorporation of tissue-specific promoters, or the use of targeting ligands in non-viral systems. High specificity reduces off-target effects and enhances therapeutic efficacy.
Second, the duration of gene expression must be tailored to the clinical objective. Some conditions require only transient expression—for example, in cancer immunotherapy—while others, such as genetic deficiencies, demand long-term or stable expression. This is influenced by vector type, genomic integration capability, and regulatory elements controlling transcription.
Third, minimization of immune response is a major consideration. Both innate and adaptive immune reactions can neutralize vectors, reduce gene expression, or cause adverse effects. Strategies such as vector engineering, immune evasion techniques, and careful dose selection are employed to mitigate immunogenicity.
Finally, scalability for clinical-grade production is crucial for translating gene therapy from laboratory research to clinical application. Vectors must be producible under Good Manufacturing Practice (GMP) conditions, ensuring consistency, purity, and safety at large scale.
3. Pre-Clinical In Vitro Studies
Pre-clinical in vitro studies are a foundational step in gene therapy development. These experiments are conducted in controlled laboratory environments using cultured cells to evaluate the basic functionality and safety of the therapeutic construct.
Key objectives of in vitro studies include:
- Confirming successful gene transfer and expression
- Assessing the biological activity of the introduced gene
- Evaluating cytotoxicity and off-target effects
- Determining dose-response relationships
Cell models used in these studies may include immortalized cell lines, primary cells, or patient-derived cells. Increasingly, advanced systems such as organoids and 3D culture models are employed to better mimic physiological conditions. In vitro testing allows researchers to refine vector constructs and delivery methods before moving into more complex biological systems. It also provides initial insights into potential safety concerns, such as unintended gene activation or suppression.
Pre-Clinical In Vivo Studies
Following successful in vitro validation, gene therapy candidates must undergo in vivo testing using animal models. These studies are critical for understanding how the therapy behaves in a whole organism, where factors such as immune responses, tissue distribution, and metabolic processes come into play.
Animal models are selected based on their relevance to the human disease being studied. These may include genetically modified mice, rats, or larger animals such as dogs or non-human primates, depending on the complexity of the disease.
Key aspects evaluated during in vivo studies include:
- Biodistribution of the vector and transgene
- Duration and level of gene expression
- Therapeutic efficacy in disease models
- Immunogenicity and toxicity
- Potential for insertional mutagenesis
In vivo studies also help determine the optimal route of administration, which may include intravenous, intramuscular, intrathecal, or localized delivery depending on the target tissue.
Optimization of Gene Delivery Systems
One of the most significant challenges in gene therapy is the efficient and targeted delivery of genetic material to the appropriate cells or tissues. The success of gene therapy largely depends on overcoming biological barriers such as cellular membranes, immune defenses, and tissue-specific accessibility.
Delivery strategies in gene therapy must be precisely tailored to the underlying disease pathology and the anatomical location of the target tissue. This customization is necessary because biological barriers, cellular accessibility, and disease mechanisms vary significantly across conditions, thereby influencing both the efficiency and safety of gene transfer.
The optimization of gene delivery systems can be explained in the following disease conditions in which gene therapy could be applied:
- Neurological disorders: This requires vectors capable of crossing the blood-brain barrier. For neurological disorders, one of the primary challenges is the presence of the blood-brain barrier (BBB), a highly selective physiological barrier that restricts the passage of most macromolecules from the bloodstream into the central nervous system. To address this, vectors must either possess intrinsic capabilities to cross the BBB such as certain engineered adeno-associated viruses or be delivered through alternative routes like intrathecal or intracerebral injection. These approaches ensure that the therapeutic gene reaches neurons or glial cells in sufficient quantities while minimizing systemic exposure.
- Hematological conditions: This may involve ex vivo modification of patient-derived stem cells followed by reinfusion. In hematological conditions, such as sickle cell disease or certain immunodeficiencies, gene delivery is often performed using an ex vivo approach. In this strategy, hematopoietic stem cells are harvested from the patient, genetically modified in a controlled laboratory setting, and then reinfused back into the patient. This method allows for high-efficiency gene transfer and extensive quality control prior to administration. Additionally, because the patient’s own cells are used, the risk of immune rejection is significantly reduced.
- Cancer therapies: This may use targeted vectors that selectively infect tumor cells. For cancer therapies, delivery systems are frequently designed to achieve selective targeting of tumor cells while sparing normal tissues. This can be accomplished through vectors engineered to recognize tumor-specific surface markers or by using promoters that are only active in cancer cells. Some approaches also exploit the tumor microenvironment, such as hypoxia-responsive systems, to enhance specificity. This targeted delivery not only improves therapeutic efficacy but also reduces off-target toxicity and systemic side effects.
Safety and Toxicology Assessment
Before transitioning to human trials, comprehensive safety and toxicology studies are required. These studies are conducted under Good Laboratory Practice (GLP) conditions and are designed to identify any potential risks associated with the therapy.
Key safety concerns in gene therapy include:
- Immune reactions to the vector or transgene
- Off-target genetic effects
- Long-term expression and potential toxicity
- Risk of oncogenesis due to insertional mutagenesis
Toxicology studies often involve multiple animal species and extended observation periods to assess both acute and chronic effects. Regulatory agencies require detailed documentation of these findings before approving clinical trials.
Regulatory Approval and Ethical Considerations
Gene therapy is subject to strict regulatory oversight due to its complexity and potential risks. Before initiating clinical trials, researchers must submit an Investigational New Drug (IND) application or equivalent documentation to regulatory authorities.
This submission includes:
- Pre-clinical data (in vitro and in vivo results)
- Details of vector design and manufacturing
- Proposed clinical trial protocols
- Risk mitigation strategies
Ethical considerations are also paramount. Gene therapy raises important questions about long-term effects, germline modification, and equitable access. Institutional review boards (IRBs) and ethics committees must approve study designs to ensure patient safety and informed consent.
Clinical Trial Phases
Clinical trials in gene therapy follow a phased approach similar to other biomedical interventions, but often with additional safeguards.
Phase I trials focus primarily on safety and involve a small number of participants. Researchers assess tolerability, dosing, and initial biological effects.
Phase II trials expand the participant pool and aim to evaluate efficacy while continuing to monitor safety. These trials provide preliminary evidence of therapeutic benefit.
Phase III trials involve larger populations and are designed to confirm efficacy, compare with existing treatments, and identify rare adverse effects. Successful completion of this phase is typically required for regulatory approval.
Phase IV (post-marketing surveillance) may be conducted after approval to monitor long-term outcomes and rare side effects in the general population.
Manufacturing and Quality Control
Another critical prerequisite is the development of robust manufacturing processes for producing clinical-grade vectors and genetic materials. This must comply with Good Manufacturing Practice (GMP) standards to ensure consistency, purity, and safety.
Challenges in manufacturing include:
- Scaling up production without compromising quality
- Maintaining vector stability
- Preventing contamination
- Ensuring reproducibility across batches
Quality control measures involve rigorous testing at every stage of production, including vector characterization, sterility testing, and potency assays.
Long-Term Monitoring and Follow-Up
Gene therapies often involve permanent or long-lasting genetic modifications, making long-term monitoring essential. Patients who receive gene therapy are typically followed for years to assess durability of the therapeutic effect and detect any delayed adverse events.
Long-term follow-up studies may include:
- Periodic clinical evaluations
- Genetic and molecular analyses
- Monitoring for secondary conditions such as cancer
These data are crucial for refining future therapies and improving safety profiles.
References
Sayed, N., Allawadhi, P., Khurana, A., Singh, V., Navik, U., Pasumarthi, S. K., Khurana, I., Banothu, A. K., Weiskirchen, R., & Bharani, K. K. (2022). Gene therapy: Comprehensive overview and therapeutic applications. Life Sciences, 294, 120375. https://doi.org/10.1016/j.lfs.2022.120375
Rashid, R. A., & Ankathil, R. (2020). Gene therapy: An updated overview on the promising success stories. Malaysian Journal of Pathology, 42(2), 171–185.
Alberts B, Bray D, Johnson A, Lewis J, Raff M, Roberts Kand Walter P (1998). Essential Cell Biology: An Introduction to the Molecular Biology of the Cell. Third edition. Garland Publishing Inc., New York.
Dale J (2003). Molecular genetics of bacteria. Jeremy W. Dale and Simon Park (4th eds.). John Wiley & Sons Ltd, West Sussex, UK.
Edelstein, M. L., Abedi, M. R., Wixon, J., and Edelstein, R. M. (2004). Gene therapy clinical trials worldwide 1989-2004—an overview. J Gene Med, 6: 597-602.
Ferrua, F.; Brigida, I.; Aiuti, A. (2010). Update on gene therapy for adenosine deaminase-deficient severe combined immunodeficiency. Current Opinion in Allergy and Clinical Immunology. 10 (6): 551–556.
Gardlík R, Pálffy R, Hodosy J, Lukács J, Turna J, Celec P; Pálffy; Hodosy; Lukács; Turna; Celec (2005). Vectors and delivery systems in gene therapy. Med Sci Monit. 11 (4): RA110–21.
Horn PA, Morris JC, Neff T, Kiem HP; Morris; Neff; Kiem (2004). Stem cell gene transfer—efficacy and safety in large animal studies. Mol. Ther. 10 (3): 417–31.
S Li and L Huang (2000). Nonviral gene therapy: promises and challenges. Gene Therapy, 7:31-34. www.nature.com/gt
Salmons B, Günzburg WH; Günzburg (1993). Targeting of retroviral vectors for gene therapy. Hum Gene Ther. 4 (2): 129–41.
Sambrook, J., Russell, D.W. (2001). Molecular Cloning: a Laboratory Manual, 3rd edn. Cold Spring Harbor Laboratory Press, New York.
Vannucci, L; Lai, M; Chiuppesi, F; Ceccherini-Nelli, L; Pistello, M (2013). Viral vectors: A look back and ahead on gene transfer technology. The new microbiologica. 36 (1): 1–22.
Discover more from Microbiology Class
Subscribe to get the latest posts sent to your email.