The discovery and clinical deployment of antibiotics transformed the management of bacterial infections and fundamentally altered the trajectory of modern medicine. Before their widespread availability, bacterial diseases were major causes of morbidity and mortality, with limited therapeutic options for many infections. The introduction of penicillin, the first naturally derived antibiotic to achieve widespread clinical application, demonstrated the extraordinary capacity of antimicrobial agents to selectively eliminate pathogenic bacteria and established antibiotics as indispensable tools in infectious-disease management.
However, the effectiveness of antimicrobial therapy has progressively been challenged by the ability of bacteria to adapt to antimicrobial pressure. Antimicrobial resistance (AMR) occurs when microorganisms acquire or develop characteristics that enable them to survive exposure to drugs that would ordinarily inhibit or eliminate them. The extensive and sometimes inappropriate use of antimicrobial agents in human medicine, veterinary practice, livestock production, aquaculture, agriculture, and food-production systems has intensified this selective pressure and facilitated the emergence of resistant bacterial populations.
Of particular concern is the development of multidrug-resistant bacteria (MDRB). MDRB possess resistance to multiple antimicrobial classes rather than a single therapeutic agent. Such organisms can withstand several commonly used antibiotics, including β-lactams, aminoglycosides, macrolides, fluoroquinolones, and trimethoprim-sulfamethoxazole, thereby substantially narrowing available treatment options. The emergence of MDRB is therefore not simply a pharmacological problem but a complex biological and public-health challenge.
Historical development of antimicrobial therapy
The development of antimicrobial therapy represents a major turning point in the history of modern medicine. Before the antibiotic era, bacterial infections such as pneumonia, septicemia, tuberculosis, and wound infections were associated with substantial morbidity and mortality, while physicians had limited means of controlling their progression. Early observations of antimicrobial activity eventually led to the discovery of substances capable of selectively inhibiting bacterial growth. The discovery of penicillin by Alexander Fleming in 1928, followed by its purification, mass production, and clinical application in the 1940s, marked a defining milestone in infectious-disease treatment.
Subsequently, numerous antibiotic classes, including aminoglycosides, macrolides, tetracyclines, β-lactams, and fluoroquinolones, were developed, substantially expanding therapeutic options. The introduction of these agents transformed clinical practice by converting many previously life-threatening bacterial infections into treatable conditions. Antibiotics also enabled safer surgical procedures, organ transplantation, cancer chemotherapy, and other medical interventions that depend on effective infection control.
However, the therapeutic success of antibiotics was accompanied by an evolutionary consequence: the emergence and selection of resistant microorganisms. Bacteria exposed to antimicrobial agents can survive through pre-existing resistance traits or acquire adaptive genetic changes. Inappropriate prescribing, unnecessary consumption, incomplete treatment, and extensive antimicrobial use in non-human settings have intensified selective pressure. Antimicrobial resistance has progressively undermined the effectiveness of drugs that once provided reliable control of bacterial infections.
Mechanisms and dissemination of multidrug resistance
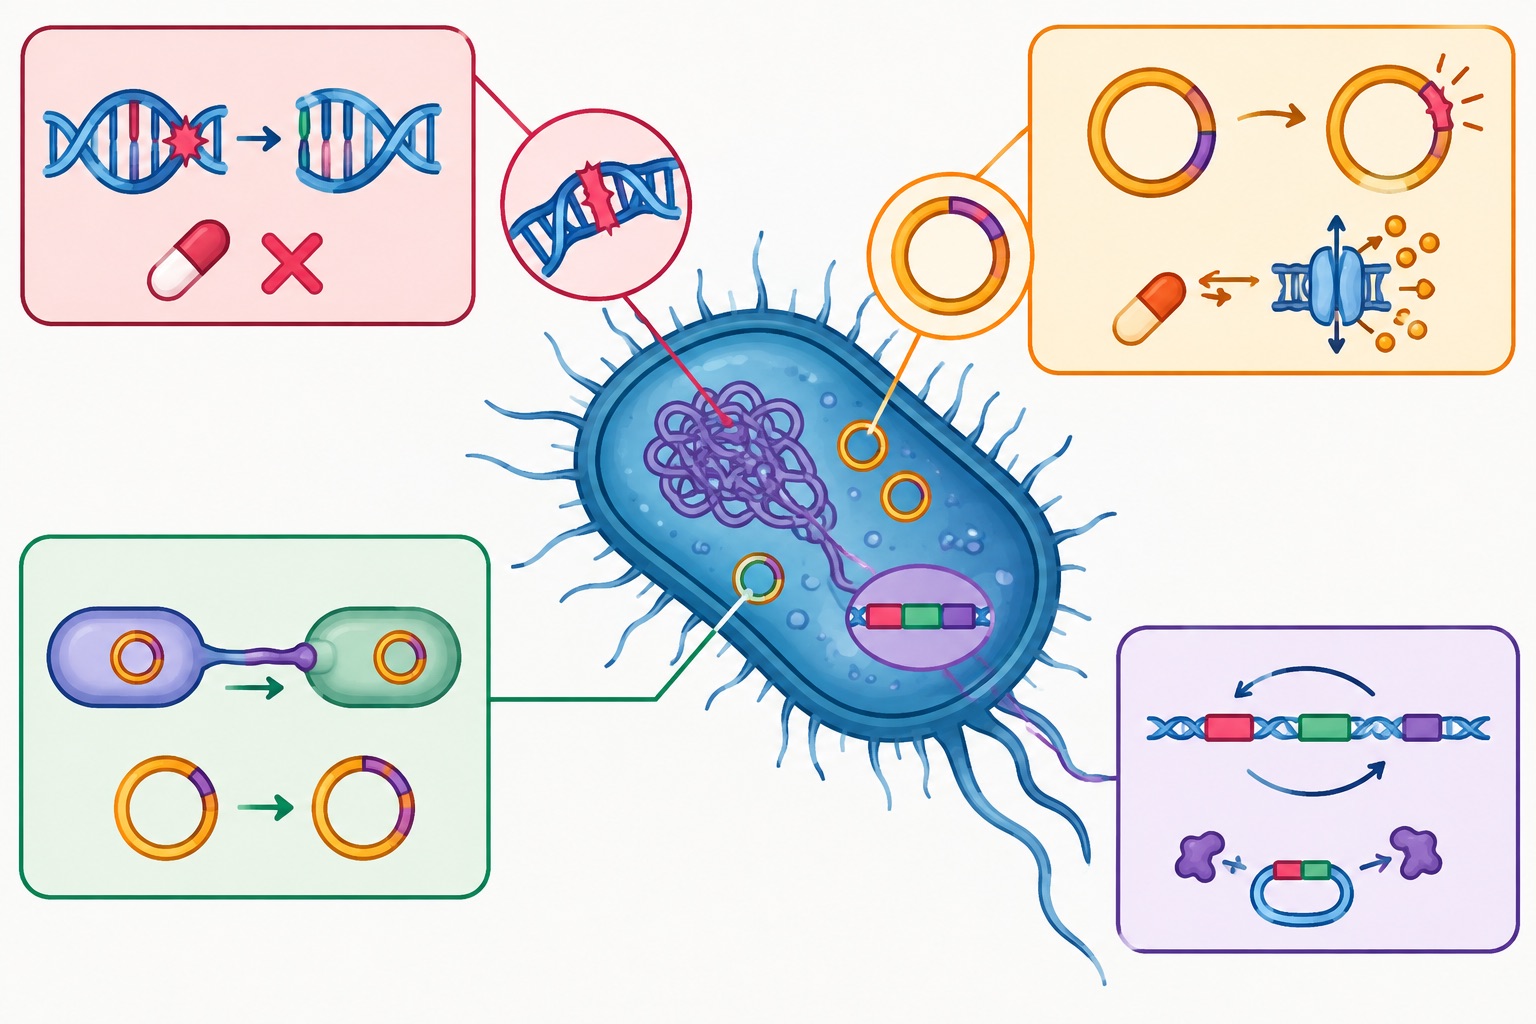
The capacity of bacteria to withstand antimicrobial treatment arises from evolutionary adaptation combined with the remarkable genetic plasticity of bacterial populations. Resistance may originate through spontaneous genetic alterations or through the acquisition of resistance determinants from other microorganisms. Although chromosomal mutations can generate advantageous traits under antimicrobial selection, horizontal gene transfer represents a particularly important pathway for the rapid distribution of resistance within and between bacterial populations.
Horizontal gene transfer enables bacteria to obtain genetic material without requiring direct descent from a resistant parent cell. Three principal mechanisms contribute to this process: conjugation, transformation, and transduction. Conjugation involves direct interaction between bacterial cells and commonly facilitates the movement of plasmids carrying multiple resistance determinants. Transformation occurs when competent bacteria internalize extracellular DNA released following cellular disruption, potentially incorporating resistance-associated sequences into their genome. Transduction is mediated by bacteriophages, which can inadvertently transport bacterial genetic material, including resistance determinants, from one cell to another.
Mobile genetic elements considerably increase the efficiency of this process. Plasmids, transposons, integrons, and insertion sequences can capture, rearrange, and disseminate resistance genes across bacterial populations. Consequently, exposure to antimicrobial compounds can select for organisms carrying combinations of resistance determinants and favor their persistence within microbial communities. Selective pressure is not restricted to antibiotics; certain disinfectants, biocides, and heavy metals may also contribute to co-selection when resistance mechanisms or associated genetic elements are linked.
The environmental context is particularly important because bacteria from humans, animals, food systems, wastewater, soil, and aquatic environments can interact within interconnected microbial ecosystems. Resistance determinants generated or maintained in one setting may therefore move into another through contaminated water, food, animals, environmental reservoirs, or human contact.
Multidrug resistance emerges when these processes accumulate resistance mechanisms against unrelated antimicrobial classes within the same organism. A single bacterial strain may consequently harbor multiple genes encoding β-lactamases, aminoglycoside-modifying enzymes, efflux systems, target-modifying proteins, or other protective mechanisms. Such genetic combinations can produce organisms capable of surviving sequential or simultaneous exposure to several therapeutic classes.
The spread of resistance is therefore driven by more than antibiotic consumption alone. It reflects the interaction between microbial evolution, mobile genetic elements, antimicrobial selection, ecological connectivity, and opportunities for bacterial exchange. This dynamic enables resistance traits to persist and disseminate even after the original selective environment has changed, making MDRB a particularly persistent biological threat.
Clinical consequences and strategies for containment of MDRB
The clinical significance of multidrug-resistant bacteria is primarily reflected in their capacity to compromise conventional treatment and prolong the course of infectious diseases. MDRB can be implicated in urinary tract infections, pneumonia, bloodstream infections, wound infections, gastroenteritis, skin and soft-tissue infections, endocarditis, respiratory infections, and other conditions affecting both hospitalized and community-based populations. When first-line antimicrobial agents become ineffective, clinicians may be forced to rely on drugs that are less familiar, more toxic, more expensive, or less readily available.
Healthcare environments provide particularly favorable conditions for the transmission and persistence of resistant organisms. Patients with prolonged hospital stays, severe underlying illness, immunosuppression, or repeated exposure to antimicrobial therapy may have increased susceptibility to MDRB infections. Crowded clinical settings, frequent patient-care interactions, invasive procedures, contaminated surfaces, and inadequate infection-prevention practices can further facilitate transmission. Nevertheless, resistance is not confined to hospitals. Resistant bacteria circulate through communities and may move between humans, animals, food systems, and environmental reservoirs, emphasizing the interconnected nature of the problem.
The consequences extend beyond individual treatment failure. Infections caused by MDRB may require longer hospitalization, additional diagnostic procedures, alternative therapeutic regimens, and increased healthcare expenditure. Delayed administration of effective therapy can worsen clinical outcomes, increase complications, and contribute to avoidable mortality. At a broader level, antimicrobial resistance threatens the reliability of routine medical procedures that depend on effective infection control, including surgery, transplantation, cancer treatment, and intensive-care interventions.
Effective management therefore requires precise identification of the causative organism and characterization of its susceptibility profile. Antimicrobial susceptibility testing provides essential evidence for selecting an effective agent and reducing unnecessary exposure to drugs that are unlikely to work. In severe infections, empirical treatment may initially be necessary, but therapy should subsequently be refined according to microbiological and susceptibility findings whenever possible.
Containment also requires action before resistance becomes clinically manifest. Antimicrobial stewardship should promote appropriate drug selection, dosage, duration, and indication while limiting unnecessary antimicrobial exposure. Infection-prevention measures, surveillance systems, environmental monitoring, vaccination, improved sanitation, and responsible antimicrobial practices in veterinary and agricultural settings are equally important. Because resistance can move across human, animal, food, and environmental compartments, a coordinated One Health approach is essential.
Ultimately, addressing MDRB requires simultaneous reduction of selective pressures, interruption of transmission, preservation of existing therapeutic options, and sustained development of new antimicrobial and non-antibiotic interventions. Without such coordinated measures, the progressive accumulation of resistance determinants may continue to erode the effectiveness of established antibacterial therapies.
Evolution and molecular basis of multidrug resistance
Multidrug resistance does not generally emerge from a single genetic event; rather, it develops through the progressive accumulation, interaction, and maintenance of multiple resistance determinants within bacterial populations. A bacterium initially susceptible to several antimicrobial agents may acquire a resistance trait that protects it against one drug and subsequently accumulate additional determinants that compromise other antimicrobial classes. These determinants may be located on the bacterial chromosome or carried by mobile genetic elements such as plasmids, transposons, and integrons. Their accumulation can produce resistance profiles that extend across pharmacologically unrelated drugs, creating bacterial populations for which conventional treatment options become increasingly ineffective.
The development of multidrug resistance is strongly influenced by selective pressure. When an antimicrobial is introduced into a bacterial population, susceptible cells are inhibited or eliminated, whereas organisms possessing advantageous resistance characteristics have a greater probability of surviving and reproducing. Repeated or prolonged exposure can consequently shift the composition of the population toward resistant phenotypes. Importantly, this process does not necessarily mean that every exposure directly creates a resistance gene. Instead, antimicrobial pressure preferentially preserves organisms that already possess, or subsequently acquire, genetic characteristics capable of supporting survival under the prevailing conditions.
The coexistence of several resistance determinants may generate co-resistance, in which distinct resistance genes are physically associated on the same genetic element. Selection for resistance to one antimicrobial can therefore indirectly maintain resistance to another drug that was not responsible for the initial selection. This phenomenon becomes particularly important when plasmids or other mobile elements carry multiple resistance genes. Elimination of one susceptible component of the bacterial population may consequently enrich organisms carrying an entire cluster of resistance determinants.
A related but distinct phenomenon is cross-resistance, whereby a single bacterial mechanism provides protection against multiple antimicrobial agents. Enhanced efflux activity, alterations in a shared drug target, or reduced cellular permeability can decrease the effectiveness of several structurally or functionally related compounds. Thus, resistance to one antimicrobial may coincide with reduced susceptibility to other agents even when separate resistance genes are not involved.
Bacterial adaptation further strengthens this evolutionary process. Under changing environmental conditions, bacterial populations can undergo genetic and physiological adjustments that improve survival. Mutations, gene acquisition, altered gene expression, and selection of advantageous variants may collectively produce increasingly resistant populations. Once established, these populations can persist within microbial communities and provide a genetic reservoir from which resistance determinants may spread to other bacteria.
The evolution of multidrug resistance is therefore best understood as a dynamic interaction between genetic variation, antimicrobial selection, bacterial adaptation, and horizontal dissemination of resistance determinants. This interaction allows resistance traits to accumulate and become established within bacterial populations, ultimately transforming previously manageable infections into infections with considerably fewer therapeutic options.
Reservoirs of multidrug-resistant bacteria
Multidrug-resistant bacteria are not restricted to clinical environments; they persist across interconnected human, animal, food, and environmental systems. These reservoirs provide conditions that allow resistant organisms and their associated genetic determinants to survive, interact, and disseminate beyond the location in which resistance initially emerged.
Hospitals and healthcare facilities represent important reservoirs because intensive antimicrobial exposure, high patient density, invasive procedures, and frequent movement of healthcare personnel create strong opportunities for resistant organisms to persist and circulate. Hospital wastewater, medical equipment, patient-care surfaces, and colonized individuals can collectively contribute to the maintenance of resistant bacterial populations.
Community settings provide a broader reservoir in which MDRB can circulate among individuals who may have no apparent symptoms. Household contact, schools, public facilities, contaminated surfaces, and inappropriate antimicrobial consumption can support the persistence and movement of resistant organisms within communities. This creates a pathway through which resistance can move between healthcare-associated and community-associated bacterial populations.
Livestock and veterinary environments constitute another important reservoir. Repeated antimicrobial exposure in animal production can select for resistant bacteria within animal gastrointestinal tracts and surrounding farm environments. These organisms may subsequently reach humans through direct animal contact, food products, manure, or contaminated environments.
Aquaculture systems may similarly sustain resistant bacteria where antimicrobial agents are introduced into aquatic production systems. Resistance determinants can circulate among microorganisms in water, sediment, farmed animals, and surrounding ecosystems.
Food-processing environments can facilitate the persistence and transfer of MDRB when resistant organisms contaminate raw materials, processing equipment, workers, or finished products. Inadequate sanitation may allow these organisms to establish persistent niches within processing facilities.
Soil and water ecosystems function as extensive environmental reservoirs. Agricultural runoff, wastewater discharge, manure application, and industrial contamination can introduce resistant bacteria and resistance genes into natural environments. These ecosystems may subsequently act as exchange zones where environmental microorganisms encounter human- and animal-associated bacteria, creating opportunities for further dissemination of antimicrobial resistance.
Routes of transmission of multidrug-resistant bacteria
MDRB is facilitated by multiple, interconnected transmission pathways that allow resistant organisms to move between individuals, animals, food systems, water sources, and the wider environment. These pathways create opportunities for resistant bacteria and their associated resistance determinants to enter new microbial communities and become established in previously unaffected populations.
Person-to-person transmission: Direct human contact represents an important pathway for MDRB dissemination, particularly within healthcare facilities and densely populated communities. Colonized or infected individuals may release resistant organisms through respiratory secretions, skin contact, fecal material, or wound exudates. Healthcare workers can inadvertently transfer these organisms between patients when hand hygiene, personal protective equipment, or other infection-control practices are inadequate. Close contact among household members may similarly facilitate transmission outside healthcare settings.
Food-borne transmission: Food can function as both a vehicle for resistant bacteria and a medium through which resistance circulates between populations. Contamination may occur during animal production, slaughter, processing, transportation, preparation, or storage. Inadequately cooked meat, contaminated fresh produce, dairy products, and other foods may introduce resistant organisms into the human gastrointestinal tract. Food-handling practices can subsequently amplify transmission when contaminated products or utensils come into contact with ready-to-eat foods.
Animal-to-human transmission: The extensive interaction between humans and domestic or food-producing animals provides another route for MDRB exchange. Resistant bacteria selected within livestock, poultry, aquaculture systems, or companion animals may reach humans through direct contact, animal-derived foods, occupational exposure, or contaminated environments. Agricultural settings can therefore act as important interfaces where resistance generated under antimicrobial selection may move beyond animal populations.
Contaminated water: Water connects otherwise distinct reservoirs of antimicrobial resistance. Hospital effluent, agricultural runoff, wastewater, and inadequately treated sewage may contain resistant bacteria and free resistance-associated genetic material. When such contaminants enter rivers, groundwater, irrigation systems, or recreational waters, they create opportunities for resistant organisms to persist, interact, and potentially reach human or animal populations.
Environmental surfaces and fomites: Frequently touched surfaces and contaminated objects can support indirect transmission, particularly where sanitation is insufficient. Medical equipment, door handles, bedding, utensils, clothing, and other fomites may become contaminated by MDRB and facilitate their movement between individuals. The persistence of some resistant organisms on environmental surfaces makes routine cleaning, disinfection, and environmental hygiene important components of transmission control.
Drivers of multidrug-resistant bacterial mergence
The MDRB is driven by a complex interaction between antimicrobial selection, microbial adaptation, environmental contamination, and human activity. Rather than arising from a single cause, multidrug resistance develops and becomes established when conditions repeatedly favor the survival and propagation of bacteria carrying advantageous resistance determinants.
Antibiotic misuse and overuse represent major sources of selective pressure. Inappropriate prescribing, unnecessary treatment, incorrect dosing, premature discontinuation of therapy, and the use of antibiotics against non-bacterial infections can expose bacterial populations to concentrations that favor resistant variants. Repeated antimicrobial exposure consequently reduces susceptible organisms while providing a survival advantage to bacteria possessing resistance mechanisms.
Antimicrobial use in agriculture creates additional opportunities for resistance selection outside clinical environments. Antibiotics administered to livestock, poultry, and farmed aquatic species can select resistant bacteria within animal microbiota. Resistant organisms and resistance genes may subsequently enter soil, water, food products, and human populations through animal waste, agricultural runoff, handling of animals, or consumption of contaminated products.
Weak infection-prevention practices further facilitate the establishment of MDRB. In healthcare facilities, inadequate hand hygiene, insufficient environmental decontamination, overcrowding, improper equipment sterilization, and delayed identification of colonized patients can allow resistant organisms to circulate between patients and healthcare workers. Similar deficiencies in community and institutional settings can sustain transmission after resistant bacteria have become established.
Poor sanitation and wastewater management provide environmental pathways for resistance dissemination. Hospital effluent, pharmaceutical residues, municipal sewage, agricultural waste, and contaminated surface waters may contain both antimicrobial residues and resistant microorganisms. Their release into inadequately treated environments can create conditions that support the persistence and exchange of resistance determinants.
Global movement of people, animals, and food accelerates the geographical spread of MDRB. International travel, migration, livestock trade, food distribution networks, and movement of agricultural products can transport resistant organisms across otherwise separated populations. These interconnected pathways allow resistance that emerges in one ecological or geographical setting to rapidly become a wider public-health concern.
One Health perspective on MDRB: connecting human, animal and environmental dimensions of AMR
AMR cannot be adequately understood by examining human infections in isolation because resistance determinants move continuously across biological and environmental boundaries. The One Health perspective recognizes that human health, animal health and environmental integrity constitute interconnected components of a single system in which antimicrobial resistance can emerge, persist and circulate. Bacteria exposed to antimicrobial agents in hospitals, farms, veterinary facilities, aquaculture systems and contaminated environments may develop or acquire resistance characteristics that subsequently enter other microbial communities.
This interconnectedness creates multiple pathways through which resistant bacteria and resistance genes can circulate. Antimicrobial use in livestock and aquaculture, for example, can impose selective pressure on microbial populations outside clinical settings. Resistant organisms may subsequently reach humans through direct animal contact, food products, water or contaminated environments. Similarly, inadequately treated hospital, agricultural and industrial wastewater may introduce antimicrobial residues and resistant microorganisms into aquatic ecosystems, creating conditions that support the maintenance and exchange of resistance determinants.
Addressing this complexity requires cross-sectoral surveillance rather than independent monitoring within individual disciplines. Surveillance systems should integrate microbiological and epidemiological information generated from hospitals, veterinary services, food-production systems, farms, wastewater facilities and environmental sampling sites. Such coordination can facilitate early recognition of emerging resistance patterns and reveal transmission pathways that might remain undetected when surveillance is restricted to a single sector.
An effective One Health response should consequently combine antimicrobial stewardship, infection prevention, environmental management, responsible agricultural practices and coordinated laboratory surveillance. Data sharing between medical, veterinary, agricultural and environmental institutions can strengthen the capacity to identify resistance hotspots and respond before resistant strains become widely established. Ultimately, containment of multidrug-resistant bacteria depends on treating antimicrobial resistance as a shared ecological and public-health problem, requiring interventions that extend beyond clinical settings and address the interconnected reservoirs through which resistance is maintained and disseminated.
Representative multidrug-resistant bacteria and clinically important resistance phenotypes
Multidrug-resistant bacteria encompass a diverse collection of organisms whose resistance profiles differ according to their species, genetic background, antimicrobial exposure, and ecological setting. Rather than representing a single bacterial category, multidrug resistance describes a phenotype in which an organism is no longer susceptible to multiple antimicrobial agents that would ordinarily provide therapeutic options. The organisms of greatest concern are those capable of combining several resistance mechanisms, thereby limiting the effectiveness of unrelated antimicrobial classes.
Among Gram-negative bacteria, extended-spectrum β-lactamase (ESBL)-producing Enterobacterales are important examples. ESBL enzymes hydrolyze a broad range of β-lactam antibiotics, particularly third-generation cephalosporins, and are frequently encountered among Escherichia coli and Klebsiella pneumoniae. Their clinical importance is amplified by the frequent co-occurrence of resistance to fluoroquinolones, aminoglycosides, and other antimicrobial classes. An additional threat is posed by metallo-β-lactamase (MBL)-producing organisms, whose enzymes can inactivate many β-lactams, including carbapenems. MBL determinants such as NDM-type carbapenemases can be carried on mobile genetic elements, creating opportunities for rapid dissemination among bacterial populations.
Carbapenem-resistant Enterobacterales (CRE) represent another major resistance phenotype. These organisms may acquire carbapenemases such as Klebsiella pneumoniae carbapenemase (KPC) or NDM, resulting in resistance to antibiotics that are often reserved for severe infections caused by otherwise resistant Gram-negative pathogens. The therapeutic challenge becomes particularly pronounced when carbapenem resistance occurs alongside resistance to several other antimicrobial categories.
Among Gram-positive bacteria, methicillin-resistant Staphylococcus aureus (MRSA) remains an important pathogen in both healthcare and community settings. Resistance to methicillin and related β-lactams is associated with alterations in penicillin-binding proteins, allowing the organism to continue cell-wall synthesis despite exposure to these agents. More advanced resistance phenotypes include vancomycin-intermediate S. aureus (VISA) and vancomycin-resistant S. aureus (VRSA). These phenotypes are particularly concerning because vancomycin has historically served as an important therapeutic option for serious infections caused by resistant Gram-positive organisms.
Vancomycin-resistant Enterococci (VRE) constitute another clinically significant group. Resistance to vancomycin can severely restrict treatment choices, particularly in patients with prolonged hospitalization or significant underlying disease. Similarly, antimicrobial-resistant Streptococcus pneumoniae can compromise the management of pneumococcal respiratory and invasive infections.
Other important examples occur across diverse bacterial species. Multidrug-resistant Acinetobacter baumannii (MDRAB) and multidrug-resistant Pseudomonas aeruginosa are prominent healthcare-associated pathogens because of their capacity to accumulate multiple resistance mechanisms and persist in clinical environments. Resistant strains of Neisseria gonorrhoeae are also increasingly problematic because resistance can progressively erode the number of reliable therapeutic options for gonorrhoea.
Outside these organisms, drug-resistant Salmonella and Shigella demonstrate how antimicrobial resistance can affect enteric pathogens, while resistant non-typhoidal Salmonella can complicate the treatment of invasive foodborne infections. Multidrug-resistant Mycobacterium tuberculosis, including extensively drug-resistant tuberculosis (XDR-TB), represents a particularly consequential form of resistance because treatment requires prolonged, complex regimens involving multiple agents.
Clinical significance and consequences of multidrug-resistant bacteria
MDRB represent a major clinical concern because their resistance phenotype can substantially alter the expected course of bacterial infections. Organisms with resistance to several antimicrobial classes have been implicated in urinary tract infections, pneumonia, bloodstream infections, wound and skin infections, gastrointestinal disease, and other invasive conditions. The clinical importance of these organisms does not arise solely from the number of antibiotics to which they are resistant, but from the consequences of that resistance for timely and effective patient management.
The clinical setting strongly influences the epidemiology of MDRB. Healthcare-associated infections may emerge where antimicrobial exposure, invasive procedures, prolonged hospitalization, and close patient-to-patient contact create favorable conditions for resistant organisms to persist and circulate. Community-associated MDRB, however, demonstrate that resistance is no longer restricted to hospitals. Resistant pathogens can circulate among individuals, animals, food systems, and environmental reservoirs, creating multiple opportunities for exposure outside healthcare facilities.
Certain patient groups are particularly vulnerable to severe MDRB infections. Individuals with compromised immunity, prolonged hospital stays, recurrent infections, previous antimicrobial exposure, indwelling medical devices, or serious underlying diseases may have reduced capacity to resist infection or fewer therapeutic options once infection occurs.
The consequences of multidrug resistance can be substantial. Failure of an initial antimicrobial regimen may permit continued bacterial multiplication and progression of disease, potentially resulting in complications, prolonged hospitalization, or invasive infection. Switching to alternative agents may also increase the risk of adverse drug reactions and treatment-related complications. From a healthcare perspective, resistant infections can generate additional diagnostic, therapeutic, and hospitalization costs while increasing demands on infection-control services.
Most importantly, MDRB can compress the therapeutic margin available to clinicians. When resistance eliminates several first-line options, treatment becomes increasingly dependent on susceptibility results and the availability of effective alternative agents. Multidrug resistance transforms an otherwise manageable bacterial infection into a more uncertain clinical problem, where delays in identifying an effective therapy may directly influence patient outcome.
Diagnosis and antimicrobial susceptibility testing in MDRB management
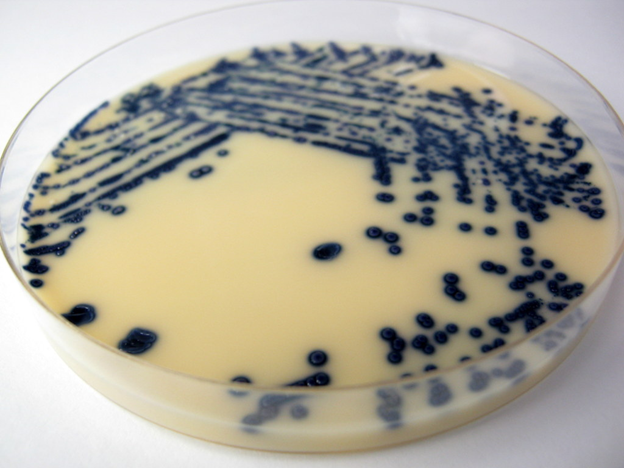
Effective management of infections caused by multidrug-resistant bacteria depends on obtaining reliable microbiological evidence rather than relying exclusively on empirical antimicrobial therapy. The diagnostic process begins with appropriate clinical sampling followed by isolation and identification of the causative organism. Specimen quality, collection procedures, transport, and laboratory processing are critical because inaccurate or contaminated samples can lead to inappropriate therapeutic decisions.
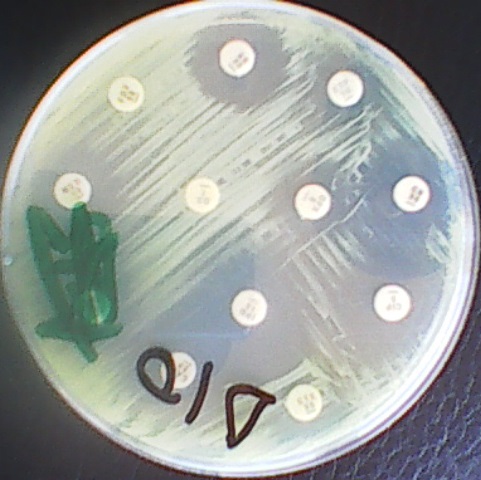
Once a bacterial isolate has been recovered, laboratory characterization can determine its susceptibility to relevant antimicrobial agents. Phenotypic antimicrobial susceptibility testing (AST) evaluates the capacity of an organism to grow in the presence of selected antibiotics. Techniques such as disk diffusion and broth microdilution can provide clinically useful susceptibility profiles, allowing isolates to be categorized according to established interpretive criteria. These results are particularly valuable when empirical therapy has failed or when the organism displays an unusual resistance phenotype.
Phenotypic testing can be complemented by molecular approaches capable of identifying specific resistance determinants. Detection of genes encoding enzymes or other resistance-associated mechanisms can provide additional information about the biological basis of resistance and, in selected circumstances, facilitate rapid recognition of clinically important resistance traits. Molecular findings should nevertheless be interpreted alongside culture results, susceptibility data, and the clinical context because detection of a resistance gene does not always correspond directly to the expressed phenotype.
The principal value of diagnostic susceptibility testing is its ability to support targeted antimicrobial selection. Instead of continuing broad empirical treatment, clinicians can use laboratory evidence to narrow therapy toward an agent with demonstrated activity against the infecting organism. This approach may improve therapeutic precision while reducing unnecessary antimicrobial exposure and limiting further selection for resistant populations.
For MDRB infections, timely communication between the microbiology laboratory and clinical team is therefore essential. Laboratory data become most useful when they are integrated with the patient’s clinical condition, infection site, previous antimicrobial exposure, and pharmacological characteristics of the available drugs. A diagnostic strategy that combines accurate pathogen identification, reliable susceptibility testing, and appropriate interpretation of resistance mechanisms provides a practical foundation for managing infections in which conventional antimicrobial choices have become increasingly constrained.
References
Bharadwaj, A., Rastogi, A., Pandey, S., Gupta, S., & Sohal, J. S. (2022). Multidrug-resistant bacteria: Their mechanism of action and prophylaxis. BioMed Research International, 2022, 5419874.
Centers for Disease Control and Prevention. (2023). Antibiotic resistance threats report. Centers for Disease Control and Prevention.
ECDC. (2023). European Antimicrobial Resistance Surveillance Network annual report 2022. European Centre for Disease Prevention and Control.
Ejikeugwu Chika, Iroha Ifeanyichukwu, Adikwu Michael and Esimone Charles (2013). Susceptibility and Detection of Extended Spectrum β-Lactamase Enzymes from Otitis Media Pathogens. American Journal of Infectious Diseases. 9(1):24-29.
Ejikeugwu Chika, Iroha Ifeanyichukwu, Adikwu Michael and Esimone Charles (2013). Susceptibility and Detection of Extended Spectrum β-Lactamase Enzymes from Otitis Media Pathogens. American Journal of Infectious Diseases. 9(1):24-29.
Madrazo, M., López-Cruz, I., Piles, L., Viñola, S., Alberola, J., Eiros, J. M., & Artero, A. (2023). Risk factors and the impact of multidrug-resistant bacteria on community-acquired urinary sepsis. Microorganisms, 11(5), 1278.
Marino, A., Maniaci, A., Lentini, M., Ronsivalle, S., Nunnari, G., Cocuzza, S., Parisi, F. M., Cacopardo, B., Lavalle, S., & La Via, L. (2025). The global burden of multidrug-resistant bacteria. Epidemiologia, 6(2), 21.
Russell, L., Pène, F., & Martin-Loeches, I. (2023). Multidrug-resistant bacteria in the grey shades of immunosuppression. Intensive Care Medicine, 49, 216–218.
World Bank. (2023). Economic impact assessment of antimicrobial resistance. World Bank.
World Health Organization. (2023). Global report on antimicrobial resistance. World Health Organization.
Discover more from Microbiology Class
Subscribe to get the latest posts sent to your email.