Tuberculosis (TB) remains an important infectious disease caused predominantly by Mycobacterium tuberculosis. M. tuberculosis is an intracellular, slow-growing bacterium with a distinctive lipid-rich cell envelope. Transmission of M. tuberculosis occurs primarily through the respiratory route when individuals with infectious pulmonary TB release airborne particles containing viable bacilli during coughing, sneezing, speaking, or other respiratory activities. Following inhalation, M. tuberculosis can reach the alveoli, where it interacts with resident immune cells and may persist within macrophages. Depending on the effectiveness of host immune responses, infection may remain latent or progress to active disease. This complex biological behavior contributes to the prolonged treatment duration required for TB and creates a continuing need for antimicrobial agents with potent activity against mycobacteria.
Isoniazid, also known as isonicotinic acid hydrazide or isonicotinyl hydrazine (INH), is one of the most important drugs used in the pharmacological management of TB. It is particularly valuable because of its strong early bactericidal activity against actively replicating M. tuberculosis. Isoniazid is generally administered as part of a multidrug regimen rather than as monotherapy for active TB, thereby reducing the likelihood of selecting resistant bacterial populations. Standard treatment of drug-susceptible TB commonly incorporates isoniazid together with other first-line agents, including rifampicin, pyrazinamide, and ethambutol. The complementary mechanisms of these drugs permit simultaneous disruption of different bacterial processes and improve the overall effectiveness of chemotherapy.
The distinctive susceptibility of M. tuberculosis to isoniazid is closely associated with the unusual architecture of its cell envelope. Unlike many conventional bacteria, mycobacteria possess a highly hydrophobic outer layer containing abundant mycolic acids that are covalently associated with components of the cell wall. This lipid-rich barrier contributes to the characteristic impermeability, environmental persistence, and reduced susceptibility of mycobacteria to numerous antimicrobial compounds. More importantly, mycolic acids are essential structural components required for maintaining the integrity and physiological function of the mycobacterial envelope. Interference with their biosynthesis therefore compromises bacterial survival.
Isoniazid is a prodrug that requires activation within susceptible mycobacterial cells. The enzyme catalase-peroxidase, encoded by the katG gene, converts isoniazid into reactive intermediates that subsequently interact with cellular targets involved in fatty-acid metabolism. A major consequence is inhibition of the enoyl-acyl carrier protein reductase InhA, an enzyme participating in the synthesis of long-chain fatty acids required for mycolic acid production. Suppression of this pathway weakens the mycobacterial cell envelope and ultimately produces lethal effects in actively dividing bacilli. Resistance to isoniazid can consequently arise through genetic alterations affecting drug activation, particularly mutations involving katG, or through changes in drug targets and associated metabolic pathways.
When resistance or intolerance limits the use of conventional therapy, treatment may require additional or alternative agents selected according to the resistance profile and clinical circumstances. Drugs used in drug-resistant TB management may include fluoroquinolones and other specialized anti-TB agents, although their selection differs substantially from older historical classifications of “second-line” therapy. Isoniazid remains both a therapeutically important compound and a significant subject of pharmacological investigation because of its distinctive activation mechanism, inhibition of mycolic acid biosynthesis, clinical utility, and association with antimicrobial resistance.
Source and structure of isoniazid
Isoniazid (INH), also known as isonicotinic acid hydrazide, is a synthetic antibacterial compound developed specifically for the treatment of tuberculosis (TB). Unlike several antimicrobial agents obtained from microbial fermentation, INH is not a natural product or a semi-synthetic derivative; it is manufactured through chemical synthesis. Its relatively simple molecular architecture contrasts with the highly complex structures of some other antitubercular agents. Isoniazid has the molecular formula C6H7N3O and a molecular weight of approximately 137.14 g/mol. Chemically, INH is classified as a pyridine carboxylic acid hydrazide, with pyridine-4-carbohydrazide being its systematic name.
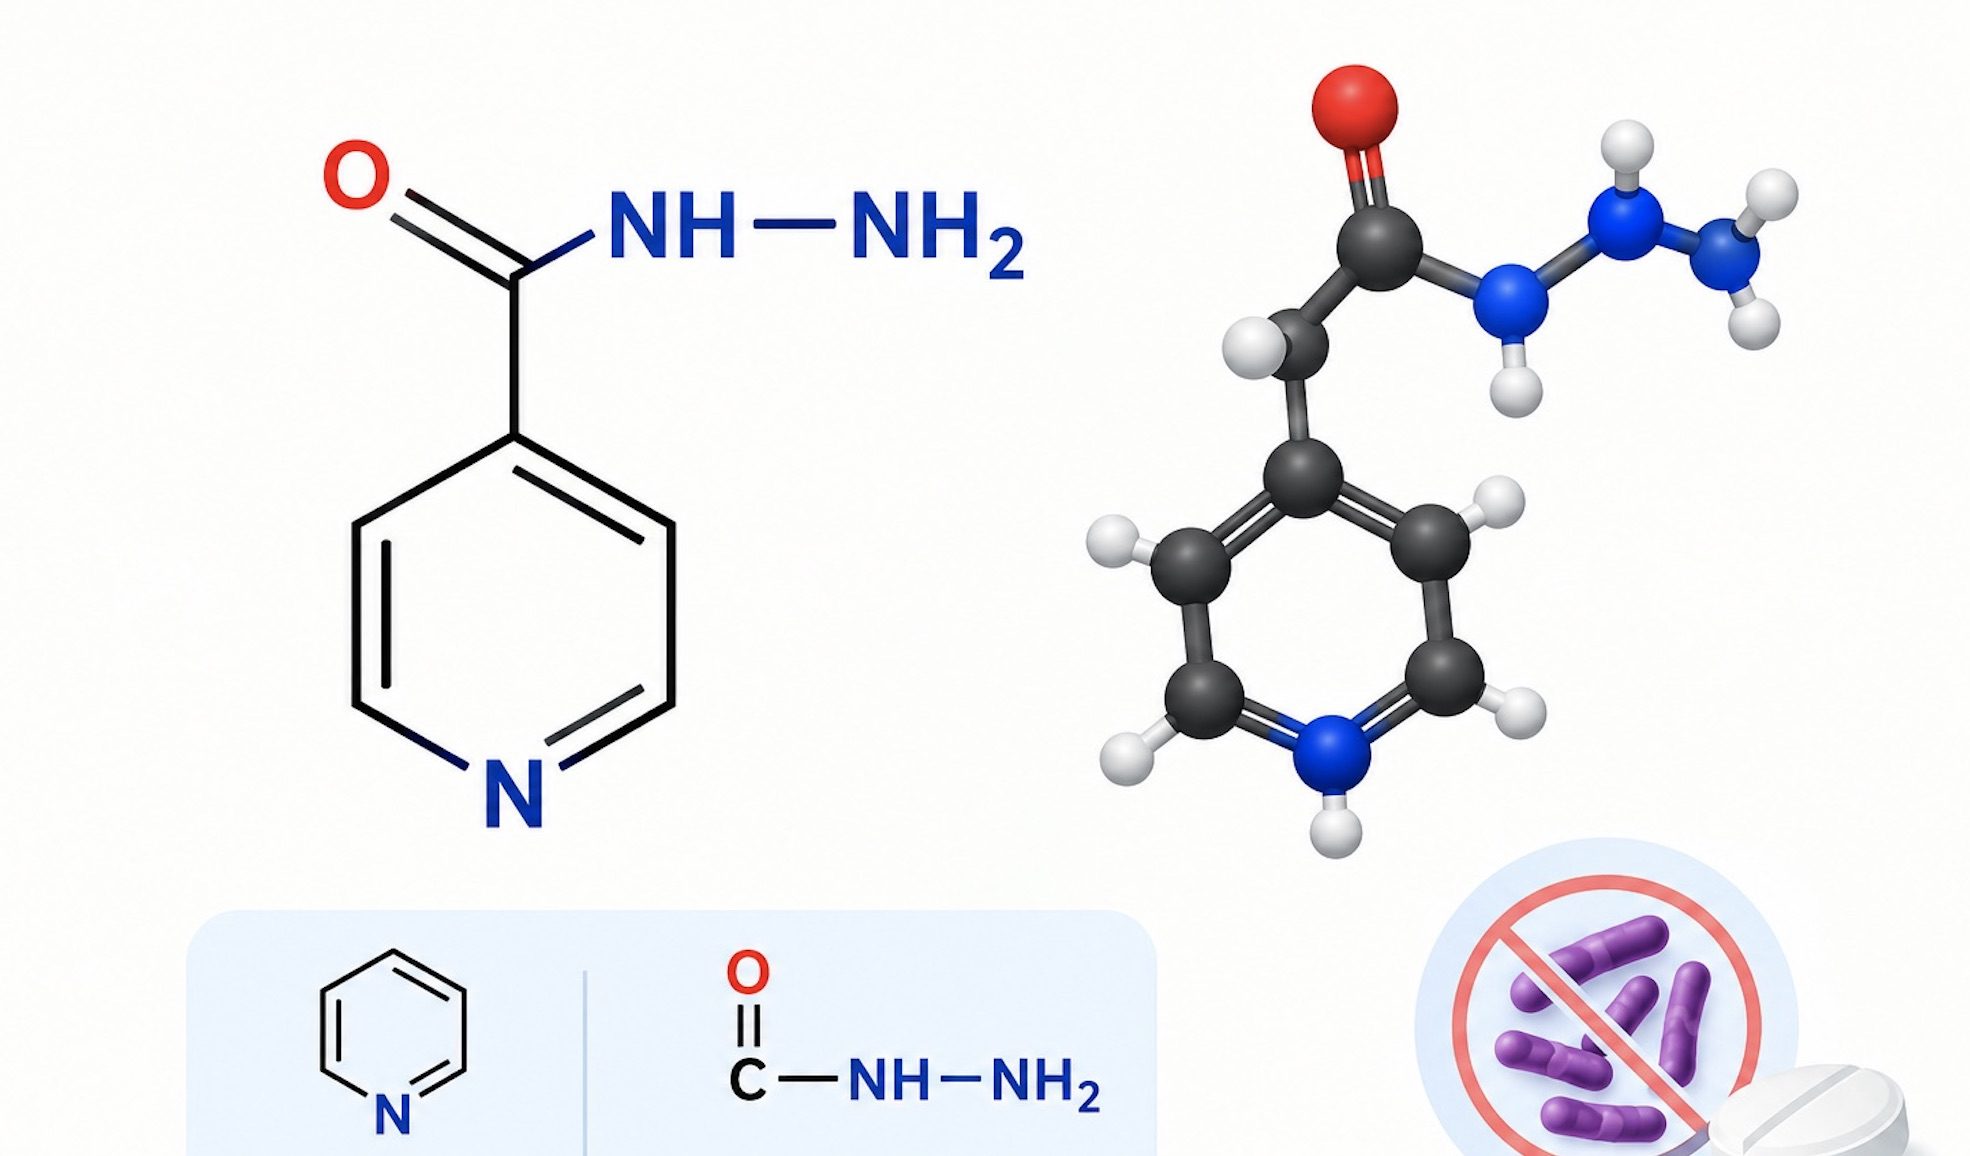
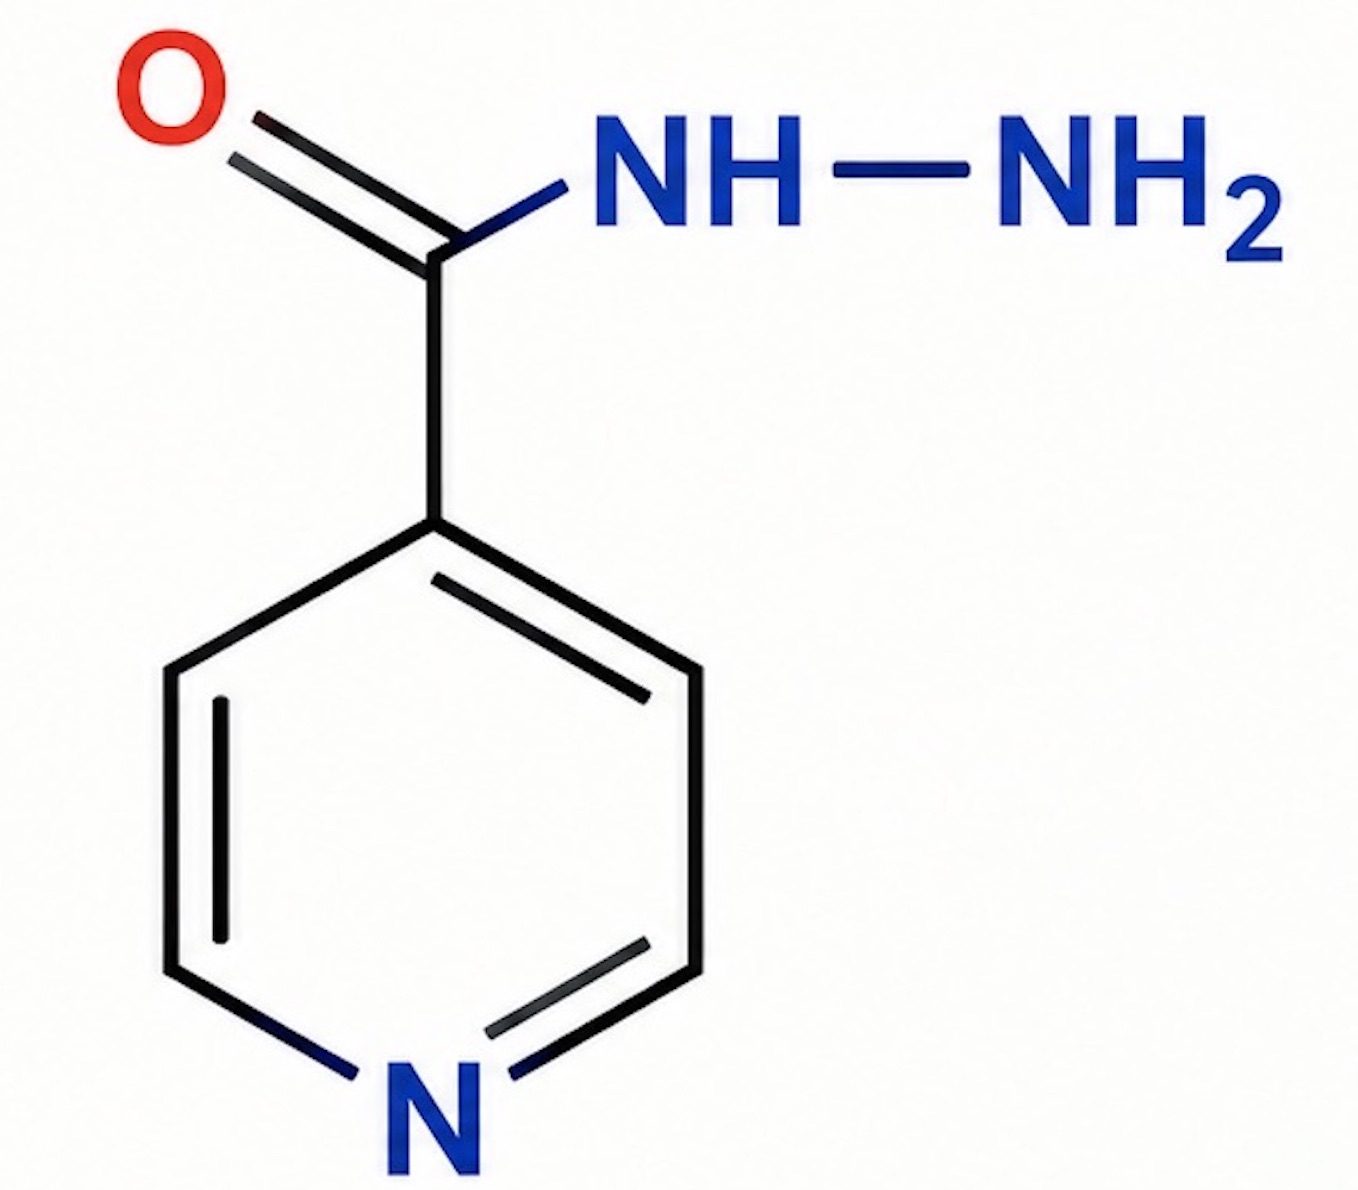
Structurally, INH should not be described as possessing a benzene nucleus. Its central aromatic framework is a six-membered pyridine ring, in which one carbon atom of the benzene-like ring is replaced by nitrogen (Figure 1). At the 4-position of the pyridine ring, a carbohydrazide substituent is attached. This arrangement produces the characteristic structure of isoniazid and provides the chemical functionality required for its antimycobacterial activity. The compound can therefore be represented as a pyridine ring bearing a –C(=O)–NH–NH2 hydrazide group. Its canonical SMILES representation is C1=CN=CC=C1C(=O)NN.
The hydrazide moiety is particularly important to the biological properties of INH. Structure-activity investigations have shown that substantial alteration or replacement of this functional group can markedly reduce or abolish antimycobacterial activity, demonstrating that the hydrazide pharmacophore is closely associated with the drug’s activity against Mycobacterium tuberculosis. Modifications of the pyridine ring can likewise influence antibacterial potency, indicating that both structural regions contribute to the molecular recognition and activation of INH.
The chemical simplicity of INH also distinguishes it from other members of antitubercular therapy. For example, rifampin is a semi-synthetic rifamycin derivative, whereas isoniazid is a defined, low-molecular-weight synthetic molecule. INH therefore represents a structurally compact drug whose therapeutic activity depends on specific chemical features rather than on the complex architecture of a natural-product scaffold.
In pharmaceutical preparations, isoniazid may occur as the free compound or as an acid-addition salt such as isoniazid hydrochloride. Its defined pyridine-hydrazide framework forms the chemical basis for subsequent enzymatic activation within M. tuberculosis and ultimately contributes to disruption of mycolic-acid biosynthesis, an essential process in the construction of the mycobacterial cell envelope.
Spectrum of activity of isoniazid
INH is a highly selective antimycobacterial agent whose principal activity is directed against members of the M. tuberculosis complex. Unlike broad-spectrum antibacterial drugs, its antimicrobial effect is closely associated with the distinctive lipid-rich envelope of mycobacteria. Isoniazid is particularly active against metabolically active and rapidly multiplying tubercle bacilli, where inhibition of essential cell-envelope biosynthesis produces a pronounced bactericidal effect. Its activity is therefore strongly influenced by the physiological state and growth rate of the organism.
Isoniazid is administered as a prodrug and requires intracellular activation by the mycobacterial catalase-peroxidase enzyme KatG. The activated drug forms reactive intermediates that interact with cellular cofactors and inhibit enzymes involved in the synthesis of mycolic acids. Mycolic acids are long-chain fatty acids that constitute a major structural component of the mycobacterial cell envelope. Their depletion compromises envelope integrity, alters permeability, and interferes with essential processes required for continued bacterial growth and survival.
The spectrum of isoniazid is relatively narrow compared with conventional broad-spectrum antibacterial agents. Its greatest clinical significance is its potent activity against M. tuberculosis, the principal causative organism of tuberculosis. Activity may also extend to other susceptible members of the M. tuberculosis complex, although susceptibility varies among individual mycobacterial species. Isoniazid has substantially less activity against many nontuberculous mycobacteria, making species identification and susceptibility testing important when these organisms are implicated.
The drug is particularly valuable against actively replicating bacilli, while organisms exhibiting metabolic quiescence may demonstrate reduced susceptibility. This distinction contributes to the rationale for combining isoniazid with other antitubercular agents during treatment. Combination therapy also reduces the likelihood that naturally occurring resistant organisms will become clinically dominant. Resistance to isoniazid commonly results from alterations affecting drug activation or its intracellular target pathways, thereby reducing susceptibility and limiting its therapeutic usefulness.
Clinical application of isoniazid
INH remains an important antituberculosis agent in the prevention and treatment of infection caused by M. tuberculosis. Its clinical value is closely associated with its potent activity against actively multiplying tubercle bacilli and its ability to penetrate tissues and body fluids, including the central nervous system. Because tuberculosis can rapidly develop resistance when exposed to isoniazid alone, the drug is generally administered as part of a multidrug regimen for active disease. The principal first-line agents traditionally associated with drug-susceptible tuberculosis are isoniazid, rifampicin (RIF), pyrazinamide (PZA), and ethambutol (EMB).
The use of isoniazid in combination therapy has two major clinical objectives: achieving effective bacterial killing while limiting the emergence of drug-resistant organisms. Mycobacteria within a tuberculosis population may contain naturally occurring variants with reduced susceptibility to individual antimicrobial agents. Administration of several drugs with different mechanisms of action therefore reduces the likelihood that a resistant subpopulation will survive and become dominant. Isoniazid consequently functions as one component of a coordinated therapeutic strategy rather than as a routine single-agent treatment for active tuberculosis.
For drug-susceptible pulmonary tuberculosis, modern treatment generally consists of an intensive phase followed by a continuation phase. A commonly used regimen includes isoniazid, rifampicin, pyrazinamide, and ethambutol during the initial phase, followed by isoniazid and rifampicin during the continuation phase when appropriate. The exact regimen and duration may vary according to disease site, drug susceptibility, patient characteristics, and applicable clinical guidelines. This structured approach allows the initial treatment to target a broad population of bacilli while the continuation phase consolidates microbiological control and reduces the risk of relapse.
Isoniazid also has an important role in the management of latent tuberculosis infection. In individuals for whom preventive treatment is indicated, isoniazid may be administered alone or in combination with another antituberculosis drug according to the selected preventive regimen. The objective in this setting differs from treatment of active disease: rather than treating a clinically manifest infection, therapy aims to eliminate persistent M. tuberculosis organisms and decrease the probability of progression to active tuberculosis.
Despite its therapeutic effectiveness, clinical use of isoniazid requires attention to adverse effects and drug interactions. Hepatotoxicity is one of its most important complications and may manifest through elevations in hepatic enzymes or, in more serious cases, clinical hepatitis. Isoniazid can also produce peripheral neuropathy, particularly in individuals with recognized risk factors. Pyridoxine (vitamin B6) supplementation is therefore frequently used in patients at increased risk of neuropathy. Regular clinical assessment and appropriate monitoring are important when prolonged therapy is prescribed.
The emergence of multidrug-resistant tuberculosis (MDR-TB) and other forms of drug-resistant disease has further emphasized the importance of susceptibility testing and individualized treatment. Resistance to isoniazid can substantially alter the composition of an effective regimen, making microbiological evaluation essential when resistance is suspected or demonstrated.
The clinical application of isoniazid extends beyond its direct antibacterial activity. Its therapeutic contribution depends on appropriate drug combinations, adherence to the prescribed regimen, recognition of resistance, and monitoring for toxicity. When appropriately selected and monitored, isoniazid remains a significant component of tuberculosis prevention and treatment strategies.
Mechanism or mode of action of isoniazid
INH is a first-line antituberculosis agent that exerts its principal activity against M. tuberculosis, the causative organism of tuberculosis. Its antibacterial effect is closely associated with disruption of mycolic-acid biosynthesis, an essential pathway involved in maintaining the distinctive, lipid-rich cell envelope of mycobacteria. Unlike many conventional antibiotics, isoniazid is a prodrug, meaning that it requires activation within the bacterial cell before it can exert its principal pharmacological effect.
Following entry into the mycobacterial cell, isoniazid is activated by the KatG catalase-peroxidase enzyme. The activated drug forms reactive intermediates that interact with cellular cofactors, particularly NAD and NADH, producing inhibitory complexes. These complexes interfere primarily with InhA, an enoyl-acyl carrier protein reductase involved in fatty-acid elongation. Inhibition of this enzyme interrupts the synthesis of long-chain fatty-acid precursors required for mycolic-acid production. The mycobacterial cell becomes progressively deficient in the lipid components necessary for constructing and maintaining its protective cell envelope.
The resulting impairment of cell-wall integrity increases the vulnerability of actively dividing bacilli and ultimately contributes to bacterial death. Isoniazid therefore demonstrates particularly strong activity against rapidly multiplying M. tuberculosis, although its activity can vary according to the physiological state and metabolic activity of the bacilli. Resistance may arise through alterations in the katG gene, which can reduce drug activation, or through changes affecting inhA and related pathways, which decrease susceptibility to inhibition.
Isoniazid is commonly administered as part of a multidrug tuberculosis regimen, because combination therapy attacks the organism through several independent biochemical pathways and reduces the likelihood of selecting resistant organisms. Other antituberculosis drugs act at different cellular targets. Rifampicin (rifampin) inhibits bacterial DNA-dependent RNA polymerase, thereby suppressing transcription and subsequent RNA synthesis. Ethambutol interferes with the synthesis of arabinogalactan components of the mycobacterial cell envelope by inhibiting arabinosyl transferases, compromising cell-wall assembly. Pyrazinamide, another major tuberculosis drug, is converted to its active form within mycobacteria and is particularly important against susceptible bacilli under acidic intracellular conditions.
Para-aminosalicylic acid (PAS) has a different mechanism and acts primarily as an antimetabolite interfering with folate-related metabolic processes in mycobacteria. It is structurally related to compounds involved in folate metabolism and ultimately disrupts pathways required for bacterial growth. Streptomycin, an aminoglycoside, acts principally on the bacterial ribosome. It binds to the 30S ribosomal subunit, interfering with translation and promoting errors in protein synthesis.
The therapeutic principle of tuberculosis chemotherapy is based on combining agents with distinct molecular targets. Isoniazid primarily compromises mycolic-acid production, whereas rifampicin affects transcription, ethambutol disrupts cell-envelope assembly, pyrazinamide alters metabolic survival mechanisms, and streptomycin interferes with protein translation. This complementary pharmacological activity provides a broader attack on the tubercle bacillus and forms the biochemical foundation of combination treatment for tuberculosis.
Bacterial resistance to isoniazid
INH remains a central component of antituberculosis therapy, but its effectiveness is challenged by the capacity of Mycobacterium tuberculosis to acquire resistance during treatment. The distinctive lipid-rich envelope of mycobacteria provides substantial intrinsic protection against antimicrobial penetration and contributes to the organism’s ability to persist under drug pressure. More importantly, resistance to INH is predominantly associated with chromosomal mutations that alter drug activation, target interaction, or intracellular redox processes rather than with conventional plasmid-mediated mechanisms. Exposure to inadequate drug concentrations, poor adherence, or prolonged drug monotherapy can select resistant bacterial populations.
INH is a prodrug that requires activation within M. tuberculosis, principally through the catalase-peroxidase enzyme KatG. Mutations affecting katG, particularly those that reduce or alter KatG-mediated activation, can substantially diminish the formation of the reactive INH-derived species required for antimicrobial activity. Another important mechanism involves alterations in inhA, which encodes enoyl-acyl carrier protein reductase, a critical component of mycolic-acid biosynthesis. Mutations in the inhA promoter may increase target expression, whereas structural changes within the target can reduce susceptibility to inhibition. Additional genetic changes involving genes such as ahpC and kasA may modify oxidative stress responses or fatty-acid metabolism and can contribute to the resistance phenotype.
The clinical significance of INH resistance extends beyond the loss of a single drug because it can influence the effectiveness of the entire treatment regimen. Resistance may occur as an isolated phenotype or alongside resistance to other first-line agents, contributing to multidrug-resistant tuberculosis (MDR-TB). The emergence of resistant subpopulations is therefore closely linked to bacterial genetic diversity, antimicrobial selection pressure, and the pharmacological environment experienced by the organism.
Pharmacokinetics of isoniazid
The pharmacokinetic behavior of isoniazid has a direct bearing on both therapeutic activity and toxicity. Following oral administration, INH is absorbed efficiently from the gastrointestinal tract, with systemic exposure influenced by food, formulation, gastric conditions, and individual metabolic characteristics. Peak plasma concentrations are generally achieved relatively rapidly after administration. Because INH is comparatively small and water soluble, it distributes widely throughout the body and can reach several clinically important compartments, including the lungs and central nervous system. Its ability to penetrate tissues contributes to its usefulness against both pulmonary and extrapulmonary M. tuberculosis infections.
Hepatic metabolism is the principal determinant of INH clearance. A major metabolic pathway is acetylation by N-acetyltransferase 2 (NAT2), producing acetylisoniazid, which undergoes further biotransformation. Genetic variation in NAT2 activity creates substantial interindividual differences in INH disposition. Individuals classified as rapid acetylators generally eliminate the drug more quickly and may have lower systemic exposure, whereas slow acetylators can maintain higher and more prolonged concentrations. These differences help explain variability in therapeutic response and susceptibility to adverse drug reactions among patients receiving similar doses.
Renal elimination also contributes to the removal of INH and its metabolites, although hepatic biotransformation is particularly important in determining overall exposure. The pharmacokinetic profile may be further modified by age, hepatic function, nutritional status, concomitant medicines, and interactions with other antituberculosis agents. Rifampicin, for example, can alter the metabolic environment in which INH is handled, potentially affecting systemic exposure.
Hepatotoxicity represents a clinically important limitation because INH itself undergoes hepatic metabolism and can generate metabolites associated with liver injury. Peripheral neuropathy is another recognized adverse effect and is associated with interference with pyridoxine-dependent pathways; pyridoxine supplementation is therefore commonly used in individuals at increased risk. The combination of rapid absorption, extensive tissue distribution, variable acetylation, and hepatic metabolism makes INH pharmacokinetics an important determinant of the balance between antimicrobial exposure and treatment-related toxicity.
References
Sankar, J., Chauhan, A., Singh, R., & Mahajan, D. (2024). Isoniazid – Historical development, metabolism associated toxicity and a perspective on its pharmacological improvement. Frontiers in Pharmacology, 15, 1441147.
O’Connor, C., Patel, P., & Brady, M. F. (2024). Isoniazid. In StatPearls. StatPearls Publishing.
Ryu, J., Lee, Y., & Kwon, J. W. (2025). Analysis of nationwide adverse event reports on isoniazid and rifampin in tuberculosis prevention and treatment in South Korea. Scientific Reports, 15, 7411.
Pugh, A. J., Barve, A. J., Falkner, K., Patel, M., & McClain, C. J. (2009). Drug-induced hepatotoxicity or drug-induced liver injury. Clinics in Liver Disease, 13(2), 277–294.
Wang, E. R., Cho, K., Harrison, G. A., Smelyansky, S. R., Soni, V., Smirnov, A., McKee, S. R., Ghabrial, G. S., Flentie, K. N., Beatty, W., Ofori-Anyinam, B., Sarkar, S., Hurtaux, T., Loza, L., Almqvist, F., Doering, T. L., Yang, J. H., Kiessling, L. L., Rhee, K. Y., Patti, G. J., & Stallings, C. L. (2025). Metabolic rewiring of isoniazid sensitivity in Mycobacterium tuberculosis. Proceedings of the National Academy of Sciences of the United States of America, 122(36), e2421336122.
Heysell, S., & Mpgama, S. (2020). Re-evaluating the role of isoniazid in treatment of pulmonary tuberculosis. The Lancet Microbe, 1, e49–e50.
Shao, Y., Song, W., Song, H., Li, G., Zhu, L., Liu, Q., & Chen, C. (2024). Incidence, outcomes, and risk factors for isoniazid-resistant tuberculosis from 2012 to 2022 in Eastern China. Antibiotics, 13(4), 378.
Micheni, L. N., Kassaza, K., Kinyi, H., Ntulume, I., & Bazira, J. (2021). Rifampicin and isoniazid drug resistance among patients diagnosed with pulmonary tuberculosis in southwestern Uganda. PLoS ONE, 16(10), e0259221.
Rizvi, F., Khan, M., Jabeen, A., et al. (2019). Studies on isoniazid derivatives through a medicinal chemistry approach for the identification of new inhibitors of urease and inflammatory markers. Scientific Reports, 9, 6738.
Vilchèze, C., & Jacobs, W. R., Jr. (2019). The isoniazid paradigm of killing, resistance, and persistence in Mycobacterium tuberculosis. Journal of Molecular Biology, 431(18), 3450–3461.
Discover more from Microbiology Class
Subscribe to get the latest posts sent to your email.