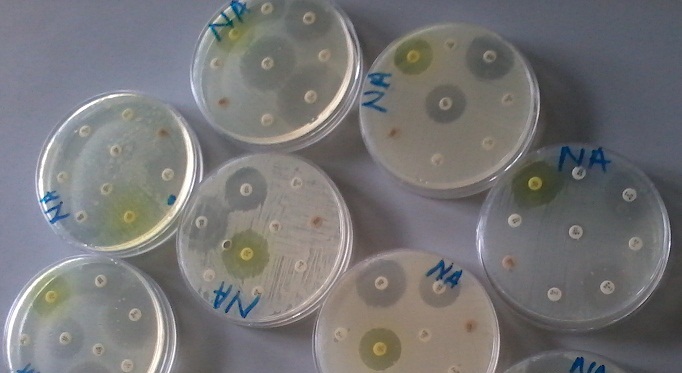
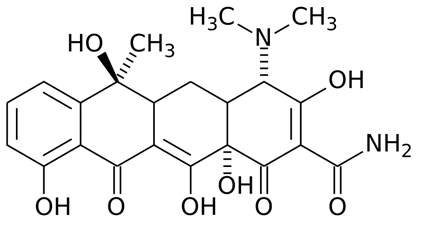
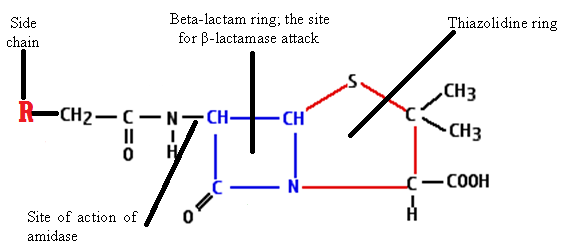
Chloramphenicol is a chemically distinctive broad-spectrum antibacterial agent that has occupied an important position in the development of antimicrobial chemotherapy. Originally isolated from Streptomyces venezuelae, chloramphenicol subsequently became one of the earliest antibiotics to be produced on a large scale by chemical synthesis. Its relatively simple molecular architecture, characterized by a dichloroacetyl group, nitrobenzene ring, and substituted propanediol moiety, has made it an interesting compound in medicinal chemistry and pharmaceutical research. Although its systemic use has declined because of concerns regarding serious hematological toxicity, chloramphenicol remains relevant in selected infections and continues to provide an important model for understanding bacterial protein synthesis, drug distribution, antimicrobial resistance, and antibiotic-associated toxicity.
Chloramphenicol is primarily a protein-synthesis inhibitor, but its molecular target distinguishes it from several other major classes of antibacterial drugs. Unlike tetracyclines and aminoglycosides, which primarily exert their effects through interactions with the bacterial 30S ribosomal subunit, chloramphenicol binds predominantly to the 50S subunit of the bacterial ribosome. More specifically, it interacts with the peptidyl-transferase center and interferes with peptide-bond formation during translation. By restricting the elongation of newly synthesized polypeptide chains, the antibiotic reduces bacterial protein production and consequently inhibits bacterial growth. Its principal action is therefore bacteriostatic, although the ultimate response can vary according to the bacterial species, drug concentration, and susceptibility of the organism.
The interaction of chloramphenicol with the 50S ribosomal subunit also provides an interesting point of comparison with macrolide antibiotics such as erythromycin. Both agents target the 50S bacterial ribosome, but they do not bind in exactly the same manner or occupy identical molecular sites. Macrolides generally associate with the nascent peptide exit tunnel and interfere with translation, whereas chloramphenicol acts primarily at the peptidyl-transferase center. Thus, their shared association with the 50S subunit reflects a common ribosomal target rather than an identical mechanism of molecular interaction. This distinction is important when considering antimicrobial pharmacology, because differences in binding sites can influence antibacterial activity, resistance mechanisms, and interactions with other ribosome-targeting antibiotics.
Chloramphenicol exhibits activity against a broad spectrum of microorganisms, including numerous Gram-positive and Gram-negative bacteria as well as several anaerobic organisms. Historically, this extensive antibacterial coverage, together with its relatively low cost and favorable tissue penetration, contributed to its widespread therapeutic application. The drug is capable of reaching concentrations in several body compartments that are difficult for many antimicrobial agents to penetrate. Its penetration into the central nervous system is particularly significant because it can achieve therapeutically relevant concentrations in cerebrospinal fluid, contributing to its historical use in serious bacterial infections such as meningitis.
The apparent selectivity of chloramphenicol arises from its preferential interaction with bacterial ribosomes. This selectivity is not absolute. Human cells contain mitochondria that possess ribosomes with bacterial evolutionary characteristics, and chloramphenicol can interfere with mitochondrial protein synthesis at sufficiently high exposure. This property provides an important biological explanation for some of the drug’s adverse effects. In particular, inhibition of mitochondrial function has been associated with effects on rapidly developing or metabolically active tissues. Chloramphenicol can produce reversible bone-marrow suppression and, more rarely, potentially fatal idiosyncratic aplastic anemia. Its use therefore requires careful assessment of potential benefits and risks.
The safety concerns become especially important in vulnerable populations. Newborn infants have limited capacity to metabolize and eliminate chloramphenicol efficiently, which can lead to excessive systemic concentrations and the characteristic condition known as gray baby syndrome. Pregnancy and infancy consequently require particular consideration when systemic chloramphenicol therapy is contemplated. Hepatic metabolism, primarily through glucuronidation, also contributes substantially to the drug’s pharmacokinetic behavior and helps determine its duration of action and potential for accumulation.
Chloramphenicol represents a valuable intersection of antimicrobial pharmacology, medicinal chemistry, microbiology, and pharmaceutical science. Its broad antibacterial spectrum and distinctive 50S ribosomal mechanism are balanced by clinically important toxicity considerations. The compound therefore continues to serve as an informative example of how antimicrobial selectivity can coexist with significant host-cell effects, demonstrating the complex relationship between molecular target, pharmacokinetics, therapeutic efficacy, and drug safety.
Sources of chloramphenicol
Chloramphenicol is a broad-spectrum antibiotic that was originally obtained from a natural microbial source. It was first isolated in 1947 from a soil sample collected in Venezuela and was subsequently identified as a metabolite produced by the bacterium Streptomyces venezuelae. This discovery established chloramphenicol as one of the early antibiotics derived from actinomycetes, a group of filamentous, soil-dwelling bacteria known for producing numerous biologically active compounds.
The principal natural source of chloramphenicol is Streptomyces venezuelae, which produces the antibiotic through a complex biosynthetic pathway involving several enzymatic reactions. During natural biosynthesis, the microorganism assembles the characteristic chemical structure of chloramphenicol from precursor molecules. The antibiotic is then accumulated in the culture medium, from which it can be recovered and purified using appropriate extraction and purification techniques.
Although chloramphenicol was initially obtained through microbial fermentation, commercial production has largely shifted toward chemical synthesis. Modern synthetic methods provide greater control over production, yield, purity, and consistency than reliance solely on microbial fermentation. Chemical synthesis involves the stepwise construction of the chloramphenicol molecule, including formation and modification of its characteristic nitrobenzene ring, as well as the appropriate side-chain structure and stereochemistry required for antibacterial activity.
Thus, the sources of chloramphenicol can broadly be classified into two categories: natural biological production and chemical synthesis. The natural source is principally S. venezuelae, while industrial production can employ synthetic chemical processes. The historical discovery of chloramphenicol from S. venezuelae remains significant because it demonstrated the pharmaceutical potential of soil microorganisms as sources of antimicrobial agents. Today, controlled chemical manufacturing is important for producing chloramphenicol of consistent pharmaceutical quality and meeting therapeutic requirements.
Structure of chloramphenicol
Chloramphenicol is a naturally occurring, broad-spectrum antibiotic with a relatively small and distinctive chemical structure. Unlike many other antibiotics that inhibit bacterial protein synthesis, such as tetracyclines and macrolides, chloramphenicol possesses a characteristic nitrobenzene ring as an important component of its molecular structure. Its chemical formula is C11H12Cl2N2O5, and its molecular structure contains several functional groups that contribute to its antimicrobial activity and physicochemical properties (Figure 1).
The basic structure of chloramphenicol consists of a p-nitrobenzene ring, a dichloroacetamide group, and a propanediol side chain containing hydroxyl groups. The nitro group attached to the aromatic ring is particularly important for the biological and chemical characteristics of the molecule. The presence of two chlorine atoms in the dichloroacetamide portion also contributes to the compound’s overall chemical properties. In addition, the hydroxyl groups influence its solubility, formulation, and interaction with biological molecules.
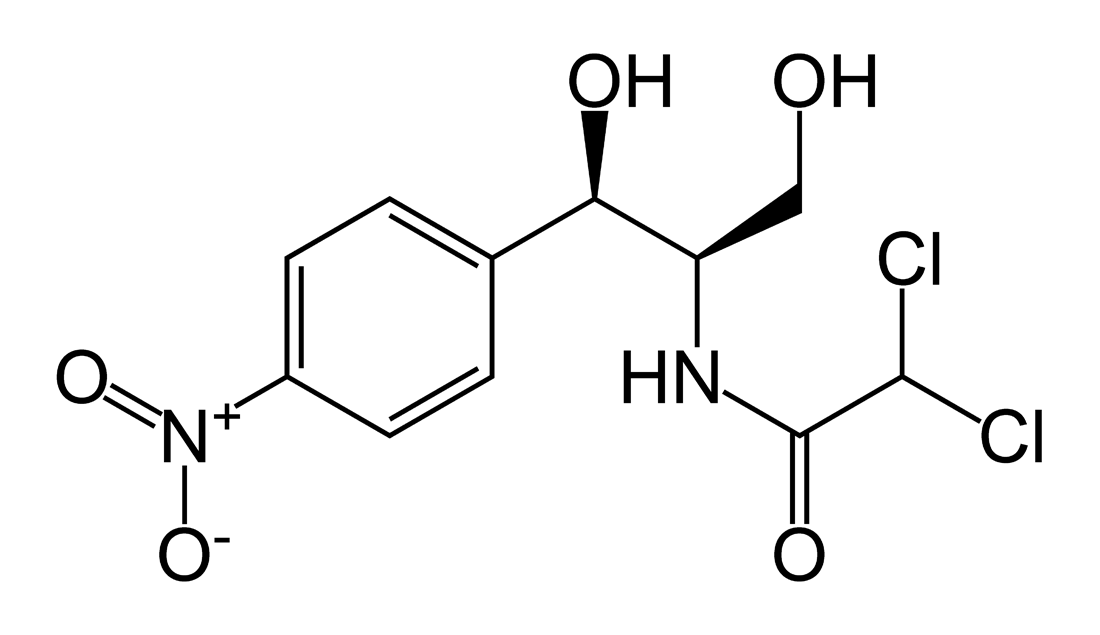
Chloramphenicol contains two stereogenic centers, meaning that its three-dimensional configuration is important for biological activity. The naturally active form has a specific stereochemical arrangement, while different stereoisomers may have substantially different antimicrobial activity. The stereochemistry of chloramphenicol is an important consideration in its chemical synthesis and pharmaceutical production.
The molecular structure enables chloramphenicol to interact with the 50S subunit of the bacterial ribosome, where it inhibits bacterial protein synthesis. Although the nitrobenzene ring is an important structural feature, the antimicrobial activity of chloramphenicol depends on the molecule as a whole and on the appropriate arrangement of its functional groups. Structural features therefore influence both its pharmacological activity and its interaction with bacterial ribosomal targets.
Chemical modification of chloramphenicol can produce derivatives with altered solubility, stability, absorption, and pharmaceutical characteristics. Examples include chloramphenicol palmitate and chloramphenicol sodium succinate, which are formulated as prodrug or ester derivatives to modify administration and pharmacokinetic properties. These modifications do not simply replace the nitrobenzene ring; rather, they alter specific functional groups of the parent molecule while retaining the structural features necessary for subsequent conversion to active chloramphenicol.
The structure of chloramphenicol can be understood in terms of three major components: the nitrobenzene ring, dichloroacetamide group, and substituted propanediol moiety. The combination and spatial arrangement of these groups give chloramphenicol its characteristic chemical and biological properties and distinguish it structurally from other inhibitors of bacterial protein synthesis.
Clinical application of chloramphenicol
Chloramphenicol is a broad-spectrum, bacteriostatic antimicrobial agent that inhibits bacterial protein synthesis by binding reversibly to the 50S subunit of the bacterial ribosome. Historically, it played an important role in the treatment of a wide range of serious bacterial infections, including typhoid fever, bacterial meningitis, rickettsial infections, and infections caused by Chlamydia species. However, its clinical use has declined considerably because of the risk of serious and potentially fatal adverse effects, particularly bone-marrow suppression and aplastic anaemia. Chloramphenicol is now generally reserved for selected situations in which alternative antibiotics are ineffective, contraindicated, unavailable, or inappropriate.
One of the classical applications of chloramphenicol is the treatment of enteric (typhoid) fever caused by Salmonella enterica serovar Typhi. Although chloramphenicol was historically regarded as an important treatment for typhoid fever, widespread bacterial resistance and the availability of safer antibiotics have substantially reduced its routine use. Its role may therefore be considered in carefully selected cases based on antimicrobial susceptibility testing and local treatment guidelines.
Chloramphenicol has also been used in the management of serious bacterial meningitis because of its excellent penetration into the cerebrospinal fluid. It has activity against several organisms responsible for meningitis and may be considered when conventional first-line antibiotics cannot be used because of allergy, resistance, or other clinical circumstances. However, treatment decisions should be guided by current antimicrobial guidelines and microbiological data.
Another important application is the treatment of certain rickettsial infections. Chloramphenicol has activity against several Rickettsia species and has historically been used when alternative agents, particularly tetracyclines, are unsuitable. It has also demonstrated activity against certain Chlamydia species, although it is not generally the preferred treatment for most chlamydial infections because more effective and safer alternatives are available.
The major limitation to chloramphenicol therapy is its toxicity. Reversible dose-related bone-marrow suppression may occur during treatment, while rare idiosyncratic aplastic anaemia can develop and may be fatal. In neonates and young infants, impaired drug metabolism can result in accumulation and a potentially serious condition known as gray baby syndrome. Other adverse effects include gastrointestinal disturbances, hypersensitivity reactions, and neurological effects such as peripheral neuritis with prolonged treatment.
Because of these safety concerns, chloramphenicol should be used only when its potential benefits clearly outweigh its risks. Appropriate dosing, duration of therapy, monitoring, and consideration of alternative antimicrobial agents are essential. Chloramphenicol remains a clinically valuable antibiotic for selected serious infections, but its modern role is highly restricted compared with its historical importance.
Spectrum of activity of chloramphenicol
Chloramphenicol is a broad-spectrum antimicrobial agent with activity against a wide variety of Gram-positive and Gram-negative bacteria. It is primarily bacteriostatic, meaning that it inhibits bacterial growth and multiplication rather than directly killing the organisms. Its antibacterial activity results from inhibition of bacterial protein synthesis. Chloramphenicol enters susceptible bacterial cells and binds reversibly to the 50S subunit of the bacterial ribosome, where it inhibits the peptidyl-transferase activity required for peptide-bond formation. Bacterial protein synthesis is disrupted, leading to inhibition of bacterial growth.
The antibacterial spectrum of chloramphenicol includes several important Gram-positive organisms. It has activity against certain Streptococcus species and other susceptible Gram-positive bacteria. However, because of the availability of safer and more effective antibiotics, chloramphenicol is not routinely used as a first-line treatment for most infections caused by these organisms. Its use is generally reserved for selected clinical situations in which alternative antimicrobial agents are unsuitable or ineffective.
Chloramphenicol also demonstrates significant activity against a range of Gram-negative bacteria. Important susceptible organisms include Haemophilus influenzae, Neisseria meningitidis, and Neisseria gonorrhoeae, although resistance can occur. It has historically been particularly important in the treatment of serious infections caused by H. influenzae, including meningitis. Chloramphenicol also has activity against certain members of the family Enterobacteriaceae, although its clinical usefulness against these organisms has been considerably reduced by the development and spread of antimicrobial resistance.
In addition to its activity against common Gram-positive and Gram-negative bacteria, chloramphenicol has activity against some anaerobic bacteria. This broad spectrum contributed to its historical use in severe systemic infections, particularly when the causative organism was unknown or when penetration into difficult-to-reach body sites was required. Chloramphenicol has also been used in selected cases of typhoid fever caused by Salmonella enterica serovar Typhi, although resistance and the availability of alternative antibiotics have substantially limited this application.
Although chloramphenicol is generally bacteriostatic, it can exhibit bactericidal activity against certain susceptible organisms under appropriate conditions. This effect is particularly relevant to some strains of H. influenzae and N. meningitidis. Therefore, describing chloramphenicol simply as either bacteriostatic or bactericidal is an oversimplification; its effect may depend on the bacterial species, strain, drug concentration, and other environmental factors.
Chloramphenicol possesses a broad antibacterial spectrum encompassing several clinically important Gram-positive, Gram-negative, and anaerobic bacteria. Nevertheless, its serious potential adverse effects, particularly bone-marrow suppression and rare aplastic anaemia, together with increasing antimicrobial resistance, have restricted its use to specific clinical circumstances.
Mechanism or mode of action of chloramphenicol
Chloramphenicol is a broad-spectrum antimicrobial agent that inhibits bacterial growth primarily by interfering with protein synthesis. Its antibacterial activity is based on its ability to penetrate bacterial cells and interact with the bacterial ribosome, the cellular structure responsible for translating messenger RNA (mRNA) into proteins. Chloramphenicol acts mainly at the 50S subunit of the bacterial ribosome, where it inhibits the enzymatic activity required for peptide-bond formation during translation.
After entering susceptible bacterial cells, chloramphenicol binds reversibly to a specific site on the 50S ribosomal subunit, particularly near the peptidyl transferase center. The peptidyl transferase activity of the 50S ribosomal subunit catalyzes the formation of peptide bonds between amino acids during protein synthesis. By binding to this region, chloramphenicol interferes with the proper positioning and transfer of the growing peptide chain, thereby inhibiting peptide-bond formation.
Normally, bacterial protein synthesis occurs through several stages. During translation, aminoacyl-tRNA molecules deliver specific amino acids to the ribosome according to the genetic information encoded by mRNA. The ribosome then links these amino acids together through peptide bonds, producing a growing polypeptide chain. Chloramphenicol disrupts this process by inhibiting the peptidyl transferase reaction. Consequently, the addition of new amino acids to the growing peptide chain is prevented or markedly reduced.
The inhibition of protein synthesis ultimately interferes with the production of essential bacterial proteins, including enzymes and structural proteins required for growth, replication, metabolism, and cellular maintenance. Because bacteria depend on continuous protein synthesis for normal cellular function, inhibition of translation suppresses bacterial multiplication and growth. For this reason, chloramphenicol is generally described as a bacteriostatic antibiotic, meaning that it primarily inhibits the growth and reproduction of susceptible bacteria rather than directly destroying them.
However, the bacteriostatic effect is not absolute. Chloramphenicol may exhibit bactericidal activity against certain bacterial species or under particular conditions, depending on factors such as the bacterial organism, drug concentration, susceptibility of the pathogen, and site of infection. Therefore, its effect can vary from one microorganism to another. An important feature of chloramphenicol is its relatively selective action against bacterial protein synthesis.
Bacterial ribosomes are 70S ribosomes, consisting of 30S and 50S subunits, whereas human cytoplasmic ribosomes are 80S, consisting of 40S and 60S subunits. This structural difference allows chloramphenicol to preferentially interfere with bacterial translation. Chloramphenicol can also affect mitochondrial protein synthesis in human cells because mitochondrial ribosomes possess evolutionary similarities to bacterial ribosomes. This contributes to some of the drug’s clinically important toxic effects, particularly with prolonged or systemic exposure.
The principal mechanism of action of chloramphenicol involves binding to the bacterial 50S ribosomal subunit and inhibiting peptidyl transferase activity. This prevents normal peptide-bond formation and consequently inhibits bacterial protein synthesis. The resulting depletion of essential proteins suppresses bacterial growth and reproduction, making chloramphenicol predominantly bacteriostatic, although it can be bactericidal against selected microorganisms.
Bacterial resistance to chloramphenicol
Bacterial resistance to chloramphenicol is an important mechanism that reduces the clinical effectiveness of this broad-spectrum antimicrobial agent. Resistance may be acquired through chromosomal mutations or, more commonly in many bacterial species, through transferable genetic elements such as plasmids, transposons, and integrons. Plasmids carrying chloramphenicol-resistance determinants may also contain genes that confer resistance to other antimicrobial classes, including tetracyclines, aminoglycosides, sulfonamides, and β-lactam antibiotics. Exposure to one antimicrobial agent can contribute to the selection and persistence of bacteria carrying multiple resistance determinants.
Several mechanisms contribute to chloramphenicol resistance. The most clinically significant mechanism is enzymatic inactivation by chloramphenicol acetyltransferase (CAT). CAT modifies chloramphenicol by acetylation, reducing its ability to bind effectively to the bacterial 50S ribosomal subunit and thereby allowing bacterial protein synthesis to continue. Another mechanism involves reduced intracellular accumulation of the drug. This may result from decreased membrane permeability or, particularly in Gram-negative bacteria, increased activity of efflux pumps that actively remove chloramphenicol from the bacterial cell.
Resistance can also arise through alterations in the drug’s target. Mutations affecting the 50S ribosomal subunit, particularly the region of the 23S ribosomal RNA to which chloramphenicol binds, may reduce the affinity of the drug for its target. Such modifications can diminish inhibition of the peptidyl-transferase activity required for bacterial protein synthesis. Bacteria may acquire resistance through regulatory changes that increase the expression of resistance-associated proteins.
Despite these mechanisms, chloramphenicol remains active against certain bacterial pathogens, including some organisms resistant to multiple other antimicrobial agents. Its continued activity in some settings may partly reflect its comparatively restricted use in many countries because of concerns about serious adverse effects, particularly bone-marrow toxicity and aplastic anaemia. Resistance remains clinically important, and susceptibility testing is essential when chloramphenicol is being considered for treatment.
Pharmacokinetics of chloramphenicol
Chloramphenicol is a broad-spectrum antibiotic that can be administered by several routes, including oral, intravenous, intramuscular, and topical routes, depending on the clinical indication and formulation. Following oral administration, chloramphenicol is generally well absorbed from the gastrointestinal tract, with high and relatively predictable systemic bioavailability. Its absorption is influenced by the pharmaceutical formulation, and preparations such as chloramphenicol palmitate may require conversion to the active drug before exerting their therapeutic effects. Because of its high lipid solubility, chloramphenicol readily crosses biological membranes and is extensively distributed throughout the body.
The drug has a relatively large apparent volume of distribution, reflecting its extensive penetration into body tissues and fluids. Chloramphenicol achieves therapeutic concentrations in many organs and tissues, including the lungs, liver, kidneys, and central nervous system (CNS). Importantly, it crosses the blood–brain barrier effectively and can achieve significant concentrations in the cerebrospinal fluid (CSF), even in the absence of marked meningeal inflammation. This property historically contributed to its use in the treatment of serious CNS infections such as bacterial meningitis. Chloramphenicol undergoes extensive hepatic metabolism, primarily through glucuronidation, to produce an inactive metabolite.
This metabolic pathway is particularly important because the capacity to metabolize the drug is immature in newborn infants, increasing the risk of drug accumulation and toxicity. A smaller proportion of the administered drug is eliminated unchanged through the kidneys. The elimination half-life is generally several hours in healthy adults but may be considerably prolonged in neonates and patients with impaired hepatic function. Pharmacokinetic considerations, including age, liver function, and dosage, are important when chloramphenicol is used clinically. Its extensive tissue distribution and CNS penetration are major pharmacological characteristics, but these same properties necessitate careful dosing and monitoring.
Side effects or toxicity of chloramphenicol
Although chloramphenicol is an effective broad-spectrum antimicrobial agent, its potentially serious adverse effects have substantially limited its routine clinical use. One of its most important toxicities is bone-marrow suppression. This may occur as a dose-related and generally reversible reduction in blood-cell production during treatment. More seriously, chloramphenicol has been associated with idiosyncratic aplastic anaemia, a rare but potentially fatal disorder characterized by severe impairment of bone-marrow function and reductions in multiple blood-cell lines. Because this reaction is unpredictable and may occur even after treatment has ended, chloramphenicol is generally reserved for situations in which alternative antibiotics are unsuitable.
Other adverse effects may include gastrointestinal disturbances, headache, skin reactions, and hypersensitivity reactions. Prolonged treatment or high systemic exposure can increase the likelihood of adverse effects and therefore requires appropriate clinical monitoring. Chloramphenicol may also cause neurological adverse effects, including peripheral neuropathy and optic neuritis, particularly following prolonged therapy. Patients receiving systemic treatment may therefore require monitoring for clinical signs of haematological or neurological toxicity.
A particularly serious form of toxicity occurs in newborn infants. Neonates have limited capacity to metabolize and eliminate chloramphenicol because hepatic glucuronidation and renal elimination are not fully developed. Accumulation of the drug can produce gray baby syndrome, which may present with vomiting, abdominal distension, cyanosis, hypotension, hypothermia, and cardiovascular collapse. For this reason, systemic chloramphenicol should generally be avoided in neonates unless there is a compelling clinical indication and appropriate monitoring is available. Similarly, its use during pregnancy requires careful assessment of potential maternal and fetal risks. The serious haematological, neurological, and neonatal toxicities of chloramphenicol mean that its therapeutic benefits must be carefully weighed against its potential risks.
References
Felix, N. S. (1956). Chloramphenicol: Applied pharmacology. Pediatric Clinics of North America, 3(2), 317–327.
Gruhzit, O. M., Fisken, R. A., Reutner, T. F., & Martino, E. (1949). Chloramphenicol (Chloromycetin), an antibiotic: Pharmacological and pathological studies in animals. The Journal of Clinical Investigation, 28(5, Part 1), 943–952.
Hahn, F. E. (1983). Chloramphenicol. In F. E. Hahn (Ed.), Modes and mechanisms of microbial growth inhibitors(Antibiotics, Vol. 6). Springer.
Livingston, R. J., Butterworth, J. W., & Belt, P. (2013). Reaction or infection: Topical chloramphenicol treatment. Annals of the Royal College of Surgeons of England, 95(1), e20–e21.
Papich, M. G. (2013). Antimicrobial drugs. In R. J. Washabau & M. J. Day (Eds.), Canine and feline gastroenterology(pp. 471–476). W. B. Saunders.
Pongs, O. (1979). Chloramphenicol. In F. E. Hahn (Ed.), Mechanism of action of antibacterial agents (Antibiotics, Vol. 5/1). Springer.
Smith, A. L., & Weber, A. (1983). Pharmacology of chloramphenicol. Pediatric Clinics of North America, 30(1), 209–236.
Wiest, D. B., Cochran, J. B., & Tecklenburg, F. W. (2012). Chloramphenicol toxicity revisited: A 12-year-old patient with a brain abscess. Journal of Pediatric Pharmacology and Therapeutics, 17(2), 182–188.
Eliakim-Raz, N., Lador, A., Leibovici-Weissman, Y., Elbaz, M., Paul, M., & Leibovici, L. (2015). Efficacy and safety of chloramphenicol: Joining the revival of old antibiotics? Systematic review and meta-analysis of randomized controlled trials. Journal of Antimicrobial Chemotherapy, 70(4), 979–996.
Discover more from Microbiology Class
Subscribe to get the latest posts sent to your email.