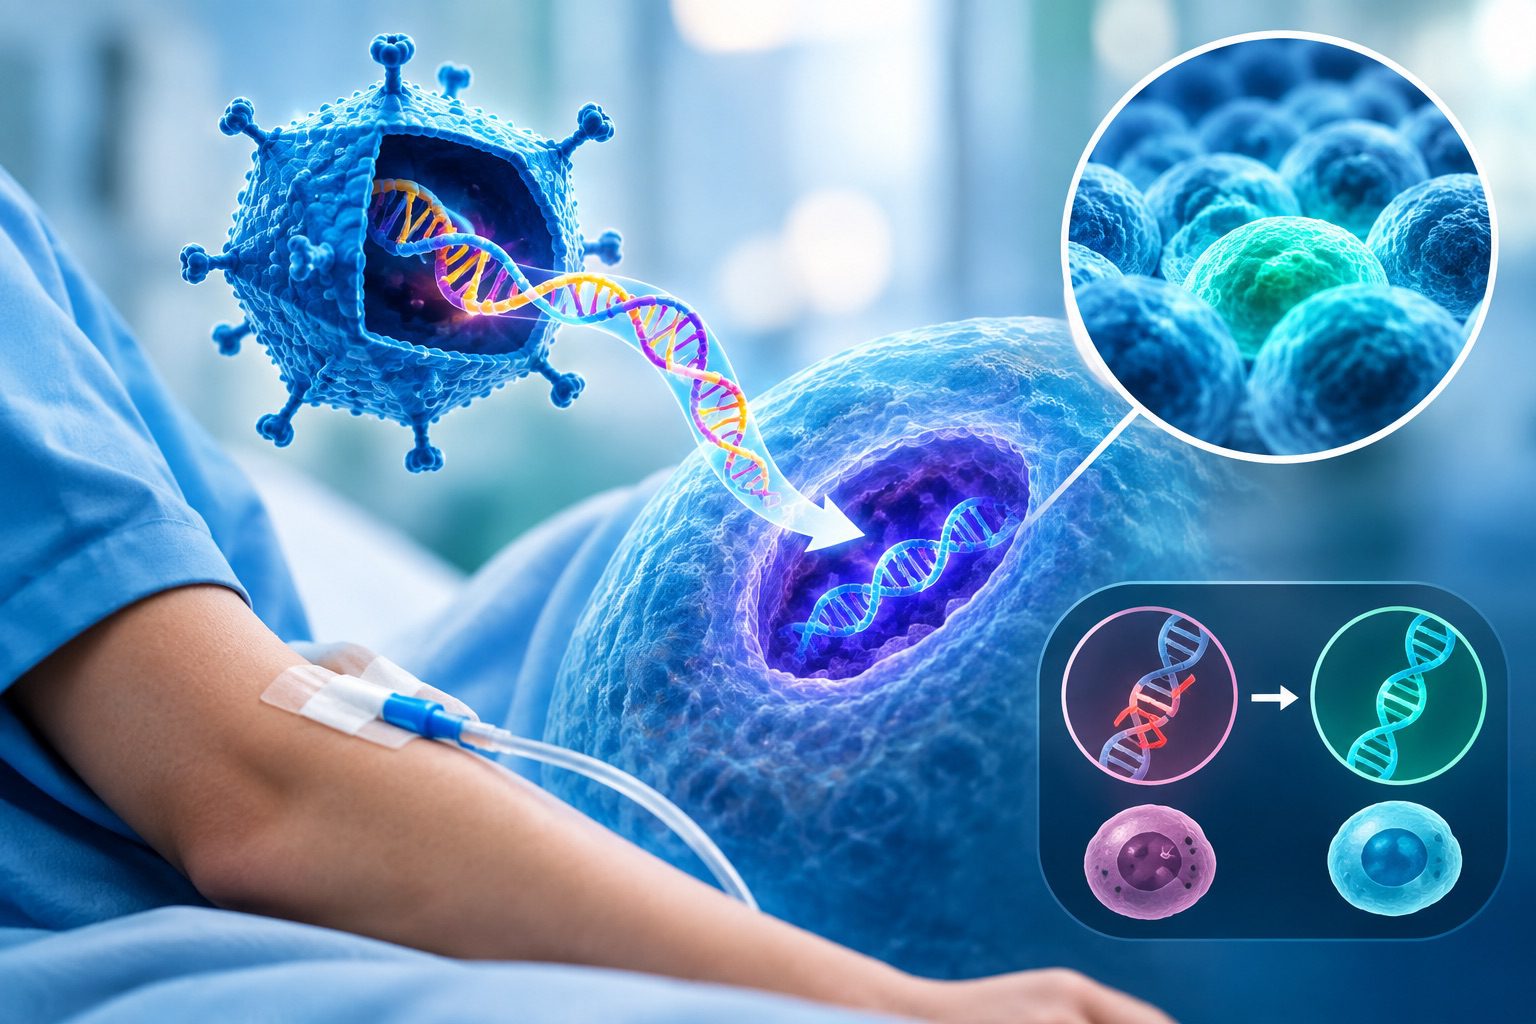
Gene therapy is used to deliver functional genes or therapeutic DNA into target cells and tissues of patients suffering from genetic disorders so that the defective genes in their body can be corrected, repaired or replaced with the normal genes. Though they may provide the only clue for treating some genetic diseases; gene therapy is not without some drawbacks and ethical issues which have impeded their outright global applications in hospitals. At present, gene therapy is still largely regarded as an emerging and highly specialized field, with many approaches remaining within the realm of controlled clinical trials. However, it has progressed beyond purely experimental use in certain cases, with several therapies now approved for clinical application.
Notable examples include Zolgensma for treating Spinal Muscular Atrophy, Luxturna for inherited retinal diseases that cause blindness, and (chimeric antigen receptor) CAR T-cell therapy for certain forms of Leukemia. These examples highlight the gradual transition of gene therapy from experimental research to real-world clinical practice. One of the major problems associated with the application of gene therapy for the management of genetic diseases is that gene therapy is short-lived; and the therapeutic genes or DNA inserted into the recipient hosts patient may experience difficulty integrating into the rapidly dividing cells in the host.
This is why gene therapy is often administered at several times so that the repair of the defective genes could be efficient. Other problems associated with the use of gene therapy include the reversion of the viral particle used into becoming a pathogen in the recipient host and the possibility of the virus triggering an adverse immunological response in the body of the patient. The inserted therapeutic DNA may misfire and enter a non-target cell or tissue; and the viral vector used (i.e. viruses) may affect other cells of the body apart from the target cell.
Ethically, gene therapy is not accepted in some quarters and this has limited the practice to merely clinical trials and especially for diseases for which there is no known available medical cure. As earlier said, gene therapy are usually of two types i.e. somatic gene therapy (in which body cells are targeted) and germ line gene therapy (in which the germ cells are targeted). While gene therapy involving somatic cells may not be transferrable or inherited by the next generation, gene therapy involving the egg or sperm cells (i.e. the germ cells) can be passed on to the next generation and this may occur in cases where the inserted gene misses and enter reproductive cells.
Another ethical issue surrounding gene therapy application is the notion that it uses viral vectors to deliver functional genes into host cells. The use of viruses has posed some safety concerns about gene therapy since viral particles could be over-expressed in vivo or cause other pathological changes in the recipient host. The development of novel systems for the efficient delivery of therapeutic genes or DNA is critical to the clinical use of gene therapy in managing genetic disorders, and further research into this important field of molecular medicine will go a long way in coming up with sustainable measures of using the technique in clinical medicine.
Risks of gene therapy
Gene therapy represents a powerful and promising approach in modern medicine, offering the possibility of treating or even curing genetic disorders at their root cause. However, the same complexity that makes gene therapy effective also introduces a wide spectrum of biological and clinical risks. These risks arise from the intricate nature of gene regulation, cellular interactions, and the challenges of safely delivering genetic material into living systems. These risks are not purely hypothetical. Several have been documented in preclinical studies and human clinical trials, underscoring the need for caution, rigorous testing, and continuous monitoring. Understanding these risks is essential for clinicians, researchers, and patients when evaluating the safety and feasibility of gene therapy interventions.
The risks associated with gene therapy reflect the complexity of intervening at the genetic level within living organisms. From immune reactions and genomic instability to long-term uncertainties and potential heritable effects, these challenges highlight the need for cautious and responsible development. While significant progress has been made in improving the safety and precision of gene therapy, ongoing research, rigorous clinical evaluation, and robust regulatory oversight are essential. A thorough understanding of these risks enables better decision-making and helps ensure that the benefits of gene therapy are realized without compromising patient safety.
Major risks associated with gene therapy
Immune system reactions
One of the most immediate and clinically significant risks associated with gene therapy is the activation of the patient’s immune system. Many gene therapy strategies rely on viral vectors such as adenoviruses, lentiviruses, or adeno-associated viruses to transport therapeutic genes into target cells. Although these vectors are genetically modified to eliminate their disease-causing capabilities, they still retain structural components that the immune system can recognize as foreign.
When these vectors are introduced into the body, the immune system may respond in several ways. The innate immune response, which serves as the body’s first line of defense, may rapidly detect viral particles and trigger inflammation. This can result in the release of pro-inflammatory cytokines, leading to localized or systemic inflammatory responses. In severe cases, this can escalate into a cytokine storm, a condition characterized by excessive immune activation that can cause organ failure and death.
In addition to innate immunity, the adaptive immune system may also be activated. This involves the production of antibodies and the activation of T cells that specifically target the viral vector or the genetically modified cells. As a result:
- the therapeutic cells may be destroyed before they can exert their beneficial effects,
- the effectiveness of the treatment may be significantly reduced, and
- repeat administration of the therapy may become impossible due to immune memory.
Repeat administration of the therapy is particularly important because many gene therapies require multiple doses to achieve sustained therapeutic outcomes. Once the immune system has been sensitized, subsequent treatments may trigger faster and stronger immune reactions, limiting long-term efficacy.
Insertional mutagenesis
Insertional mutagenesis is one of the most serious long-term risks of gene therapy, particularly for approaches that involve integrating vectors. This phenomenon occurs when the introduced genetic material inserts itself into the host genome at unintended locations. The human genome is highly organized, and the position of genes within it is critical for proper function. Random integration can disrupt this organization in several ways. For instance, if the inserted gene disrupts a tumor suppressor gene responsible for controlling cell growth it may lead to uncontrolled cell proliferation. Conversely, if the insertion occurs near an oncogene, it may activate that gene, triggering cancer development.
This risk is not merely theoretical. In early gene therapy trials for certain immunodeficiency disorders, some patients developed leukemia as a direct result of vector integration near oncogenes. These cases highlighted the potential for gene therapy to inadvertently introduce new, life-threatening conditions. Insertional mutagenesis can lead to broader genomic instability. Disruptions in DNA structure may affect neighboring genes or regulatory elements, leading to unpredictable changes in gene expression. Because these changes occur at the genetic level, their effects may persist indefinitely and may not be easily reversible.
Off-target effects
With the advent of advanced gene editing technologies, the precision of gene therapy has improved significantly. However, no system is entirely error-free. Off-target effects occur when genetic modifications are made at unintended locations in the genome. These unintended edits can arise due to similarities between the target DNA sequence and other regions of the genome. Even minor mismatches can sometimes be tolerated by gene-editing tools, leading to unintended modifications.
The consequences of off-target effects can be wide-ranging, and are as follows:
- Altered gene expression: Genes that were not meant to be modified may become overactive or suppressed.
- Disruption of essential pathways: Critical biological processes may be affected, leading to cellular dysfunction.
- Accumulation of mutations: Multiple off-target events may compound over time, increasing the risk of disease
One of the key challenges with off-target effects is that they may not produce immediate symptoms. Instead, their impact may become apparent only after prolonged periods, making them difficult to detect during short-term clinical trials. Because gene regulation networks are highly interconnected, even a single unintended modification can have cascading effects across multiple pathways. This complexity underscores the importance of improving targeting specificity and conducting comprehensive genomic analyses following treatment.
Toxicity of delivery systems
The delivery system used in gene therapy plays a crucial role in determining both efficacy and safety. While viral vectors are highly efficient at delivering genetic material, they can also introduce toxicity. Viral vectors may cause cellular stress by overwhelming the host cell’s machinery. The process of viral entry, gene expression, and replication (even in a modified form) can place significant metabolic demands on cells. This may lead to:
- cellular damage or apoptosis (programmed cell death),
- inflammatory responses in surrounding tissues, and
- activation of stress-related signaling pathways.
In some cases, the toxicity may extend beyond individual cells to affect entire tissues or organs. For example, high doses of viral vectors have been associated with liver toxicity in certain clinical settings. Non-viral delivery systems, such as lipid nanoparticles or polymer-based carriers, are often considered safer alternatives. However, they are not without risks. Depending on their composition, size, and dosage, these systems may:
- accumulate in non-target tissues,
- trigger immune responses, and
- interfere with normal cellular processes.
Because delivery systems are integral to gene therapy, optimizing their safety profile remains a critical area of ongoing research.
Overexpression or misregulation of genes
A central challenge in gene therapy is not just delivering the correct gene, but ensuring that it is expressed at appropriate levels. Gene expression in the body is tightly regulated through complex mechanisms involving promoters, enhancers, and feedback loops. When a therapeutic gene is introduced, these regulatory controls may not function as intended. Overexpression of the gene can lead to excessive production of the corresponding protein, which may be toxic to cells. For example:
- high levels of a therapeutic protein may overwhelm cellular processing systems,
- protein aggregates may form, leading to cellular dysfunction, and
- metabolic pathways may become imbalanced.
On the other hand, insufficient expression may render the therapy ineffective, requiring additional interventions. Another concern is the timing and location of gene expression. A gene that is beneficial in one tissue may be harmful in another. Similarly, expression at the wrong developmental stage or physiological condition may disrupt normal biological processes. Achieving precise control over gene expression both spatially and temporally remains one of the most difficult challenges in gene therapy.
Long-term unknown effects
Gene therapy is still a relatively young field, and long-term safety data are limited. Unlike conventional drugs, which are metabolized and cleared from the body, gene therapy can result in permanent or long-lasting genetic changes. This raises concerns about delayed or unforeseen effects that may only emerge years or even decades after treatment.
Potential long-term risks include:
- Late-onset cancers: Resulting from insertional mutagenesis or cumulative genetic damage,
- Chronic immune complications: Including persistent inflammation or autoimmune reactions, and
- Epigenetic alterations: Changes in gene regulation that do not involve alterations in DNA sequence but can still affect cellular function.
Because these effects may develop slowly, they are difficult to detect in early-phase clinical trials. Long-term follow-up studies are therefore essential but can be resource-intensive and challenging to implement. The evolving nature of gene therapy technologies means that current safety assessments may not fully capture future risks. Continuous monitoring and adaptive regulatory frameworks are necessary to address these uncertainties.
Risk of germline transmission
Gene therapy is generally classified into somatic and germline approaches. Somatic gene therapy targets non-reproductive cells and is not intended to be inherited. However, there is a small but significant risk that therapeutic genetic material could inadvertently affect germ cells (sperm or eggs). If this occurs, the introduced genetic changes may be passed on to future generations. This has several important implications:
- Unintended hereditary effects: Genetic modifications not originally designed for inheritance may persist in offspring,
- Propagation of errors: Any unintended mutations or off-target effects could be transmitted across generations, and
- Population-level consequences: Over time, such changes could influence the genetic makeup of populations.
This risk is particularly concerning because future generations cannot consent to these modifications. Moreover, the long-term effects of such inherited changes are largely unknown. Even in strictly controlled clinical settings, completely eliminating the possibility of germline involvement is challenging. As a result, stringent safeguards and monitoring protocols are necessary to minimize this risk.
Problems of gene therapy
Beyond its biological risks, gene therapy faces a range of practical, technical, economic, and clinical challenges that continue to limit its effectiveness, scalability, and integration into routine medical practice. Although it has shown significant promise particularly in treating rare genetic disorders its broader application remains constrained by persistent issues related to delivery efficiency, durability of expression, cost, and overall system complexity. Recognizing these limitations is critical for researchers, clinicians, policymakers, and patients alike, as it helps direct innovation and regulatory efforts toward making gene therapy more reliable and accessible.
These challenges are interconnected, spanning biological constraints, technological limitations, economic barriers, and regulatory demands, which together explain why gene therapy has not yet achieved widespread clinical adoption despite notable progress in recent years. Moving forward, meaningful advancement will depend on several key developments. Improved delivery systems are needed to enhance the precision and efficiency of gene transfer into target cells. At the same time, advances in genomic technologies must ensure safer and more controlled genetic modifications.
Addressing the high cost of therapy will require scalable and cost-efficient manufacturing processes, while regulatory frameworks must strike a careful balance between ensuring patient safety and enabling timely innovation. Ultimately, sustained interdisciplinary collaboration bringing together scientists, clinicians, policymakers, and industry stakeholders will be essential for transforming gene therapy from a largely experimental approach into a dependable and widely accessible form of medical treatment.
Short-lived effects of gene therapy
One of the most persistent and technically challenging limitations of gene therapy is the lack of long-term durability of therapeutic effects. Although gene therapy is often envisioned as a one-time treatment capable of producing lasting clinical benefits, the introduced genetic material may not remain active in a patient’s cells indefinitely. This limitation is particularly important when treatment targets tissues characterized by rapid cell turnover, where therapeutic genetic material can be progressively diluted or lost.
The persistence of therapeutic effects depends on several biological and technical factors. First, it matters whether the therapeutic DNA integrates into the host genome or remains episomal, meaning that it exists outside the chromosomes. Integrated genetic material can potentially be maintained as cells divide, although integration carries its own risks, including insertional mutagenesis and unintended effects on neighboring genes. In contrast, episomal DNA may gradually disappear as cells undergo repeated divisions.
Second, the lifespan and replication rate of target cells strongly influence treatment durability. In rapidly dividing tissues, such as the skin, blood-forming system, and intestinal lining, non-integrated genetic material may be diluted with each round of cell division. Even when gene transfer is initially successful, the number of cells expressing the therapeutic gene may decrease over time. In long-lived or non-dividing cells, however, therapeutic expression may persist for substantially longer periods.
A third consideration is the stability of gene expression. Even when therapeutic DNA remains present within cells, molecular mechanisms can reduce or completely silence its activity. Epigenetic modifications, changes in transcriptional regulation, immune-mediated elimination of modified cells, and gradual deterioration of vector-derived expression systems can all contribute to declining therapeutic activity.
Clinical consequences of short-lived gene expression
Short-lived gene expression can have significant clinical consequences. The most immediate concern is temporary therapeutic benefit. Patients may initially experience substantial improvement, only for symptoms to reappear as the therapeutic gene becomes less active or is lost from the relevant cells. This can be particularly problematic for chronic or progressive diseases that require continuous correction of an underlying genetic defect.
A decline in therapeutic activity may also necessitate repeated administration. Multiple treatments can increase the overall treatment burden and may expose patients to additional procedural risks, immune reactions, or vector-related complications. Furthermore, repeated treatment can be challenging when the patient’s immune system develops antibodies or cellular responses against the delivery vector, potentially reducing the effectiveness of subsequent doses.
Broader implications and current strategies for sustaining gene expression
The durability of gene expression directly influences the feasibility and cost-effectiveness of gene therapy. If therapeutic effects are short-lived, the treatment may function more like a temporary biological intervention than a definitive cure. This also complicates clinical trial design because researchers must evaluate not only initial efficacy but also the duration of therapeutic benefit over extended follow-up periods.
Researchers are therefore investigating several strategies to improve durability. These include the development of integrating vectors capable of maintaining therapeutic genes through cell division, gene-editing technologies designed to make permanent corrections to disease-causing mutations, and improved promoters and regulatory elements that support sustained gene expression. Advances in vector engineering and targeted delivery may further improve the ability to maintain therapeutic activity while minimizing associated risks.
Achieving safe, stable, and long-lasting gene expression remains a central objective in gene therapy research. Overcoming this limitation is essential for transforming many experimental therapies into durable treatments capable of providing sustained clinical benefit.
Inefficient Gene Delivery
Efficient delivery of therapeutic genes to the correct cells is arguably the central bottleneck in gene therapy. Even the most sophisticated gene-editing technologies, therapeutic genes, or vector designs cannot achieve their intended effects if they fail to reach the appropriate target cells in sufficient quantities. Gene delivery therefore represents a critical determinant of both the efficacy and safety of gene therapy. Challenges can arise at virtually every stage, from administration and tissue distribution to cellular uptake, intracellular trafficking, and sustained gene expression.
Barriers to effective gene delivery
Gene delivery is confronted by numerous biological, anatomical, and physical barriers. Anatomical barriers can significantly restrict access to specific tissues. For example, the blood-brain barrier (BBB) limits the passage of many therapeutic agents from the bloodstream into the central nervous system, making the treatment of neurological disorders particularly challenging. Similarly, dense extracellular matrices, tissue architecture, and limited vascular access can restrict vector penetration into certain organs or tumors.
Cellular uptake limitations present another major obstacle. Therapeutic genetic material must enter the appropriate cells and, depending on the therapeutic strategy, reach specific intracellular compartments to exert its intended effect. Not all cell types efficiently internalize genetic material or gene-delivery vectors. Even when vectors enter cells, intracellular degradation or inefficient transport can prevent the therapeutic payload from reaching its functional destination.
Immune clearance can further reduce delivery efficiency. The immune system may recognize viral or non-viral delivery systems as foreign and eliminate them before they reach the target tissue. Pre-existing immunity against certain viral vectors can also reduce their effectiveness and limit the feasibility of repeated administration.
Targeting challenges in gene delivery
Precise targeting is essential because therapeutic genes should ideally be delivered to diseased cells while minimizing exposure of healthy tissues. However, many delivery systems do not possess sufficient cell-type specificity. Consequently, vectors may distribute to unintended tissues, potentially reducing therapeutic efficacy while increasing the risk of adverse effects.
Biodistribution is another important consideration. Following administration, vectors may accumulate preferentially in certain organs rather than reaching the intended target. Tissue accessibility also varies considerably. For example, delivering therapeutic genes to some muscle tissues may be comparatively achievable, whereas selectively targeting specific neuronal populations within the brain remains considerably more complex.
Efficiency limitations of gene delivery
Even when a delivery system successfully reaches the target tissue, only a proportion of cells may receive and adequately express the therapeutic gene. This transduction efficiency can vary according to vector type, tissue characteristics, disease state, dose, and individual patient factors. Insufficient gene expression may result in incomplete therapeutic responses, while substantial variation between patients can make treatment outcomes difficult to predict.
Impact of gene delivery on clinical success
Inefficient gene delivery can substantially limit the clinical success of gene therapy. When only a small fraction of target cells are successfully modified, therapeutic benefits may be reduced or short-lived. Increasing the administered dose to compensate for poor delivery may improve tissue exposure but can simultaneously increase the risk of toxicity, immune reactions, and off-target effects.
Inefficient delivery can increase manufacturing complexity and treatment costs, particularly when highly specialized vectors or administration procedures are required. Overcoming these limitations will require advances in vector engineering, tissue-specific targeting, delivery technologies, and strategies for improving cellular uptake and sustained gene expression. Ultimately, achieving safe, precise, and efficient delivery remains one of the most important challenges in translating gene therapy from promising laboratory research into reliable clinical treatments.
Ongoing innovations to improve gene delivery
Improving the delivery of therapeutic genetic material remains one of the central challenges in gene therapy. The effectiveness of a gene therapy product depends not only on the therapeutic gene itself but also on whether it can be delivered safely, efficiently, and selectively to the intended cells. Researchers are therefore developing increasingly sophisticated delivery platforms designed to improve tissue targeting, reduce toxicity, and minimize unintended biological effects.
Current innovations include tissue-specific viral vectors, which are engineered to preferentially target particular organs or cell types. By improving tissue specificity, these vectors may increase therapeutic efficacy while reducing exposure to non-target tissues. Researchers are also investigating ligand-targeted nanoparticles, in which specific molecules bind to receptors expressed on target cells, facilitating selective uptake of the therapeutic cargo.
Physical delivery approaches such as electroporation can temporarily increase cell membrane permeability, allowing genetic material to enter cells more efficiently. Other emerging approaches include engineered capsids, exosome-based delivery systems, biodegradable polymers, and next-generation lipid nanoparticles.
Vector limitations of gene therapy
Vectors are biological or synthetic vehicles used to transport genetic material into target cells and are fundamental to the development of gene therapies. Despite major advances in vector engineering, both viral and non-viral vectors have inherent limitations that can constrain their safety, efficiency, scalability, and clinical utility.
Viral vectors are widely used because naturally evolved viruses are highly efficient at entering cells and delivering genetic material. However, their biological advantages are accompanied by several important limitations as follows:
- Limited cargo capacity: Many viral vectors can carry only relatively small amounts of genetic material. This restricts their use for large therapeutic genes, complex regulatory elements, or multiple genetic components.
- Immunogenicity: The immune system may recognize viral capsids or other vector components as foreign. This can trigger innate or adaptive immune responses, potentially reducing therapeutic effectiveness and, in severe cases, causing clinically significant adverse reactions.
- Insertional risks: Certain viral vectors can integrate therapeutic genetic material into the host genome. Although integration can provide long-lasting expression, it may also disrupt endogenous genes or regulatory regions and, in some circumstances, contribute to insertional mutagenesis and abnormal cell growth.
- Pre-existing immunity: Patients may already possess antibodies or immune cells against commonly used viral vectors because of previous natural exposure. Such immunity can reduce vector availability and limit treatment effectiveness.
- Manufacturing complexity: Producing viral vectors at the required purity, potency, consistency, and scale can be technically demanding and expensive. These manufacturing challenges can affect development timelines and treatment costs.
Non-viral vector limitations of gene therapy
Non-viral delivery systems, including lipid nanoparticles, polymer-based carriers, and other synthetic platforms, have attracted significant interest because they can offer greater flexibility in cargo design and may reduce some risks associated with viral vectors. However, they also present important challenges as follows:
- Lower delivery efficiency: Many non-viral systems are less efficient than viral vectors at transporting genetic material into specific target cells.
- Reduced biological stability: Genetic material and delivery particles may be degraded or cleared before reaching the intended tissue, limiting the amount of therapeutic material that reaches target cells.
- Limited tissue penetration: Some non-viral systems have difficulty crossing biological barriers, including cellular membranes, extracellular matrices, and physiological barriers such as the blood-brain barrier.
- Potential toxicity: Higher doses may be necessary to achieve an adequate therapeutic effect. Increased exposure to delivery materials can contribute to inflammation, organ toxicity, or other adverse effects.
There is currently no universal vector platform suitable for every gene therapy application. Vector selection must be tailored to the target tissue, type and size of genetic material, route of administration, required duration of expression, and patient characteristics. This need for individualized delivery strategies complicates development, increases manufacturing requirements, and can contribute to the overall cost of gene therapy.
Reversion to pathogenicity
Although viral vectors used in gene therapy are generally engineered to be replication-deficient and non-pathogenic, the theoretical possibility of regaining harmful characteristics remains an important biosafety consideration. Modern vector design incorporates multiple safeguards to minimize this risk, making clinically significant reversion highly unlikely. Nevertheless, because the consequences could be serious, regulatory authorities require extensive characterization and testing.
Mechanisms of potential reversion of viral vectors used in gene therapy
Theoretical mechanisms could include:
- Genetic mutation within vector sequences that alters their biological properties.
- Recombination between vector components and naturally occurring viruses or other genetic elements within the host.
- Unexpected residual replication functions resulting from incomplete separation or inadequate control of essential viral genes during vector production.
These mechanisms are carefully considered during vector design and manufacturing to prevent the restoration of replication competence or pathogenic properties.
Potential consequences of reversion to pathogenicity
If a replication-competent or otherwise harmful viral form were generated, potential consequences could include:
- Infection or tissue damage in the treated patient.
- Uncontrolled viral replication.
- Increased inflammatory or immune responses.
- In rare theoretical circumstances, transmission to other individuals.
Such events could have significant consequences for patient safety and could undermine public confidence in gene therapy technologies.
Risk management and regulatory oversight of viral vector reversion
The probability of clinically meaningful reversion is considered low when appropriately engineered vector systems and manufacturing controls are used. Nevertheless, the potential severity of such an event requires rigorous safeguards.
These include extensive preclinical evaluation, replication-competence testing, multiple genetic modifications that prevent viral replication, validated manufacturing processes, quality-control testing, and long-term clinical monitoring.
Regulatory agencies therefore impose stringent requirements on vector design, production, characterization, and clinical evaluation. Although these requirements increase development complexity and cost, they are essential for demonstrating that gene therapy products have an acceptable benefit–risk profile and can be administered safely to patients.
Targeting specificity issues of gene therapy
Precise targeting is a fundamental requirement for the efficacy, safety, and clinical success of gene therapy. The objective is to deliver a therapeutic gene, gene-editing system, or genetic material specifically to the cells and tissues where it is needed, while minimizing exposure to healthy or unintended cells. However, achieving this level of specificity remains a significant challenge. Gene therapy vectors, including viral and non-viral delivery systems, can exhibit complex distribution patterns within the body, making it difficult to restrict their activity exclusively to the intended target.
Ideally, a therapeutic vector should recognize and enter only the desired cell type and subsequently express its genetic payload at an appropriate level. In practice, several factors can interfere with this process. Vectors may distribute broadly through the bloodstream and accumulate in organs that were not intended to receive treatment. In addition, non-target cells may take up the vector or therapeutic gene, resulting in unintended gene expression. Although tissue-specific promoters and regulatory elements can help restrict gene activity, these mechanisms are not always completely selective or reliable under physiological and disease conditions.
Consequences of poor targeting
Inadequate targeting can have important clinical consequences. First, it may lead to a reduced therapeutic benefit, because an insufficient number of target cells receive or express the therapeutic gene. This can result in incomplete correction of the underlying genetic defect or inadequate production of the desired therapeutic protein.
Second, poor targeting may cause off-target effects, in which genetic material is expressed in cells where it is unnecessary or potentially harmful. Unintended gene expression can alter cellular signaling, metabolism, proliferation, or other essential biological processes. In some circumstances, exposure of non-target tissues to therapeutic genes or gene-editing components may contribute to significant toxicity.
For example, a therapeutic gene designed primarily for liver cells could potentially reach cardiac, immune, or other tissues. If the gene is expressed at inappropriate levels in these cells, it could interfere with normal cellular function and produce adverse effects. Therefore, controlling both the distribution of the vector and the expression of its genetic payload is essential.
Biological complexity of targeting
The biological complexity of the human body further complicates precise targeting. Cells within the same tissue may differ considerably in their surface receptors, metabolic characteristics, gene-expression profiles, and susceptibility to vector uptake. Consequently, a delivery system that performs effectively in one cell population may behave differently in another.
Disease conditions can introduce additional challenges. Pathological changes may alter tissue architecture, blood flow, receptor expression, and cellular composition, potentially affecting vector distribution and uptake. Furthermore, circulatory dynamics can cause vectors to accumulate preferentially in certain organs, increasing exposure of tissues that are not the intended therapeutic targets.
Strategies to improve specificity issues in gene therapy
Researchers are developing several approaches to improve targeting specificity. These include engineering vectors with tissue- or cell-specific tropism, allowing them to preferentially interact with particular cell populations. The use of cell-specific promoters and regulatory elements can further restrict therapeutic gene expression to the desired tissues.
Other strategies include targeted delivery systems, ligand-receptor interactions, antibody-based targeting, nanoparticles, and advanced gene-editing platforms designed to recognize specific molecular sequences. Combining multiple targeting mechanisms may provide greater control than relying on a single approach.
Improving targeting specificity is critical for maximizing therapeutic efficacy while minimizing unintended biological effects. Continued advances in vector engineering, molecular targeting, and delivery technologies will be essential for making gene therapies safer, more precise, and more clinically effective.
High cost and limited accessibility of gene therapy
Gene therapy is currently among the most expensive forms of advanced medical treatment, creating significant barriers to access for patients, healthcare providers, and health systems. Unlike conventional medicines, many gene therapies involve highly specialized technologies designed to modify or replace defective genes, often requiring complex development, manufacturing, administration, and long-term monitoring. These factors contribute to exceptionally high treatment costs, with some therapies priced at hundreds of thousands or even millions of dollars per patient.
Several factors contribute to the high cost of gene therapy. First, research and development (R&D) require substantial investment in molecular biology, vector engineering, preclinical testing, and clinical trials. Gene therapies must also undergo extensive safety and efficacy assessments because their effects may persist for many years. Second, some treatments require personalized or small-batch manufacturing, particularly when a patient’s own cells are collected, genetically modified, and returned to the patient. This individualized production process is considerably more expensive than mass-producing conventional pharmaceutical drugs.
Costs arise from stringent regulatory requirements and the need for specialized clinical infrastructure. Gene therapy may require highly trained medical personnel, specialized laboratories, advanced delivery systems, and sophisticated monitoring procedures. These requirements can make treatment difficult to provide outside major medical centers.
Impact of cost on patients
The high price of gene therapy can substantially limit patient access. In low- and middle-income countries, the financial burden may make advanced gene therapies largely unavailable. In high-income countries, access may still depend on insurance coverage, government reimbursement, or special funding programs. Insurance providers and healthcare systems may face difficult decisions when determining whether the substantial upfront cost of a therapy is justified by its potential long-term benefits. High costs can therefore lead to delays in treatment, particularly for patients with rapidly progressing diseases. This creates concerns about whether patients who could benefit from potentially transformative therapies can receive them at the appropriate time.
Ethical and societal implications of gene therapy
The cost of gene therapy raises important ethical questions regarding healthcare equity and resource allocation. If only patients with comprehensive insurance coverage or access to substantial healthcare resources can receive these treatments, socioeconomic disparities may increase. Healthcare systems must also determine how limited resources should be allocated between expensive gene therapies and other essential medical services.
At a global level, unequal access could further widen the healthcare gap between high-income and low-income populations. Addressing these disparities may require international collaboration, technology transfer, public investment, and pricing strategies that make treatments more affordable.
Potential approaches to reducing costs include scaling up manufacturing, developing standardized production platforms, improving manufacturing efficiency, and implementing innovative payment models. Outcome-based pricing and installment-based reimbursement models may help healthcare systems manage the substantial upfront expense of some therapies.
Complex manufacturing and regulation of gene therapy
Gene therapy products involve highly sophisticated manufacturing and regulatory processes that are technically demanding and closely controlled. Production commonly requires advanced biotechnology facilities, specialized equipment, trained personnel, and strict quality-control systems. Biological materials must be handled with considerable precision because relatively small variations in manufacturing conditions can affect the safety, potency, purity, and consistency of the final product.
Unlike many conventional pharmaceuticals, gene therapies can be difficult to manufacture at large scale. Some treatments involve patient-specific materials or relatively small production batches, while others depend on complex biological vectors. In addition, supply chains may require specialized storage, transportation, and handling conditions to maintain product stability.
Regulatory hurdles of gene therapy
Regulatory agencies require extensive evidence demonstrating that gene therapy products are sufficiently safe, effective, and consistently manufactured. Development may involve preclinical studies, multi-phase clinical trials, manufacturing validation, and long-term patient follow-up. These requirements are particularly important because some gene therapies can produce long-lasting or potentially irreversible biological effects. Although rigorous regulation is essential for protecting patients, it can also increase development timelines and costs. Smaller biotechnology companies may find these requirements especially challenging because they often have fewer financial and technical resources than large pharmaceutical organizations.
Impact of regulation on gene therapy innovation
The complexity of manufacturing and regulation can influence the pace of innovation in gene therapy. High development costs and technical barriers may limit the number of organizations capable of bringing new therapies to market. Manufacturing difficulties can also delay clinical development and commercial availability. Advances in automation, manufacturing platforms, process standardization, regulatory science, and quality-control technologies may gradually reduce these barriers. Improving production efficiency while maintaining rigorous safety standards will be essential for making gene therapy more accessible, sustainable, and widely available.
Difficulty of gene therapy in treating complex diseases
Gene therapy has demonstrated significant success in treating monogenic disorders, which are diseases caused primarily by mutations in a single gene. However, many of the most common and challenging diseases are complex disorders involving multiple genes, environmental factors, and interconnected biological pathways. This complexity makes them considerably more difficult to treat through gene-based approaches.
Nature of complex diseases
Diseases such as cancer, diabetes, cardiovascular disease, Alzheimer’s disease, and autoimmune disorders rarely result from a single genetic defect. Instead, they develop through interactions among multiple genes and are influenced by factors such as diet, lifestyle, aging, infections, and environmental exposures. These factors can affect gene expression and disease progression in different ways. Complex diseases may also involve numerous biological pathways operating simultaneously. A genetic change that appears important in one pathway may influence several other cellular processes. Altering a single gene may have limited therapeutic value or may produce unintended biological effects.
Challenges for gene therapy in treating complex diseases
One of the major challenges is identifying appropriate genetic targets. Researchers must determine which genes or molecular pathways are directly responsible for disease progression and which modifications are likely to produce a beneficial outcome. In complex diseases, there may be dozens or even hundreds of relevant genetic and molecular factors. Modifying one gene may not be sufficient to produce a meaningful clinical effect. Other genes may compensate for the change, or the disease may continue through alternative biological pathways. Genetic interactions can therefore make treatment responses difficult to predict.
Need for multi-target approaches in treating complex diseases
Effective gene therapy for complex diseases may require simultaneous modification of multiple genes or pathways. Researchers are investigating approaches that can regulate several molecular targets while minimizing unwanted effects. In many cases, gene therapy may also need to be combined with conventional treatments such as chemotherapy, immunotherapy, surgery, or pharmacological therapies. Personalized medicine may become particularly important. Because patients can have different genetic profiles and disease mechanisms, treatment strategies may need to be tailored to individual biological characteristics rather than applying a single therapy to all patients.
Unpredictable outcomes of gene therapy in treating complex diseases
The biological complexity of these diseases also increases uncertainty about treatment outcomes. Patients may respond differently because of variations in their genetics, immune systems, disease stage, and environmental factors. Some may experience substantial benefits, while others may show limited or no response. Long-term effects can also be difficult to predict, particularly when genetic modifications produce changes across multiple cellular pathways. These uncertainties complicate the design, interpretation, and long-term monitoring of clinical trials. Treating complex diseases remains a major challenge for gene therapy because their multifactorial nature, genetic interactions, patient variability, and unpredictable biological responses require more sophisticated and precisely targeted therapeutic strategies.
Ethical issues of gene therapy
Gene therapy represents a transformative advancement in modern medicine, offering unprecedented opportunities to treat and, in some cases, potentially cure genetic and acquired diseases. By enabling targeted modification or replacement of genetic material, gene therapy extends therapeutic possibilities beyond conventional medical interventions. However, the ability to alter human biological systems also raises complex ethical questions that extend beyond the laboratory and clinical setting. These concerns intersect with philosophy, law, religion, social justice, and public policy, influencing regulatory decisions, public trust, and the responsible development of emerging genetic technologies.
At the center of the ethical debate are several interconnected issues, including informed consent and patient autonomy, safety and uncertainty, equity and access, privacy, and long-term societal consequences. Patients must receive clear and comprehensive information about potential benefits, risks, uncertainties, and alternative treatments before consenting to gene therapy. Particular concern arises with germline gene editing, because genetic changes may be inherited by future generations who cannot provide consent. The possibility of unintended genetic alterations, adverse effects, or unforeseen long-term consequences further emphasizes the need for rigorous scientific evaluation and monitoring.
Equitable access is another major ethical consideration. Many gene therapies are highly complex and expensive, potentially creating disparities between individuals or populations who can afford advanced treatments and those who cannot. Ethical implementation therefore requires policies that promote fairness and prevent technological progress from widening existing health inequalities.
Key priorities for the ethical and effective development of gene therapy include:
- Enhancing safety and efficacy through rigorous preclinical research, clinical trials, and long-term monitoring.
- Improving delivery systems to increase precision, reliability, and therapeutic effectiveness while minimizing unintended effects.
- Strengthening ethical and regulatory frameworks to ensure responsible research and clinical application.
- Promoting equitable access so that the benefits of gene therapy are not restricted to privileged populations.
- Protecting genetic privacy and preventing discrimination or misuse of genetic information.
Responsible gene therapy requires a careful balance between scientific innovation and ethical accountability. Transparent governance, informed consent, public engagement, and multidisciplinary oversight are essential to maximize therapeutic benefits while minimizing risks to individuals and society.
Germline versus somatic gene therapy
One of the most important ethical distinctions in gene therapy concerns whether genetic changes affect only the treated person or can be inherited by future generations. Somatic gene therapy modifies genes in non-reproductive cells, such as blood, liver, or muscle cells. These changes remain within the treated individual and are not transmitted to their children. For this reason, somatic gene therapy is generally viewed as ethically more acceptable because it is consistent with the conventional medical objective of treating disease without permanently altering human inheritance.
Germline gene therapy, by contrast, involves modifying sperm, eggs, or embryos. Because these changes can be inherited, their effects may extend across generations. The central ethical concern is consent: future individuals affected by a germline modification cannot consent to a decision made before their existence. This raises questions about intergenerational justice and whether present generations have the moral authority to make potentially irreversible genetic decisions for future people.
Another concern is uncertainty. Genes interact with one another and with environmental factors in complex ways, so an alteration intended to prevent one disorder could produce unintended consequences. Germline editing also raises concerns about eugenics, particularly the possibility of selecting or promoting preferred traits and discriminating against people who do not possess them. Given these risks, many jurisdictions restrict or prohibit clinical germline modification. Ethical governance requires strong independent oversight and rigorous safety evidence, long-term monitoring, transparent public discussion, and careful consideration of whether potential benefits justify heritable genetic change.
Consent, autonomy, and patient decision-making in gene therapy
Informed consent is a fundamental principle of medical ethics, but gene therapy creates distinctive challenges for meaningful patient autonomy. Genetic interventions can involve highly technical concepts, including off-target effects, immune reactions, insertional mutagenesis, vector-related complications, and uncertain long-term outcomes. Patients may therefore struggle to understand the probability and severity of possible risks. Clinicians have an ethical responsibility to communicate complex information accurately and without exaggerating benefits or risks.
These challenges intensify when gene therapy is experimental. Patients in clinical trials may be motivated by serious illness, few alternatives, or hope for a breakthrough. Such circumstances can create therapeutic misconception, in which participants mistakenly believe that an experimental intervention is primarily designed to provide individualized treatment rather than generate scientific knowledge. Consent must explain the study’s purpose, experimental status, risks, benefits, alternatives, and the right to withdraw.
Pediatric gene therapy presents additional challenges. Children often cannot provide legally or ethically sufficient consent, so parents or guardians generally make decisions on their behalf. Treatment may have lifelong consequences affecting the child’s future autonomy. Decisions should reflect the child’s best interests while considering their emerging decision-making capacity and autonomy over time.
Ethically robust consent should be an ongoing process rather than a single signature. It should include understandable explanations, opportunities for questions, independent ethical oversight, protection from coercion, and reassessment when important new evidence emerges. Respect for autonomy also requires privacy and careful handling of genetic information, which may have implications for relatives as well as the patient.
Equity, access, and genetic enhancement in gene therapy
Equity is a major ethical challenge because gene therapies can be extraordinarily expensive and often require specialized healthcare infrastructure. If access depends primarily on wealth, insurance coverage, or geographic location, these treatments could widen existing health inequalities. Patients in low- and middle-income countries may face severe barriers, creating a global “genetic divide.” Ethical policy must consider both scientific effectiveness and who can realistically benefit.
Healthcare systems must make difficult resource-allocation decisions. Funding an expensive gene therapy for a small number of patients may compete with vaccination, primary care, or treatments benefiting larger populations. Fair reimbursement, transparent priority-setting, international cooperation, technology transfer, and lower manufacturing costs can balance innovation with distributive justice.
A related concern is the distinction between therapy and genetic enhancement. Therapeutic gene therapy aims to prevent, treat, or correct disease, whereas enhancement seeks to increase traits beyond typical human functioning. Possible enhancements, such as increased physical performance or cognitive abilities, raise concerns about inequality, coercion, discrimination, and changing definitions of normality. If enhancements are mainly available to wealthy groups, genetic advantages could reinforce social stratification.
The boundary between therapy and enhancement is often unclear. Treating conditions affecting cognition, height, or physical performance may be therapeutic in one context and enhancement in another. Ethical governance should emphasize medical necessity, proportionality, safety, fairness, and broad societal deliberation, protecting vulnerable people and human diversity. Gene therapy should advance scientific innovation while ensuring that its benefits are not reserved for privileged populations or used to undermine individual dignity and social equality.
Safety versus innovation in gene therapy
The development of gene therapy requires a careful balance between two competing ethical priorities: protecting patient safety and promoting scientific innovation. Gene therapy has the potential to treat or even cure serious genetic and acquired diseases, but it can also involve substantial risks, including immune reactions, unintended genetic changes, toxicity, and unknown long-term effects. Premature or inadequately regulated applications could cause significant harm to patients. Rigorous preclinical research, carefully designed clinical trials, regulatory oversight, informed consent, and long-term follow-up are therefore essential components of responsible gene therapy development.
At the same time, excessively restrictive regulations may slow scientific progress and delay access to potentially life-saving treatments. This issue is particularly important for patients with severe, progressive, or terminal diseases for which conventional treatments are ineffective or unavailable. For such individuals, waiting for years of additional research may not be a realistic option. This creates difficult ethical questions: What level of risk is acceptable in experimental treatment? Should patients with no effective alternatives be permitted to access therapies that have not completed all stages of clinical testing? How should unexpected adverse events be reported and managed?
One possible approach is compassionate use or expanded access, which allows eligible patients to receive investigational therapies outside conventional clinical trials. Although this can provide an important option for patients with serious conditions, it must be accompanied by appropriate safeguards. Responsible gene therapy requires transparent risk-benefit assessments, adaptive regulation, continuous safety monitoring, comprehensive data sharing, and meaningful patient and public engagement. Ethical standards must evolve alongside scientific knowledge while maintaining patient welfare as the central priority.
Ethical and safety considerations in the use of viral vectors
The use of viral vectors as delivery systems introduces additional ethical and safety considerations in gene therapy. Viruses are naturally efficient at entering cells and transferring genetic material, making them valuable tools for delivering therapeutic genes to specific tissues. Scientists modify these viruses to reduce their ability to cause disease or replicate, allowing them to function as therapeutic delivery vehicles. Nevertheless, the use of viral vectors can raise concerns about patient safety, biological uncertainty, environmental effects, and public perception.
Potential risks include unintended immune responses, inflammation, toxicity, inappropriate distribution of the vector, and, in some approaches, unintended changes to the genome. Although modern vector systems are designed with multiple safety mechanisms, unforeseen biological effects may still occur. There are also questions concerning vector shedding and environmental exposure, particularly if modified viral particles can be released from treated individuals. These concerns require appropriate containment procedures, monitoring, and risk assessment.
Public perception represents another important ethical dimension. Because viruses are commonly associated with infectious diseases, patients and members of the public may be concerned about treatments involving modified viral particles. Misunderstanding or inadequate communication can contribute to fear and mistrust, even when the scientific evidence indicates that a particular vector has been carefully engineered and tested. Therefore, transparency and public education are essential for maintaining confidence in gene therapy.
Responsible use of viral vectors requires clear communication about their design, limitations, and safety controls. It also requires robust preclinical testing, carefully monitored clinical trials, ethical review, and appropriate regulatory supervision. Researchers should communicate potential risks honestly rather than minimizing uncertainty. Building public trust depends on demonstrating that scientific innovation is accompanied by accountability, transparency, and effective safeguards. In this way, viral-vector-based therapies can advance while maintaining appropriate protection for patients, healthcare professionals, and the wider environment.
Long-term societal impact of gene therapy
Gene therapy has the potential to transform healthcare, but its effects may extend far beyond individual patients. As these technologies become more effective and accessible, they could produce significant long-term societal, economic, and ethical consequences. One major concern involves the possibility of altering population genetics, particularly if germline gene editing becomes widely used. Unlike somatic gene therapy, which affects only the treated individual, germline modifications can potentially be transmitted to future generations. This raises questions about human genetic diversity, intergenerational consent, and the potential consequences of making permanent genetic changes.
Another important concern is genetic discrimination. As genetic information becomes increasingly relevant to medical treatment, individuals could potentially be treated differently because of their genetic characteristics. Such discrimination could affect employment, insurance, education, or social opportunities. Strong privacy protections and appropriate legal safeguards are therefore necessary to prevent genetic information from being misused.
The possibility of “designer babies” creates an additional ethical challenge. Using gene-editing technologies to prevent serious inherited diseases may receive broad support, but selecting or modifying non-medical characteristics such as physical appearance, intelligence, or athletic ability is considerably more controversial. If such technologies become available primarily to wealthy individuals, they could also increase existing social and economic inequalities. Access to advanced gene therapies is therefore not only a medical issue but also a question of justice and equitable healthcare.
Addressing these challenges requires proactive governance, ethical guidelines, effective legislation, international cooperation, and continued public engagement. Policymakers, scientists, healthcare professionals, patients, and communities should participate in decisions about acceptable applications and limits. Because gene therapy is developing rapidly, regulations must be sufficiently flexible to accommodate scientific progress while preventing irresponsible applications. The long-term success of gene therapy will depend not only on its scientific effectiveness but also on society’s ability to ensure that its benefits are distributed fairly and that its risks are responsibly managed.
References
Sayed, N., Allawadhi, P., Khurana, A., Singh, V., Navik, U., Pasumarthi, S. K., Khurana, I., Banothu, A. K., Weiskirchen, R., & Bharani, K. K. (2022). Gene therapy: Comprehensive overview and therapeutic applications. Life Sciences, 294, 120375.
Rashid, R. A., & Ankathil, R. (2020). Gene therapy: An updated overview on the promising success stories. Malaysian Journal of Pathology, 42(2), 171–185.
Alberts B, Bray D, Johnson A, Lewis J, Raff M, Roberts Kand Walter P (1998). Essential Cell Biology: An Introduction to the Molecular Biology of the Cell. Third edition. Garland Publishing Inc., New York.
Dale J (2003). Molecular genetics of bacteria. Jeremy W. Dale and Simon Park (4th eds.). John Wiley & Sons Ltd, West Sussex, UK.
Edelstein, M. L., Abedi, M. R., Wixon, J., and Edelstein, R. M. (2004). Gene therapy clinical trials worldwide 1989-2004—an overview. J Gene Med, 6: 597-602.
Ferrua, F.; Brigida, I.; Aiuti, A. (2010). Update on gene therapy for adenosine deaminase-deficient severe combined immunodeficiency. Current Opinion in Allergy and Clinical Immunology. 10 (6): 551–556.
Gardlík R, Pálffy R, Hodosy J, Lukács J, Turna J, Celec P; Pálffy; Hodosy; Lukács; Turna; Celec (2005). Vectors and delivery systems in gene therapy. Med Sci Monit. 11 (4): RA110–21.
Horn PA, Morris JC, Neff T, Kiem HP; Morris; Neff; Kiem (2004). Stem cell gene transfer—efficacy and safety in large animal studies. Mol. Ther. 10 (3): 417–31.
S Li and L Huang (2000). Nonviral gene therapy: promises and challenges. Gene Therapy, 7:31-34. www.nature.com/gt
Salmons B, Günzburg WH; Günzburg (1993). Targeting of retroviral vectors for gene therapy. Hum Gene Ther. 4 (2): 129–41.
Sambrook, J., Russell, D.W. (2001). Molecular Cloning: a Laboratory Manual, 3rd edn. Cold Spring Harbor Laboratory Press, New York.
Sheridan C (2011). Gene therapy finds its niche. Nature Biotechnology. 29 (2): 121–128.
Vannucci, L; Lai, M; Chiuppesi, F; Ceccherini-Nelli, L; Pistello, M (2013). Viral vectors: A look back and ahead on gene transfer technology. The new microbiologica. 36 (1): 1–22.
Discover more from Microbiology Class
Subscribe to get the latest posts sent to your email.