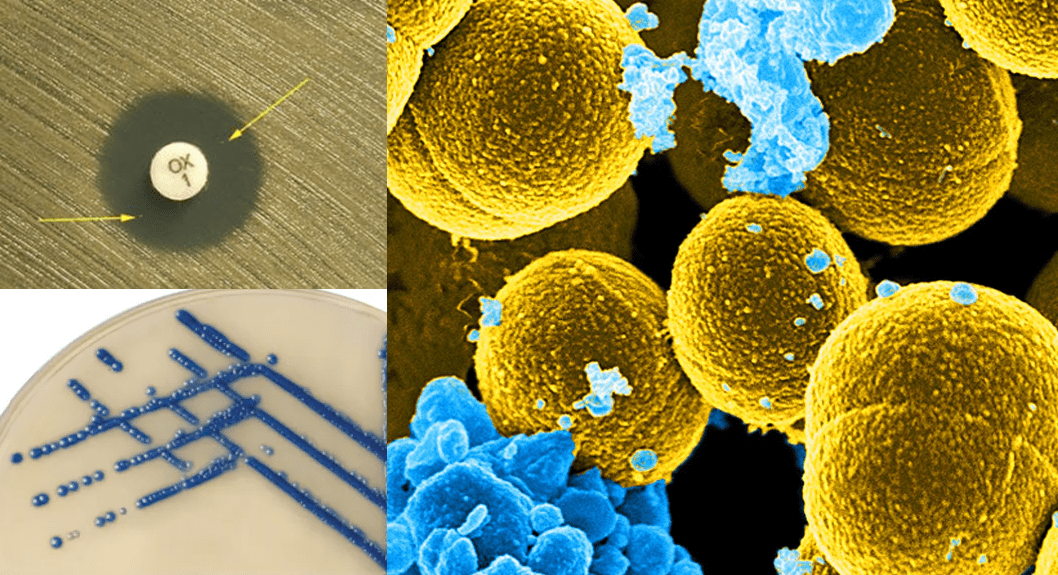
Antimicrobial resistance (AMR) or antibiotic resistance occurs when microorganisms acquire the capacity to survive exposure to antimicrobial agents (or antibiotics) that would previously have inhibited their growth or eliminated them. Although resistance can arise naturally through genetic variation and microbial evolution, its acceleration is strongly influenced by inappropriate antimicrobial use, inadequate infection prevention, poor adherence to treatment, and the extensive movement of resistant organisms between humans, animals, healthcare facilities, and the environment. The consequences of AMR are no longer confined to microbiology or clinical medicine; they increasingly affect the organization, affordability, and sustainability of healthcare systems.
AMR has emerged as a defining challenge of modern health systems, threatening the effectiveness of medicines that underpin routine clinical care. The increase in the global prevalence of AMR through inappropriate antimicrobial use, inadequate infection prevention, environmental contamination, and limited access to appropriate treatment has transformed AMR into a global public health concern. Its consequences extend beyond individual patients, affecting healthcare systems, national economies, and social development.
The public health implications of AMR are particularly profound because effective antimicrobials support procedures that are often taken for granted, including surgery, cancer chemotherapy, organ transplantation, and intensive care. When infections become resistant to available treatments, patients may experience prolonged illness, treatment failure, complications, or death. Resistant infections can also spread within hospitals and communities, increasing the burden on already constrained health services. The challenge is further intensified by the uneven distribution of antimicrobial resistance, with populations in settings characterized by inadequate sanitation, limited diagnostic capacity, and restricted access to healthcare often facing disproportionate risks.
The economic consequences of AMR are closely connected to these health impacts. Resistant infections can increase expenditure through longer hospital stays, additional diagnostic investigations, more expensive medicines, and extended clinical care. At the household level, illness may result in lost wages, reduced productivity, transportation expenses, and long-term financial hardship. At a broader level, widespread resistance can diminish workforce participation and impose substantial pressures on public healthcare budgets. Industries dependent on healthy populations and reliable medical services may also experience indirect economic disruption.
Addressing AMR therefore requires more than the development of new antimicrobial drugs. Effective action involves antimicrobial stewardship, stronger surveillance systems, improved infection prevention and control, rapid and accurate diagnostics, vaccination, sanitation, and responsible antimicrobial use across human, animal, and environmental sectors.
The growing threat of AMR to health and economic stability
Antimicrobial agents, particularly antibiotics, have transformed modern medicine by providing effective means of preventing and treating bacterial infections that were once major causes of illness and death. Their widespread availability has contributed substantially to increased life expectancy, safer surgical procedures, successful cancer treatment, organ transplantation, and improved management of infectious diseases. However, this therapeutic advantage is increasingly being undermined by the emergence and dissemination of antimicrobial-resistant microorganisms. When pathogens acquire the capacity to survive exposure to medicines that would ordinarily inhibit or eliminate them, previously manageable infections can become difficult, prolonged, and sometimes impossible to treat. The expansion of resistance across community and healthcare settings therefore represents a growing threat to the sustainability of contemporary healthcare.
The consequences of antibiotic resistance extend well beyond the failure of individual treatments. Inappropriate prescribing, unnecessary consumption, incomplete adherence, and excessive antimicrobial exposure exert selective pressure on microbial populations, favouring organisms that possess or acquire resistance determinants. Over time, these processes contribute to the accumulation and circulation of resistance genes within bacterial communities and across environmental, animal, and human reservoirs. The resulting resistance landscape can diminish the effectiveness of established therapies and narrow the range of reliable treatment options available to clinicians. Antibiotic resistance is not simply a microbiological phenomenon; it is a systemic challenge with implications for population health, healthcare capacity, and economic resilience.
From a public health perspective, resistant infections are associated with treatment delays, therapeutic failure, prolonged disease, preventable complications, and increased mortality. Patients affected by resistant organisms may require longer periods of hospitalization and additional laboratory investigations, while clinicians may need to employ broader-spectrum or reserve antibiotics. Such medicines can be substantially more expensive, may carry greater toxicity, and can further intensify selective pressure when used indiscriminately. Prolonged hospitalization also increases the opportunity for resistant organisms to spread within healthcare facilities, creating an additional cycle of transmission, treatment complexity, and resource consumption.
The economic repercussions are equally consequential. At the individual level, resistant infections can generate substantial expenses through extended hospital stays, additional diagnostic procedures, costly medicines, and prolonged follow-up care. Families may also experience indirect financial losses when illness prevents patients or caregivers from working. At the institutional level, increased occupancy, intensive clinical management, and infection-control requirements place additional demands on healthcare resources. At the national level, these pressures can translate into escalating healthcare expenditure, reduced workforce productivity, absenteeism, and losses associated with premature mortality. For health systems operating under constrained budgets, the cumulative burden may be particularly severe, potentially widening inequalities in access to effective treatment.
Containing AMR therefore requires a sustained commitment to antimicrobial stewardship and responsible antibiotic use in hospitals and communities. Optimizing prescribing practices, strengthening infection prevention and control, expanding diagnostic capacity, improving surveillance, and promoting public awareness are essential to slowing the erosion of antimicrobial effectiveness. Preserving existing antibiotics is not merely a clinical responsibility; it is an investment in public health security and economic stability. Without decisive action, the progressive loss of effective antimicrobial therapies could intensify human suffering, constrain medical progress, and impose an increasingly formidable economic burden on societies worldwide.
Clinical, therapeutic, and socioeconomic consequences of AMR
The growing prevalence of resistant microorganisms can transform otherwise treatable infections into complex clinical conditions requiring prolonged management and alternative therapeutic strategies. As first-line medicines become less reliable, patients may experience delayed recovery, treatment failure, recurrent infections, or severe complications. Healthcare facilities may consequently face greater demand for beds, diagnostic services, isolation facilities, and specialized clinical care. Beyond hospitals, AMR can reduce workforce productivity, increase household expenditure, and impose substantial pressure on national health budgets.
The significance of AMR therefore lies not only in the microorganisms themselves but also in its capacity to disrupt the interconnected systems that protect human health and economic productivity. Its major consequences include increased hospitalization, ineffective antibiotic therapy, escalating treatment costs, morbidity and mortality, economic hardship, greater disease severity, diminished antimicrobial efficacy, and the emergence and dissemination of novel drug-resistant microbes.
Increased hospitalization
AMR can substantially increase the likelihood and duration of hospitalization because infections caused by resistant organisms are often more difficult to control with conventional treatment. When first-line antibiotics fail, clinicians may need additional time to identify an effective therapeutic option through culture, antimicrobial susceptibility testing, or molecular diagnostics. During this period, patients may require continued inpatient monitoring rather than being discharged after routine treatment. Resistant infections can occupy hospital beds for longer periods and place additional demands on clinical personnel and diagnostic infrastructure.
Prolonged hospitalization also creates conditions that may facilitate further transmission of resistant microorganisms. Patients who remain in healthcare facilities for extended periods are repeatedly exposed to healthcare environments, invasive procedures, and other patients, increasing opportunities for cross-transmission. The problem can be particularly challenging in intensive care units, surgical wards, and other settings where vulnerable patients require frequent interventions.
The hospitalization burden extends beyond the infected individual. Increased bed occupancy can reduce the capacity of healthcare facilities to accommodate other patients, contributing to delays in elective procedures and other essential services. Hospitals may also require enhanced infection-prevention measures, including screening, isolation, environmental decontamination, and additional protective equipment. Thus, AMR can convert a relatively straightforward infection into a prolonged episode of care, consuming resources that could otherwise support broader healthcare delivery.
Ineffective antibiotic therapy
One of the most immediate consequences of AMR is the diminished ability of antibiotics to produce the desired therapeutic response. Antibiotics are selected on the assumption that the causative bacterial pathogen will be susceptible to the prescribed agent. However, when resistance mechanisms are present, the microorganism may withstand the drug through processes such as enzymatic degradation, alteration of antimicrobial targets, reduced membrane permeability, or active efflux of the drug from the bacterial cell. The result is therapeutic inadequacy despite appropriate administration of the medicine.
Treatment failure can prolong the infectious process and allow the pathogen to continue multiplying or disseminating within the host. Clinicians may subsequently need to modify the treatment regimen, use alternative antibiotics, or administer combinations of agents. Such adjustments are not always straightforward because resistance patterns can differ between microorganisms, geographical locations, healthcare facilities, and individual patients.
Ineffective therapy is particularly concerning when infections progress rapidly or occur in individuals with limited physiological reserves. Delayed microbiological control may permit complications such as bloodstream infection, organ dysfunction, or extensive tissue damage to develop. Furthermore, repeated exposure to unsuccessful antibiotics can increase selective pressure within microbial populations, potentially favouring additional resistance.
The erosion of antibiotic effectiveness therefore undermines one of the fundamental principles of infectious-disease management: the expectation that a diagnosed bacterial infection can be reliably controlled with an available medicine. As resistance expands, therapeutic decisions become more complex, uncertain, and resource-intensive.
Increased cost of treatment
AMR increases the financial burden associated with managing infectious diseases by transforming relatively routine treatment into a more resource-intensive process. When first-line antibiotics are ineffective, patients may require second-line or reserve medicines that are more expensive to obtain and administer. Additional laboratory investigations may also be necessary to determine the susceptibility profile of the pathogen and identify an effective therapeutic option. These expenditures accumulate alongside the costs generated by prolonged clinical monitoring and hospitalization.
The financial consequences are particularly pronounced when resistant infections require intensive or specialized care. Longer hospital stays increase expenditure on accommodation, nursing, laboratory services, medications, medical supplies, and supportive treatment. Infection-control interventions can add further costs, particularly when hospitals need isolation facilities, enhanced environmental cleaning, surveillance, or additional personal protective equipment.
At the individual level, treatment expenses may extend beyond direct medical charges. Patients and caregivers can experience transportation costs, loss of income, reduced working hours, and additional expenditure associated with prolonged recovery. These indirect costs can be substantial for households with limited financial resources.
At the healthcare-system level, AMR can divert funds from preventive programmes, primary healthcare, infrastructure development, and other essential services. The cumulative financial effect is therefore greater than the price of antibiotics alone. Resistant infections generate a cascade of expenses that begins with treatment failure and can extend through prolonged hospitalization, diagnostic investigation, rehabilitation, and productivity losses. Controlling resistance consequently represents an important economic strategy as well as a clinical necessity.
Morbidity and mortality
AMR contributes to increased morbidity and mortality by reducing the probability that infections will respond promptly to available treatment. Morbidity refers to illness, complications, and impaired functioning associated with disease, while mortality reflects deaths attributable to disease. When effective antimicrobial therapy is delayed or unavailable, an infection that might otherwise resolve can persist, worsen, or disseminate to other parts of the body.
Resistant infections can produce prolonged symptoms and complications, including tissue destruction, bloodstream infection, organ dysfunction, and recurrent disease. Patients may consequently experience longer periods of physical impairment and require extended medical care. The consequences can be particularly serious among individuals who are vulnerable to severe infection, including hospitalized patients, older adults, and people undergoing treatments that compromise normal immune defenses.
Mortality becomes a major concern when resistance limits the number of effective therapeutic choices. Even when alternative medicines exist, they may not be immediately available, may be less effective, or may carry significant adverse effects. Delays in administering effective treatment can therefore influence clinical outcomes.
The mortality burden of AMR also has consequences beyond individual patients. Premature deaths reduce workforce participation and can leave families without essential sources of income or caregiving. At the population level, increasing infection-related mortality places additional pressure on healthcare systems and social-support structures. AMR magnifies the consequences of infectious diseases by increasing both the duration and severity of illness and the likelihood of fatal outcomes. Its influence on morbidity and mortality makes resistance a central concern in contemporary public health planning.
Economic hardship
The economic consequences of AMR extend from individual households to communities, healthcare institutions, and national economies. When resistant infections require prolonged treatment, individuals and families may face expenses that exceed those associated with ordinary infectious diseases. Costs can include hospital fees, medicines, diagnostic investigations, transportation, accommodation for caregivers, and follow-up consultations. These financial pressures can be especially damaging to households that lack adequate health insurance or have limited disposable income.
Illness also produces economic losses through reduced productivity. Patients who are unable to work during prolonged infections may lose wages, while family members may have to reduce working hours or leave employment temporarily to provide care. When resistant infections affect large numbers of people, these individual losses can accumulate into substantial reductions in workforce productivity.
Healthcare systems similarly experience financial strain because resistant infections require greater expenditure on clinical management and infection prevention. Resources directed toward managing AMR-related complications may reduce the funds available for other priorities, including vaccination, maternal healthcare, disease prevention, and health-system infrastructure.
At the national level, widespread resistance can therefore become an impediment to economic development. Reduced productivity, increased healthcare expenditure, and premature mortality can weaken the economic contribution of affected populations. AMR may also deepen existing socioeconomic inequalities because financially disadvantaged populations often have fewer opportunities to obtain timely diagnosis and effective treatment.
Increased severity of infection
AMR can increase the clinical severity of infections by allowing pathogenic microorganisms to persist despite treatment. In a susceptible infection, effective antibiotic therapy can rapidly reduce the microbial burden and limit tissue damage. When the causative organism is resistant, however, continued replication may permit the infection to progress before an effective therapy is identified and administered.
Disease progression can involve the extension of infection from a localized site into deeper tissues or the bloodstream. In severe cases, systemic infection can trigger widespread inflammatory responses, organ dysfunction, and life-threatening complications. The longer an infection remains uncontrolled, the greater the opportunity for irreversible tissue injury and physiological deterioration.
The severity of resistant infections may also be influenced by the characteristics of the pathogen and the patient’s underlying condition. Some resistant organisms possess additional virulence-associated traits that can complicate disease management. Moreover, hospitalized patients with invasive devices, surgical wounds, or compromised immunity may be particularly susceptible to rapid progression.
Increasing severity creates a chain of consequences for both patients and healthcare providers. More serious infections generally require more intensive monitoring, broader diagnostic evaluation, intravenous therapy, and supportive interventions. Patients may subsequently experience prolonged recovery, functional limitations, or permanent complications.
AMR therefore changes the clinical trajectory of infectious disease. Rather than being a short-term condition readily controlled by standard therapy, infection may evolve into a complex and potentially life-threatening illness. Preventing resistance is consequently essential for preserving the possibility of early, effective, and uncomplicated treatment.
Loss of antimicrobial efficacy of available drugs
The progressive loss of antimicrobial efficacy represents one of the most fundamental consequences of resistance. The value of an antimicrobial agent depends on its ability to reliably inhibit or eliminate susceptible pathogens. When resistance becomes widespread, medicines that once served as dependable first-line therapies may gradually lose their clinical utility. This process narrows the therapeutic arsenal available to healthcare professionals and increases dependence on fewer remaining effective agents.
The erosion of antimicrobial efficacy is particularly concerning because the development of replacement medicines is scientifically complex, expensive, and time-consuming. The rate at which resistance emerges can outpace the introduction of new therapeutic options. Some newer or reserve antibiotics must therefore be protected from unnecessary use to preserve their effectiveness for infections in which conventional medicines are no longer reliable.
Loss of efficacy can also undermine medical procedures that depend on effective infection prevention and treatment. Surgery, chemotherapy, transplantation, neonatal care, and intensive care all rely on the capacity to manage bacterial infections successfully. If antimicrobial options become progressively limited, procedures that currently have acceptable risk profiles may become more difficult to perform safely.
The consequences extend into clinical decision-making. Physicians may increasingly need to rely on susceptibility testing, combination therapy, alternative agents, or individualized treatment strategies. This complexity can delay treatment and increase the likelihood of adverse outcomes.
Preserving antimicrobial efficacy is therefore equivalent to protecting a critical component of modern medicine. Every unnecessary exposure that accelerates resistance can contribute to the gradual depreciation of medicines whose effectiveness has been accumulated over decades of scientific and clinical progress.
Emergence and spread of novel drug-resistant microbes
The emergence and dissemination of novel drug-resistant microorganisms represent a dynamic dimension of AMR. Microbial populations possess considerable genetic adaptability, allowing resistance traits to arise through mutation or to be acquired from other organisms through horizontal gene transfer. Once resistance determinants become established, they can spread among bacterial populations under favourable conditions, particularly where antimicrobial exposure creates strong selective pressure.
The emergence of resistance is not restricted to hospitals. Communities, agricultural systems, food-production environments, wastewater, soil, and natural ecosystems can all participate in the circulation of resistant organisms and resistance genes. Human movement, international travel, food distribution, animal production, and healthcare-associated transmission can further accelerate geographical dissemination.
Novel resistance mechanisms are particularly concerning when they compromise multiple antimicrobial classes simultaneously. Multidrug-resistant organisms can leave clinicians with very limited treatment options, while organisms resistant to nearly all available therapies present an even more formidable challenge. The appearance of such pathogens can transform localized outbreaks into broader public health emergencies when surveillance and containment measures are inadequate.
The spread of resistant microbes also demonstrates why AMR cannot be addressed exclusively through prescribing practices. Effective containment requires coordinated surveillance, rapid laboratory identification, infection prevention, environmental management, responsible antimicrobial use in veterinary and agricultural settings, and international information sharing.
The emergence of novel resistant organisms represents an evolutionary contest between microbial adaptation and human therapeutic innovation. If resistance develops faster than effective countermeasures, the resulting gap can threaten the reliability of infectious-disease treatment. Sustained prevention and surveillance are therefore essential for limiting the emergence, amplification, and transmission of resistance.
References
Willy, C., & Bröcker, F. (2025). Gesundheitsökonomische Bedeutung antimikrobieller Resistenzen [Health economic significance of antimicrobial resistance]. Bundesgesundheitsblatt – Gesundheitsforschung – Gesundheitsschutz, 68(6), 584–592.
World Health Organization. (2024). Health and economic impacts of antimicrobial resistance in the Western Pacific Region, 2020–2030. www.who.int/publications/i/item/9789290620112
Ashutosh Kar (2008). Pharmaceutical Microbiology, 1st edition. New Age International Publishers: New Delhi, India.
Axelsen P.H (2002). Essentials of antimicrobial pharmacology. Humana Press, Totowa, New Jersey, USA. Al-Jasser A.M (2006). Extended – Spectrum Beta – Lactamases (ESBLs): A Global Problem. Kuwait Medical Journal, 38(3):171-185.
Bisht R., Katiyar A., Singh R and Mittal P (2009). Antibiotic Resistance – A Global Issue of Concern. Asian Journal of Pharmaceutical and Clinical Research, 2 (2):34-39.
Joslyn, L. J. (2000). Sterilization by Heat. In S. S. Block (Ed.), Disinfection, Sterilization, and Preservation (5th ed., pp. 695-728). Philadelphia, USA: Lippincott Williams and Wilkins.
Lai P.K and Roy J (2004). Antimicrobial and chemopreventive properties of herbs and spices. Curr. Med. Chem, 11 (11): 1451–1460.
Livermore D.M (2004). The need for new antibiotics. Clinical Microbiology & Infection, 4(10): 1-9.
Mascaretti O.A (2003). Bacteria versus antibacterial agents: An integrated approach. Washington: ASM Press.
Nally J.D (Ed.) (2007). Good manufacturing practices for pharmaceuticals. Sixth edition. Informa Healthcare USA, Inc, New York.
Discover more from Microbiology Class
Subscribe to get the latest posts sent to your email.