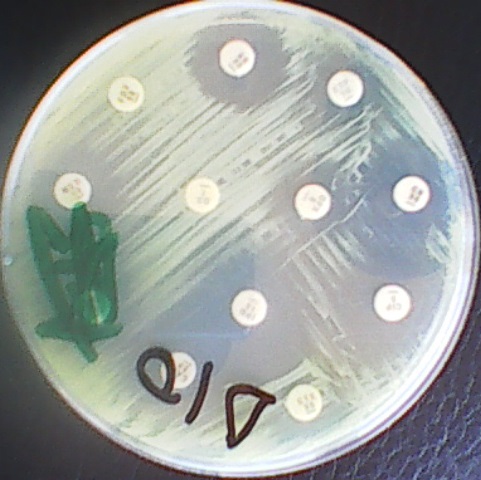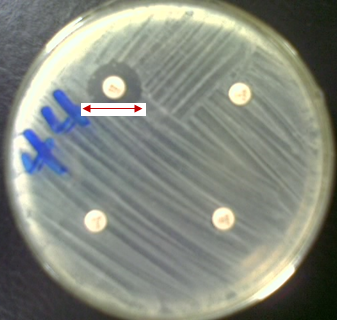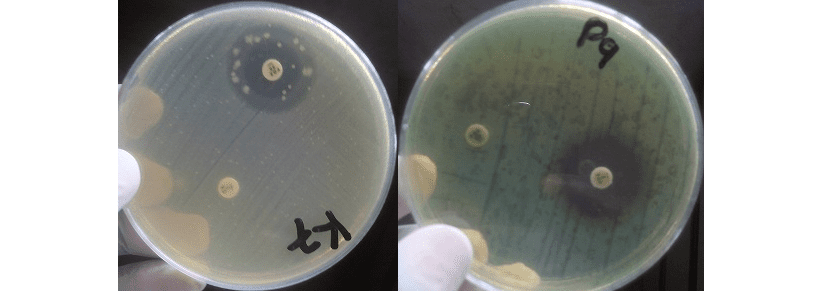
AmpC β-lactamases are clinically important cephalosporinases encoded on the chromosomes of many of the Enterobacteriaceae and a few other organisms, where they mediate resistance to cephalothin, cefazolin, cefoxitin, most penicillins, and β-lactamase inhibitor-β-lactam combinations.
They are Ambler class C β-lactamase enzymes that hydrolyze the β-lactam ring of susceptible antibiotics, thereby conferring resistance to a broad range of β-lactam antimicrobial agents. AmpC β-lactamases are particularly important because of their ability to hydrolyze penicillins, most cephalosporins, and cephamycins, including cefoxitin and cefotetan. AmpC enzymes also have activity against several third-generation cephalosporins, such as cefotaxime, ceftriaxone, and ceftazidime.
Unlike many extended-spectrum β-lactamases (ESBLs), AmpC enzymes are generally not inhibited by conventional β-lactamase inhibitors such as clavulanic acid, sulbactam, and tazobactam. This characteristic contributes significantly to the therapeutic challenges associated with infections caused by AmpC-producing bacteria. AmpC β-lactamases occur predominantly in Gram-negative bacteria and may be encoded chromosomally or carried on transferable plasmids.
Chromosomal ampC genes are naturally present in organisms such as members of the Enterobacter cloacae complex, Citrobacter freundii, Serratia marcescens, Morganella morganii, Providencia spp., and Pseudomonas aeruginosa. In several of these organisms, AmpC production can be inducible and may become markedly increased following exposure to certain β-lactam antibiotics. Mutations in regulatory pathways can also lead to stable derepression and persistent high-level enzyme production.
Plasmid-mediated AmpC (pAmpC) enzymes are acquired resistance determinants that can disseminate between bacteria through horizontal gene transfer. They are particularly important in Escherichia coli and Klebsiella pneumoniae, where acquisition of AmpC-bearing plasmids can produce resistance to cephamycins and extended-spectrum cephalosporins. Common pAmpC families include CMY, DHA, FOX, MOX, and ACC.
The emergence and dissemination of AmpC-producing bacteria represent an important antimicrobial-resistance concern in clinical and environmental settings. Accurate recognition of AmpC production is therefore essential for appropriate antimicrobial susceptibility interpretation, effective treatment selection, antimicrobial stewardship, infection prevention, and surveillance of β-lactam resistance.
Classification of AmpC β-lactamases
AmpC β-lactamases are clinically important Ambler class C β-lactamases that constitute an important mechanism of β-lactam resistance among Gram-negative bacteria. They are generally classified according to their genetic location and mode of dissemination into two types: chromosomally encoded AmpC β-lactamases and plasmid-mediated AmpC (pAmpC) β-lactamases. This classification is epidemiologically and clinically important because the two groups differ in their regulation, potential for horizontal transmission, and contribution to antimicrobial resistance.
Chromosomal AmpC enzymes are intrinsic resistance determinants in several Gram-negative organisms. Important bacterial groups possessing chromosomal ampC genes include the Enterobacter cloacae complex, C. freundii, S. marcescens, M. morganii, Providencia spp., and P. aeruginosa. The expression of chromosomal ampC varies considerably among bacterial species.
In organisms such as Enterobacter cloacae complex and C. freundii, AmpC expression may be inducible, meaning that enzyme production can increase in response to exposure to particular β-lactam antibiotics. Mutations affecting regulatory pathways may subsequently result in derepression, characterized by sustained, high-level production of AmpC. Such changes can produce clinically significant increases in resistance during antimicrobial therapy.
Plasmid-mediated AmpC β-lactamases are transferable resistance enzymes. These enzymes are encoded by ampC-related genes located on plasmids and other mobile genetic elements, allowing them to disseminate horizontally among bacterial populations. Important pAmpC families include CMY, DHA, FOX, MOX, ACC, and ACT/MIR-related enzymes. Among these, CMY-type enzymes are particularly widespread.
Plasmid-mediated AmpC is especially important in Escherichia coli and Klebsiella pneumoniae, organisms that generally lack the inducible chromosomal AmpC systems characteristic of organisms such as Enterobacter cloacae complex and C. freundii. Acquisition of an AmpC-bearing plasmid can therefore introduce an important resistance phenotype into previously susceptible bacterial populations.
AmpC enzymes may also be classified according to their biochemical properties and evolutionary relationships. Some AmpC enzymes are closely associated with particular bacterial species, whereas others have disseminated through mobile genetic elements. The mobility of pAmpC determinants is particularly concerning because plasmids may carry multiple resistance genes simultaneously, potentially producing multidrug-resistant phenotypes.
The classification of AmpC β-lactamases encompasses both genetic origin and regulatory behavior. Chromosomal AmpC is principally associated with intrinsic bacterial resistance and, in selected species, inducible or derepressed expression. Plasmid-mediated AmpC, in contrast, represents an acquired resistance mechanism with substantial potential for horizontal dissemination.
Characteristics and mechanisms of AmpC β-lactamases
AmpC β-lactamases are serine-dependent β-lactamases that hydrolyze the β-lactam ring of susceptible antimicrobial agents. Their substrate profile includes penicillins, most cephalosporins, and importantly, cephamycins such as cefoxitin and cefotetan. They can also hydrolyze many extended-spectrum cephalosporins, including cefotaxime, ceftriaxone, and ceftazidime. This broad hydrolytic activity can substantially reduce the therapeutic utility of β-lactam antibiotics against AmpC-producing organisms.
Unlike many ESBLs, AmpC enzymes are characteristically able to hydrolyze cephamycins and are generally not inhibited by traditional β-lactamase inhibitors, including clavulanic acid, sulbactam, and tazobactam. This biochemical distinction is useful when differentiating AmpC-mediated resistance from ESBL-mediated resistance.
The principal mechanism of AmpC-mediated resistance is enzymatic hydrolysis of the β-lactam antibiotic. Following penetration of the antibiotic into the bacterial periplasm, the drug interacts with the AmpC enzyme, resulting in disruption of the β-lactam ring. Because the intact β-lactam ring is essential for antibacterial activity against penicillin-binding proteins, hydrolysis prevents the antibiotic from effectively inhibiting bacterial cell-wall synthesis. The resulting reduction in antimicrobial activity may manifest as elevated minimum inhibitory concentrations (MICs) or clinical resistance.
A particularly important characteristic of chromosomal AmpC is its regulated expression. In organisms with inducible AmpC systems, basal enzyme production may be relatively low but can increase following exposure to certain β-lactam antibiotics. This regulation involves bacterial pathways associated with cell-wall recycling and transcriptional control of ampC. Mutations affecting these regulatory pathways can produce stable derepression and sustained high-level enzyme production.
Some organisms may initially demonstrate susceptibility to certain third-generation cephalosporins but subsequently develop resistance during treatment as resistant subpopulations are selected. Plasmid-mediated AmpC generally differs in its regulation and epidemiology. pAmpC genes are carried on transferable genetic elements and can spread through horizontal gene transfer, particularly bacterial conjugation.
Their acquisition allows organisms that do not normally possess clinically significant chromosomal AmpC systems to express the enzyme. This mechanism is particularly relevant to E. coli and K. pneumoniae. Because resistance plasmids may contain additional determinants for resistance to aminoglycosides, fluoroquinolones, sulfonamides, or other antimicrobial classes, pAmpC-producing isolates may exhibit multidrug resistance.
AmpC enzymes also differ in their susceptibility to β-lactam agents. Cefepime is relatively stable to AmpC hydrolysis compared with many third-generation cephalosporins and may retain activity against susceptible AmpC-producing organisms. Carbapenems are generally stable to hydrolysis by AmpC and may remain active when other β-lactams are compromised, although additional mechanisms such as porin loss or carbapenemase production can alter susceptibility.
AmpC-mediated resistance is the result of an interaction between enzyme production, substrate hydrolysis, genetic regulation, bacterial permeability, and additional resistance mechanisms. The clinical phenotype therefore cannot always be predicted solely from the presence of an ampC gene.
Genetic distribution, expression, and clinical significance of AmpC β-lactamases
The epidemiology of AmpC β-lactamases reflects the interaction between bacterial genetics, antimicrobial exposure, horizontal gene transfer, and selective pressure. Chromosomal AmpC is particularly associated with organisms such as Enterobacter cloacae complex, C. freundii, S. marcescens, M. morganii, and Providencia spp. These organisms may possess regulatory systems that permit inducible expression of their chromosomal ampC genes. Under basal conditions, enzyme production may be relatively low; however, exposure to selected β-lactam agents can stimulate increased expression. Mutational disruption of regulatory pathways can subsequently produce a stably derepressed phenotype with high-level AmpC production.
The clinical importance of this mechanism lies in the possibility of emergent resistance during antimicrobial treatment. An isolate that initially tests susceptible to a third-generation cephalosporin may contain a heterogeneous population of cells, some of which can acquire or select mutations resulting in increased AmpC expression. Continued antibiotic exposure may therefore favor these resistant subpopulations. This phenomenon is one reason why susceptibility results for organisms with inducible chromosomal AmpC require careful clinical interpretation.
Plasmid-mediated AmpC differs from classical inducible chromosomal AmpC in its epidemiology and genetic mobility. pAmpC genes are frequently located on mobile genetic elements and can move between bacterial strains and, in some circumstances, between species. E. coli and K. pneumoniae are particularly important hosts because acquisition of a plasmid-mediated AmpC gene can confer resistance to cephamycins and extended-spectrum cephalosporins. Plasmids may also carry additional resistance determinants, resulting in organisms with multidrug-resistant phenotypes.
AmpC-mediated resistance is especially significant because it can complicate interpretation of routine antimicrobial susceptibility testing. Resistance to cefoxitin and reduced susceptibility or resistance to third-generation cephalosporins may raise suspicion for AmpC production, but phenotype-based inference alone is not always sufficient. The coexistence of AmpC with other β-lactamases, including ESBLs and carbapenemases, can further complicate interpretation.
AmpC enzymes are also relevant to antimicrobial stewardship because inappropriate use of broad-spectrum antibiotics can increase selection pressure favoring resistant organisms. From a public-health perspective, AmpC-producing bacteria have been identified not only in hospitals but also in community, food, animal, wastewater, and other environmental settings. Surveillance should consider the One Health dimension of antimicrobial resistance.
AmpC should not be regarded as synonymous with multidrug resistance. AmpC primarily affects β-lactam susceptibility, while the overall resistance phenotype depends on additional mechanisms, including alterations in permeability, efflux pumps, target-site mutations, and acquisition of other resistance genes.
Laboratory detection and differentiation of AmpC β-lactamases from ESBLs
Reliable detection of AmpC β-lactamases is important because routine antimicrobial susceptibility testing may not always adequately predict the clinical significance of inducible or derepressed AmpC production. Detection is particularly challenging when AmpC occurs together with other β-lactamases, such as ESBLs or carbapenemases. The laboratory approach should therefore be based on the bacterial species, local epidemiology, susceptibility profile, and the diagnostic standards adopted by the laboratory.
Phenotypically, resistance or reduced susceptibility to cephamycins, particularly cefoxitin, can provide an indication of possible AmpC production. Resistance to third-generation cephalosporins may provide additional evidence. These findings are not specific for AmpC because resistance can arise through other mechanisms, including ESBL production combined with porin loss or other permeability changes.
One of the major distinctions between AmpC and ESBLs is their response to β-lactamase inhibitors. ESBL activity is generally inhibited by clavulanate, whereas AmpC enzymes are not reliably inhibited by clavulanate, sulbactam, or tazobactam. This distinction can be useful in phenotypic investigations. However, inhibitor-based tests must be interpreted cautiously because the presence of multiple β-lactamases can produce complex or misleading phenotypes.
Several phenotypic approaches have been investigated for AmpC detection, including tests using boronic acid compounds, cloxacillin, and other AmpC inhibitors, as well as assays based on cefoxitin susceptibility. EDTA-based methods are primarily associated with investigation of metallo-β-lactamases, because EDTA chelates zinc ions required for metalloenzyme activity; therefore, EDTA should not be regarded as a universal or specific AmpC inhibitor. The choice and interpretation of phenotypic tests should follow current laboratory standards rather than relying on a single screening method.
Molecular detection provides an alternative approach. PCR and other nucleic-acid-based techniques can identify important plasmid-mediated ampC families, including blaCMY, blaDHA, blaFOX, blaMOX, and related determinants. Whole-genome sequencing can provide more comprehensive characterization, particularly in epidemiological investigations and outbreak surveillance. Detection of an ampC gene does not necessarily quantify its expression or establish the clinical significance of a particular phenotype.
Differentiation from ESBL production is particularly important. ESBLs generally hydrolyze oxyimino-cephalosporins but do not characteristically hydrolyze cephamycins, whereas AmpC enzymes efficiently hydrolyze cephamycins and are not inhibited by clavulanate. An organism may, however, produce both ESBL and AmpC enzymes, making phenotypic interpretation considerably more difficult. Laboratories should integrate organism identification, antimicrobial susceptibility testing, phenotypic testing where appropriate, and molecular methods when indicated.
Therapeutic implications, antimicrobial stewardship, and prevention of AmpC β-lactamases
AmpC-producing organisms present important therapeutic challenges because many commonly used β-lactam antibiotics may be unreliable, particularly when high-level AmpC production is present. Treatment should therefore be guided by organism identification, antimicrobial susceptibility results, infection site, severity of illness, pharmacokinetic and pharmacodynamic considerations, and the specific AmpC mechanism. There is no single antibiotic regimen that is appropriate for every AmpC-producing organism or infection.
Third-generation cephalosporins require particular caution in infections caused by organisms capable of inducible chromosomal AmpC production. Even when an isolate initially appears susceptible, treatment may select for resistant subpopulations through increased AmpC expression. Susceptibility results must be interpreted within the biological context of the organism rather than considered in isolation.
Cefepime is relatively stable against AmpC hydrolysis and is a potentially useful option when the isolate demonstrates appropriate susceptibility and the clinical circumstances are suitable. Its use should nevertheless be guided by the infection type, bacterial species, MIC, and the possibility of additional resistance mechanisms. Carbapenems remain active against many AmpC-producing organisms and may be appropriate for severe infections caused by isolates with limited β-lactam treatment options.
Unnecessary carbapenem use can impose substantial selection pressure and contribute to the emergence and dissemination of carbapenem-resistant organisms. Non-β-lactam agents may provide alternatives when susceptibility is demonstrated. Depending on the organism and infection, these can include fluoroquinolones, aminoglycosides, trimethoprim-sulfamethoxazole, or other active agents. Their appropriateness is highly dependent on the infection site and patient-specific factors.
Temocillin, where available and licensed, has also demonstrated activity against many Enterobacterales, although its availability and clinical indications vary geographically. Tigecycline may retain in-vitro activity against some AmpC-producing organisms, but its pharmacological properties limit its suitability for certain serious infections, particularly bloodstream infections.
Antimicrobial stewardship is therefore central to controlling AmpC-mediated resistance. Stewardship programs should promote accurate diagnosis, appropriate antimicrobial selection, optimized dosing, de-escalation when clinically appropriate, and avoidance of unnecessarily prolonged broad-spectrum therapy. Surveillance of AmpC-producing organisms can help identify changes in resistance patterns and detect outbreaks or transmission clusters.
Prevention also requires effective infection-control practices, including hand hygiene, environmental cleaning, appropriate isolation precautions where indicated, and microbiological surveillance during suspected outbreaks. Because AmpC genes may occur on transferable plasmids, control efforts should extend beyond individual patients to consider transmission between bacterial strains and species.
Management of AmpC-mediated resistance requires integration of microbiology, clinical medicine, antimicrobial stewardship, infection prevention, and molecular epidemiology. Improved diagnostic methods, continued surveillance, responsible antimicrobial use, and research into novel β-lactam/β-lactamase inhibitor combinations remain essential for reducing the clinical and public-health impact of AmpC β-lactamases.
Treatment of infections caused by AmpC-producing bacteria
Treatment of infections caused by AmpC-producing organisms presents a significant therapeutic challenge because AmpC β-lactamases can hydrolyze many β-lactam antibiotics and may be expressed at different levels during infection. The clinical relevance of AmpC production is particularly important in organisms such as Enterobacter cloacae complex, Klebsiella aerogenes, and C. freundii, where inducible chromosomal AmpC expression can increase during antimicrobial exposure. Consequently, antimicrobial selection should consider not only the initial susceptibility result but also the potential for resistance to emerge during therapy.
For serious infections caused by organisms with a high risk of clinically significant AmpC production, cefepime is commonly considered when the isolate demonstrates susceptibility. Cefepime has relatively greater stability against AmpC hydrolysis than many third-generation cephalosporins and may therefore provide a useful β-lactam option for selected infections. Its effectiveness can be influenced by the bacterial AmpC expression level, the presence of additional resistance mechanisms, and the site and severity of infection. Appropriate dosing, particularly optimization of exposure in critically ill patients, is therefore important.
Carbapenems remain an important option for severe infections when resistance to other β-lactams limits therapeutic choices. Agents such as meropenem or imipenem are highly stable against AmpC enzymes and can provide reliable activity against susceptible isolates. Nevertheless, their broad antibacterial spectrum makes antimicrobial stewardship essential, particularly when narrower effective alternatives are available. Carbapenem use should therefore be guided by infection severity, susceptibility data, previous antimicrobial exposure, and the possibility of coexisting resistance mechanisms.
Third-generation cephalosporins, including ceftriaxone, cefotaxime, and ceftazidime, require particular caution in infections involving organisms capable of inducible AmpC production. Although an isolate may initially appear susceptible in vitro, antimicrobial exposure can select for bacterial subpopulations with increased AmpC expression, potentially resulting in treatment failure. For this reason, susceptibility alone may not adequately predict clinical reliability for infections in which a substantial bacterial burden or prolonged treatment is expected.
Non-β-lactam agents may provide alternative therapeutic strategies when susceptibility is demonstrated. Fluoroquinolones and trimethoprim-sulfamethoxazole are not affected by AmpC hydrolysis and can be considered for appropriate infections, particularly when clinical stability and adequate drug exposure are achievable. Selection should remain individualized according to antimicrobial susceptibility, infection site, patient characteristics, and local resistance patterns.
Successful management of AmpC-associated infections depends on integrating microbiological findings with clinical circumstances rather than relying solely on the reported susceptibility profile. Rapid identification of AmpC-producing organisms, appropriate antimicrobial exposure, source control, and reassessment of therapy during treatment are central to reducing the risk of resistance development and improving clinical outcomes.
References
Bush, K., Jacoby, G. A., & Medeiros, A. A. (1995). A functional classification scheme for β-lactamases and its correlation with molecular structure. Antimicrobial Agents and Chemotherapy, 39(6), 1211–1233.
Ejikeugwu C, Nworie O, Saki M, Al-Dahmoshi HOM, Al-Khafaji NSK, Ezeador C, Nwakaeze E, Eze P, Oni E, Obi C, Iroha I, Esimone C, Adikwu MU (2021). Detection of metallo-β-lactamase and AmpC genes in Escherichia coli, Klebsiella species, and Pseudomonas aeruginosa isolates from abattoir and poultry origin in Nigeria. BMC Microbiology, 21(124):1-9.
EjikeugwuC, HassonSO, Al-MosawiRM, AlkhudhairyMK, SakiM, EzeadorC, EzeP, Ugwu M, Duru C, Ujam NT, Edeh C, Udu-IbiamO,Iroha I,Adikwu M (2020). Occurrence of FOX-1 AmpC Gene among Pseudomonas aeruginosa isolates in abattoir samples from south-eastern Nigeria. Reviews in Medical Microbiology, 31(2):99-103.
Ejikeugwu C, Esimone C, Iroha I,Adikwu M (2018).First Detection of FOX-1 AmpC β-lactamase gene expression among Escherichia coli isolated from abattoir samples in Abakaliki, Nigeria. Oman Medical Journal, 33(3):134-140.
Halat, D. H., Sarkis, D. K., & Moubareck, C. A. (2016). Carbapenem-resistant, Gram-negative bacilli: The state of the art. In Antibiotic resistance (pp. 93–119). Academic Press.
Hanson, N. D. (2003). AmpC β-lactamases: What do we need to know for the future? Journal of Antimicrobial Chemotherapy, 52(1), 2–4.
Jacoby, G. A. (2009). AmpC β-lactamases. Clinical Microbiology Reviews, 22(1), 161–182.
Pandey, D., Gupta, I., & Gupta, D. (2025). AmpC β-lactamases: A key to antibiotic resistance in ESKAPE pathogens. The Cell Surface, 14, 100154.
Philippon, A., Arlet, G., & Jacoby, G. A. (2002). Plasmid-determined AmpC-type β-lactamases. Antimicrobial Agents and Chemotherapy, 46(1), 1–11.
Tamma, P. D., Doi, Y., Bonomo, R. A., Johnson, J. K., & Simner, P. J. (2019). A primer on AmpC β-lactamases: Necessary knowledge for an increasingly multidrug-resistant world. Clinical Infectious Diseases, 69(8), 1446–1455.
Tebano, G., Zaghi, I., Cricca, M., & Cristini, F. (2024). Antibiotic treatment of infections caused by AmpC-producing Enterobacterales. Pharmacy, 12(5), 142.
Discover more from Microbiology Class
Subscribe to get the latest posts sent to your email.