

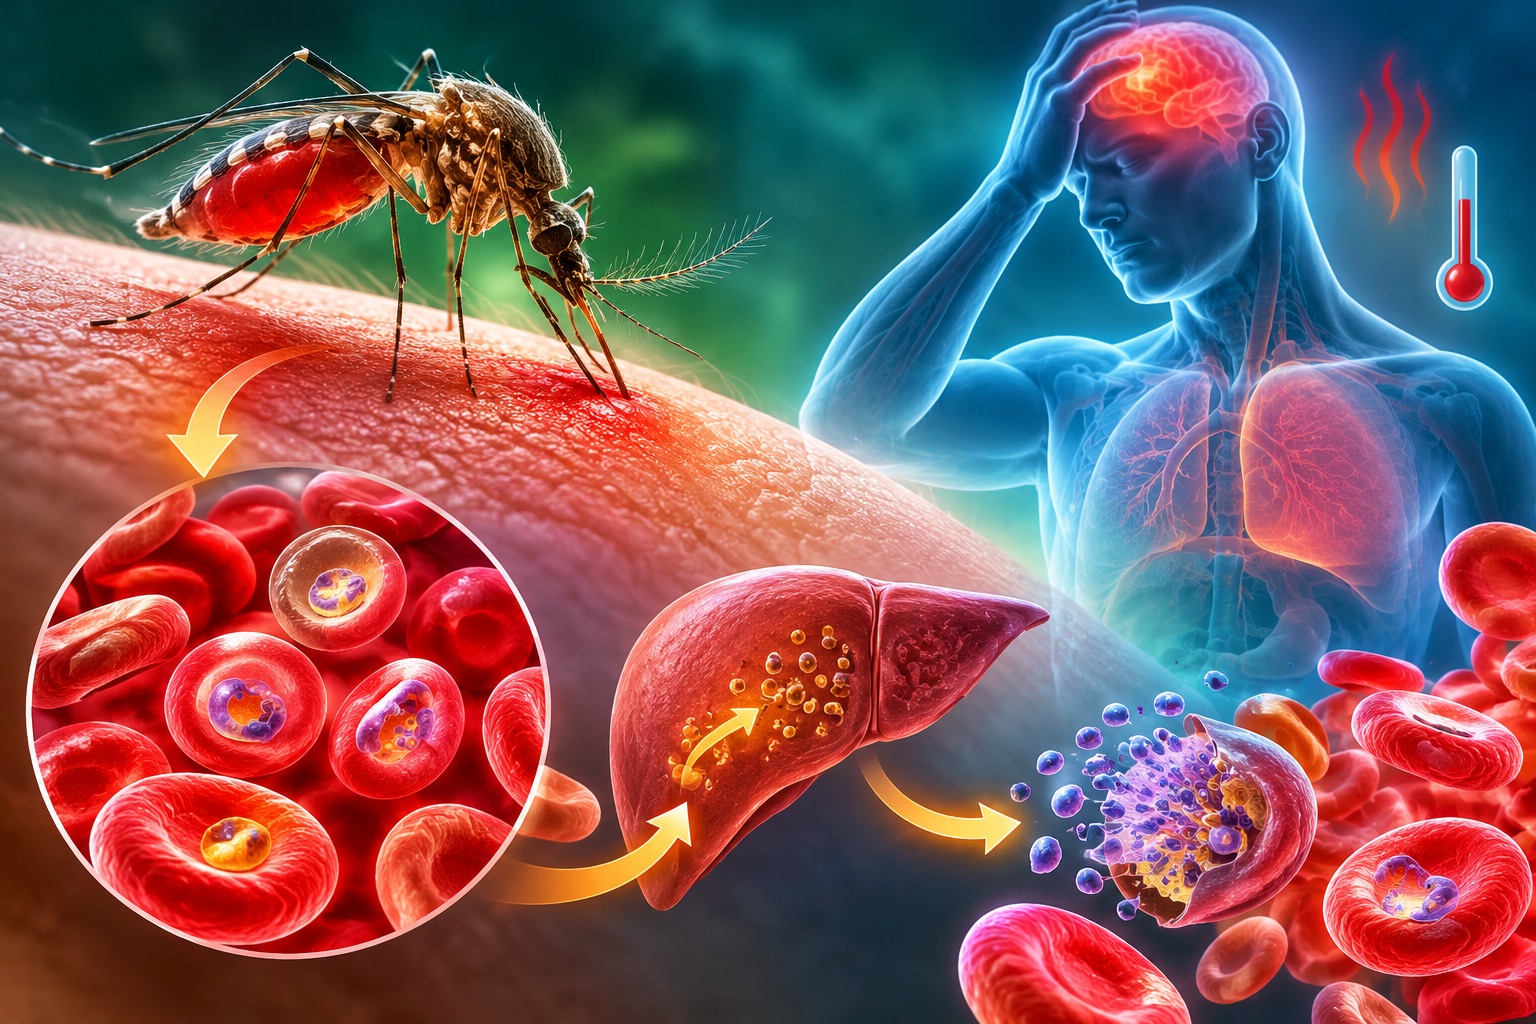
Malaria is a mosquito-borne parasitic infectious disease caused by Plasmodium species and transmitted to humans through the bite of an infected female Anopheles mosquito. It is characterized by recurrent episodes of fever, chills, sweating, headache, fatigue and, in severe cases, anaemia and other life-threatening complications. The disease occurs predominantly in tropical and subtropical regions of the world, particularly sub-Saharan Africa, where favourable climatic conditions, environmental factors and socioeconomic challenges contribute to its continued transmission. Malaria remains one of the most significant vector-borne diseases and a major public health concern worldwide.
Vector-borne diseases are infectious diseases transmitted by living organisms known as vectors. These vectors include mosquitoes, ticks, sand flies and certain freshwater snails, which carry and transmit disease-causing microorganisms or parasites between humans and, in some cases, animals and humans. Many vectors are blood-feeding organisms that acquire pathogens while feeding on an infected host and subsequently transmit them to susceptible individuals during another blood meal. In the case of malaria, the female Anopheles mosquito serves as the principal vector, transmitting Plasmodium parasites from an infected individual to an uninfected person through its bite.
The Plasmodium parasite is the causative agent of malaria and belongs to the protozoan group of parasites. Several species infect humans, including Plasmodium falciparum, Plasmodium vivax, Plasmodium malariae, Plasmodium ovale and Plasmodium knowlesi. Among these species, P. falciparum is responsible for the majority of malaria-related deaths, particularly in Africa. Following the bite of an infected mosquito, the parasites enter the human bloodstream, travel to the liver and multiply before invading red blood cells (erythrocytes), where they continue their development and reproduction. The destruction of infected red blood cells contributes to the characteristic symptoms of malaria, including fever, chills and anaemia.
Historically, significant scientific discoveries have contributed to the understanding of malaria transmission and its causative organism. In 1880, Alphonse Laveran, a French army surgeon, discovered the malaria parasite in the blood of an infected patient. Subsequently, Ronald Ross demonstrated the role of mosquitoes in malaria transmission in 1897 by identifying malaria parasites in the tissues of infected mosquitoes. These discoveries established the scientific foundation for understanding the malaria parasite’s life cycle, which involves both human hosts and mosquito vectors.
Despite considerable advances in malaria prevention, diagnosis and treatment, the disease continues to pose a substantial global health challenge. Various interventions, including insecticide-treated mosquito nets, indoor residual spraying, environmental sanitation, antimalarial medications and malaria vaccination, have been introduced to reduce its transmission and associated complications. International initiatives, including the Roll Back Malaria Partnership, have also contributed to global malaria control and elimination efforts. However, challenges such as insecticide resistance, antimalarial drug resistance, inadequate healthcare facilities, poverty and poor environmental conditions continue to hinder effective malaria control in many endemic communities.
According to the World Health Organization (WHO), malaria remains a major cause of illness and death worldwide, with the African Region accounting for the greatest proportion of the global disease burden. Children under five years of age and pregnant women are particularly vulnerable to severe malaria and its complications. Malaria remains an important public health concern, especially in endemic countries, where it contributes significantly to morbidity, mortality and socioeconomic challenges. Therefore, understanding the causes, transmission, symptoms, diagnosis, treatment and prevention of malaria is essential for developing effective control strategies and reducing its impact on human health.
Malaria occurs predominantly in tropical and subtropical environments, where climatic conditions support the survival and reproduction of mosquito vectors. Sub-Saharan Africa carries the greatest proportion of the global disease burden, while cases also occur in parts of Southeast Asia, the Eastern Mediterranean, the Western Pacific, and South America. Temperature, rainfall, humidity, environmental conditions, healthcare accessibility, and vector-control interventions influence its geographical distribution.
Although malaria can affect individuals of different ages and backgrounds, certain populations experience greater susceptibility to severe disease. Children under five years of age, pregnant women, individuals with weakened immunity, and people living in malaria-endemic communities face particularly elevated risks. Travellers visiting endemic regions without adequate preventive protection are also vulnerable. Limited access to healthcare, poor housing conditions, inadequate sanitation, and socioeconomic disadvantage can further increase exposure and worsen disease outcomes.
Causes and transmission of malaria
The transmission of malaria involves a complex biological interaction between an infected human host, a female Anopheles mosquito, and the malaria-causing parasite.
Plasmodium parasite: The primary cause of malaria is infection with Plasmodium parasites. Five species are known to cause malaria in humans: P. falciparum, P. vivax, P. malariae, P. ovale, and P. knowlesi. Among these species, P. falciparum is particularly associated with severe malaria and life-threatening complications. Following their introduction into the human bloodstream, the parasites travel to the liver, where they multiply before invading red blood cells. Their subsequent multiplication within these cells contributes to the clinical manifestations of malaria.
Female anopheles mosquito: The female mosquito of the genus Anopheles serves as the principal biological vector responsible for transmitting malaria parasites. Unlike male mosquitoes, which primarily feed on plant sugars, female mosquitoes require blood meals to support egg development. When a female Anopheles mosquito feeds on a person carrying malaria parasites, it ingests the parasites alongside the blood. The parasites subsequently undergo further development within the mosquito, eventually reaching its salivary glands. This biological transformation enables the mosquito to transmit the infection to another human host during a subsequent blood meal.
Transmission through mosquito bites: The most common route of malaria transmission is the bite of an infected female Anopheles mosquito. During feeding, the mosquito introduces infective parasite stages, known as sporozoites, into the human bloodstream through its saliva. These microscopic organisms rapidly migrate to the liver, where they invade liver cells and undergo multiplication. After this developmental phase, newly formed parasites enter the bloodstream and infect red blood cells. The infection becomes established within the human body and may produce symptoms such as fever, chills, headache, sweating, and general weakness.
Transmission through infected blood: Although mosquito bites account for most malaria infections, transmission can also occur through exposure to parasite-contaminated blood. This may happen during blood transfusions involving infected donations, organ transplantation, or the sharing of contaminated needles and syringes. Such transmission is particularly significant because it bypasses the mosquito stage of the parasite’s life cycle. In these circumstances, malaria parasites are introduced directly into the recipient’s bloodstream, potentially resulting in infection. Proper blood screening, sterilization of medical equipment, and adherence to safe transfusion procedures are therefore important preventive measures.
Mother-to-child transmission: Malaria can also pass from an infected pregnant woman to her unborn child through the placenta, a condition known as congenital malaria. This transmission may expose the developing fetus to malaria parasites and increase the risk of adverse pregnancy outcomes, including premature delivery, low birth weight, fetal growth restriction, and maternal anemia. In some instances, the newborn may develop malaria symptoms after birth. This pathway demonstrates the importance of malaria prevention, prompt diagnosis, and appropriate treatment throughout pregnancy to protect both maternal and fetal health.
Malaria transmission cycle: The transmission cycle of malaria involves alternating developmental stages within human and mosquito hosts. It begins when an infected female Anopheles mosquito introduces sporozoites into a person’s bloodstream. These parasites migrate to the liver, multiply, and subsequently release merozoites that invade red blood cells. Some parasites develop into sexual forms called gametocytes. When another female Anopheles mosquito feeds on the infected individual, it ingests these gametocytes. Within the mosquito, fertilization and further parasite development occur, eventually producing sporozoites that migrate to the salivary glands. The mosquito can then infect another person, thereby sustaining the continuous transmission of malaria within susceptible populations.
Signs and symptoms of malaria
The symptoms of malaria develop as the parasites multiply within the liver and subsequently infect red blood cells. The severity and progression of these symptoms vary depending on the parasite species, the individual’s immune response, and the duration of infection. One of the most prominent manifestations is fever, which may occur periodically as infected red blood cells rupture and release parasites into the bloodstream. This is frequently accompanied by chills and shivering, resulting from the body’s response to sudden changes in temperature.
Following the cold stage, patients may experience excessive sweating, which often coincides with a gradual reduction in body temperature. Another common symptom is headache, which may range from mild discomfort to intense and persistent pain. In addition, infected individuals frequently report muscle and joint pain, commonly described as body aches, which contribute to physical discomfort and reduced mobility.
These manifestations are associated with the inflammatory response triggered by the malaria parasite. Nausea and vomiting may also develop, sometimes accompanied by abdominal discomfort and reduced appetite. These gastrointestinal disturbances can interfere with normal food intake and contribute to dehydration, particularly when vomiting becomes persistent. Malaria may cause general body weakness and fatigue, leaving affected individuals physically exhausted and unable to perform routine activities effectively.
In more advanced cases, the destruction of red blood cells can result in severe anaemia, a condition characterized by reduced haemoglobin levels and inadequate oxygen transportation throughout the body. This may present with pale skin, dizziness, breathlessness, and extreme tiredness. In severe infections, additional warning signs may include confusion, convulsions, difficulty breathing, and impaired consciousness. These manifestations require urgent medical attention because they may indicate life-threatening complications.
Diagnosis of malaria
The diagnosis of malaria involves a systematic clinical assessment and laboratory investigation to establish the presence of malaria parasites in the blood. Accurate diagnosis is essential for identifying infected individuals, determining the severity of the disease, and initiating appropriate treatment. Since malaria presents with symptoms that may resemble other infectious diseases, clinical symptoms alone are insufficient to confirm an infection. Therefore, healthcare professionals rely on a combination of medical history, physical examination, and laboratory-based diagnostic techniques to achieve reliable results.
Medical history and physical examination: The diagnostic process begins with obtaining relevant information about the patient’s health condition, previous illnesses, and possible exposure to malaria. Healthcare professionals inquire about recent travel or residence in malaria-endemic regions, previous episodes of malaria, mosquito exposure, and the onset and duration of symptoms. Physical examination involves assessing body temperature, pulse rate, respiratory rate, blood pressure, and general physical appearance. Particular attention is given to symptoms such as fever, chills, sweating, headache, weakness, and vomiting. In suspected severe cases, clinicians also examine the patient for jaundice, pallor, altered consciousness, and other signs of organ dysfunction.
Blood smear microscopy: Blood smear microscopy is an established laboratory method for confirming malaria infection. It involves collecting a small blood sample, preparing a thick or thin blood film on a microscope slide, staining it with Giemsa stain, and examining it under a microscope. Thick blood films are particularly useful for detecting malaria parasites because they allow examination of a larger volume of blood. Thin blood films help identify the Plasmodium species and determine the percentage of infected red blood cells. This technique provides valuable information about parasite density, species identification, and the progression of infection.
Rapid diagnostic tests (RDTs): Rapid diagnostic tests are commonly employed to identify malaria infections, particularly in healthcare facilities where microscopy services are limited. These tests detect specific proteins, known as antigens, produced by malaria parasites in the blood. A small blood sample is placed on a test device, and the result is usually available within approximately 15-30 minutes. RDTs offer a convenient diagnostic option because they require minimal laboratory equipment and can be performed by trained healthcare personnel. However, their accuracy may vary depending on parasite concentration, test quality, and the presence of certain parasite strains.
Malaria parasite detection and identification: Identifying the malaria-causing organism is an important aspect of diagnosis. Human malaria is primarily associated with five Plasmodium species. Differentiating these species is important because they vary in geographical distribution, clinical presentation, and potential complications. Molecular diagnostic techniques, including polymerase chain reaction (PCR), can detect parasite genetic material and provide more precise species identification. These techniques are particularly useful in complex cases and specialized laboratory investigations.
Laboratory investigations: Additional laboratory investigations may be conducted to evaluate the patient’s general health and identify complications associated with malaria. A complete blood count can reveal anaemia and reduced platelet levels, while blood chemistry tests may indicate kidney or liver impairment. Blood glucose measurements are particularly important in patients with severe malaria because dangerously low blood sugar can occur. Other investigations may include bilirubin, electrolyte, and renal function assessments. These tests support clinical decision-making and help determine the appropriate level of patient care.
Early diagnosis and detection: Early diagnosis plays a significant role in reducing malaria-related complications, hospital admissions, and mortality. Prompt testing enables healthcare providers to distinguish malaria from other febrile illnesses and administer appropriate antimalarial treatment without unnecessary delay. Where initial testing is negative but clinical suspicion remains high, repeat blood film examinations may be necessary. Effective diagnostic services, public awareness, accessible testing facilities, and trained healthcare professionals are therefore essential components of malaria prevention and control.
Treatment and management of malaria
The treatment and management of malaria involve a systematic approach aimed at eliminating malaria parasites from the human body, relieving clinical symptoms, preventing disease progression, and reducing the risk of life-threatening complications. Effective malaria management depends on early diagnosis, appropriate selection of antimalarial medications, accurate assessment of disease severity, and continuous monitoring of the patient’s response to treatment. The choice of therapy is influenced by the species of Plasmodium responsible for the infection, the patient’s age, body weight, pregnancy status, clinical condition, and the prevalence of drug resistance in the affected geographical region.
Artemisinin-based combination therapies (ACTs): Artemisinin-based combination therapies are widely recommended for treating uncomplicated P. falciparum malaria. These therapeutic combinations contain an artemisinin derivative, which rapidly reduces the number of malaria parasites circulating in the bloodstream, alongside a longer-acting partner drug that eliminates the remaining parasites. Common ACT regimens include artemether-lumefantrine, artesunate-amodiaquine, and dihydroartemisinin-piperaquine. Combining these medications improves treatment effectiveness and helps delay the development of antimalarial drug resistance. Patients should complete the prescribed treatment course to achieve adequate parasite clearance and minimize the possibility of recurrent infection.
Antimalarial medications: Antimalarial medications are selected according to the identified parasite species, infection severity, and regional treatment guidelines. Chloroquine may be appropriate in areas where susceptible malaria parasites remain prevalent, while other medications, including quinine and atovaquone-proguanil, have specific clinical applications. Infections caused by P. vivax and P. ovale may require additional treatment with primaquine or tafenoquine to eliminate dormant liver-stage parasites known as hypnozoites and prevent relapse. Before administering these medicines, glucose-6-phosphate dehydrogenase (G6PD) deficiency testing is necessary because certain medications can cause serious haemolytic reactions in susceptible individuals.
Treatment of severe malaria: Severe malaria constitutes a medical emergency requiring immediate hospitalization and specialized clinical intervention. Patients may present with impaired consciousness, repeated convulsions, severe anaemia, respiratory distress, kidney impairment, hypoglycaemia, or circulatory collapse. Prompt administration of effective antimalarial treatment is essential to prevent irreversible tissue damage and death. Clinical management also involves maintaining vital organ functions, correcting metabolic abnormalities, ensuring adequate hydration, and addressing associated complications. Delays in initiating appropriate treatment can significantly worsen the patient’s prognosis.
Administration of intravenous artesunate: Intravenous artesunate is the preferred initial treatment for severe malaria in both children and adults. It acts rapidly against malaria parasites by interfering with their essential metabolic processes, thereby reducing parasite density in the bloodstream. Treatment is administered according to established clinical protocols, followed by a complete oral antimalarial combination regimen once the patient can tolerate oral medication. Patients receiving intravenous artesunate require careful observation because delayed haemolytic anaemia may develop after treatment, making post-treatment monitoring important.
Management of malaria-related complications: Effective malaria management extends beyond parasite elimination to include the identification and treatment of associated physiological disturbances. Severe anaemia may require blood transfusion when clinically indicated, while hypoglycaemia requires prompt glucose administration. Patients experiencing acute kidney injury may need specialized renal support, including dialysis in severe cases. Respiratory complications, seizures, dehydration, and electrolyte imbalances also require appropriate supportive interventions. Individualized clinical care helps improve treatment outcomes and reduces the likelihood of permanent organ damage.
Follow-up and monitoring: Continuous follow-up is essential for assessing therapeutic effectiveness and identifying possible treatment failure or disease recurrence. Healthcare professionals monitor body temperature, neurological condition, haemoglobin levels, blood glucose, and other relevant clinical parameters. Repeat blood examinations may be necessary to determine whether malaria parasites have been successfully cleared. Patients should also receive guidance on medication adherence, mosquito-bite prevention, and early recognition of recurring symptoms. Proper follow-up strengthens recovery, minimizes complications, and contributes to the broader control of malaria transmission.
Complications and effects of malaria
Malaria is a potentially life-threatening parasitic disease that can produce extensive physiological damage when diagnosis and treatment are delayed. Its complications arise from the destruction of red blood cells, obstruction of small blood vessels, and inflammatory responses triggered by the malaria parasite. The severity of these effects varies according to the parasite species, the patient’s immune status, age, and general health.
One major complication is severe anaemia, which develops when infected and uninfected red blood cells are destroyed at an accelerated rate. This reduces the oxygen-carrying capacity of the blood, resulting in extreme weakness, dizziness, breathlessness, and, in critical cases, cardiovascular failure.
Cerebral malaria is another devastating manifestation, particularly associated with P. falciparum. It occurs when infected red blood cells accumulate within the small blood vessels of the brain, causing impaired circulation, neurological dysfunction, seizures, altered consciousness, and potentially permanent brain damage.
Malaria may precipitate multiple organ dysfunction, affecting essential organs such as the kidneys and liver. Acute kidney injury can develop when severe infection disrupts normal renal function, while respiratory distress may result from pulmonary complications and fluid accumulation in the lungs. These conditions require urgent medical intervention to prevent fatal outcomes.
Pregnant women are particularly vulnerable to malaria-related complications. Infection during pregnancy can cause maternal anaemia, placental damage, miscarriage, premature delivery, low birth weight, and stillbirth. Infants and young children also face an increased risk of severe illness and mortality because their immune systems may not have developed sufficient protection against the parasite.
Beyond its clinical consequences, malaria imposes considerable socioeconomic pressure on affected communities. Repeated illness contributes to school absenteeism, reduced workplace productivity, increased healthcare expenditure, household financial instability, and persistent poverty. Malaria remains not only a medical concern but also a significant obstacle to educational advancement, economic development, and public health improvement.
Prevention and control of malaria
Malaria prevention and control involve a coordinated application of protective measures, environmental interventions, medical innovations, and public health initiatives aimed at interrupting the transmission of malaria parasites. Since the disease is primarily transmitted through the bite of infected female Anopheles mosquitoes, effective prevention focuses on reducing human exposure to mosquito bites, controlling mosquito populations, and strengthening community awareness. Implementing these strategies consistently can significantly reduce malaria infections, prevent severe complications, and improve the overall health and well-being of vulnerable populations.
One of the most effective preventive approaches is the use of insecticide-treated mosquito nets (ITNs), particularly long-lasting insecticidal nets (LLINs). These nets provide a physical barrier between humans and mosquitoes while exposing mosquitoes to insecticides that can kill them or reduce their ability to transmit the parasite. Sleeping under treated mosquito nets every night, especially during periods of increased mosquito activity, offers considerable protection against infection. Their distribution among households, particularly in malaria-endemic communities, remains an essential component of malaria prevention programmes.
Another important intervention is indoor residual spraying (IRS), which involves applying approved insecticides to the interior walls and surfaces of residential buildings where mosquitoes commonly rest. When mosquitoes come into contact with treated surfaces, the insecticide kills them, thereby reducing their population and limiting the likelihood of malaria transmission. Regular implementation of indoor spraying, under appropriate public health supervision, can strengthen household protection and complement the use of insecticide-treated nets.
Environmental management also plays a significant role in malaria control. Female Anopheles mosquitoes breed in suitable water collections, making the elimination of unnecessary stagnant water an important preventive measure. Communities should regularly clear blocked drainage systems, dispose of discarded containers, cover water storage vessels, and maintain clean surroundings. Proper waste disposal and improved drainage reduce potential mosquito breeding habitats and contribute to a healthier living environment.
Personal protection through mosquito repellents and appropriate clothing provides additional defence against mosquito bites. Repellents containing recognised active ingredients, such as DEET, picaridin, or IR3535, can reduce mosquito contact when applied according to product instructions. Wearing long-sleeved shirts, trousers, and other protective garments, particularly during evening and nighttime activities, further minimises exposed skin. These measures are especially useful for individuals living in or travelling to areas where malaria transmission occurs.
Malaria vaccination represents another important advancement in disease prevention. Vaccines such as RTS,S/AS01 and R21/Matrix-M have been recommended by the World Health Organization for children living in areas with moderate to high malaria transmission. These vaccines help reduce the risk of malaria, particularly severe disease, when administered according to recommended schedules. However, vaccination should complement rather than replace other established preventive interventions.
Community health education is fundamental to achieving sustainable malaria control. Public awareness programmes should provide accurate information about malaria transmission, early warning signs, available preventive measures, and the importance of seeking prompt medical attention when symptoms develop. Healthcare workers, schools, community leaders, and local organisations can contribute to educating households and encouraging responsible health practices.
The effective malaria prevention requires the continuous integration of personal protection, vector management, vaccination, environmental sanitation, and community participation. Consistent implementation of these interventions can reduce mosquito-human contact, interrupt transmission pathways, and minimise the burden of malaria. Strengthening preventive infrastructure and ensuring equitable access to essential interventions are therefore critical to achieving long-term malaria control.
References
Cowman, A. F., Healer, J., Marapana, D., & Marsh, K. (2016). Malaria: Biology and disease. Cell, 167(3), 610–624.
Fikadu, M., & Ashenafi, E. (2023). Malaria: An overview. Infection and Drug Resistance, 16, 3339–3347.
Phillips, M. A., Burrows, J. N., Manyando, C., van Huijsduijnen, R. H., Van Voorhis, W. C., & Wells, T. N. C. (2017). Malaria. Nature Reviews Disease Primers, 3, Article 17050.
Aschengrau A and Seage G.R (2013). Essentials of Epidemiology in Public Health. Third edition. Jones and Bartleh Learning,
Gillespie S.H and Pearson R.D (2001). Principles and Practice of Clinical Parasitology. John Wiley and Sons Ltd. West Sussex, England.
Leventhal R and Cheadle R.F (2013). Medical Parasitology. Fifth edition. F.A. Davis Publishers,
Molyneux, D.H., D.R. Hopkins, and N. Zagaria (2004). Disease eradication, elimination and control: the need for accurate and consistent usage. Trends Parasitol, 20(8):347-51.
https://worldanimalfoundation.org/advocate/most-dangerous-animals-in-the-world
https://www.who.int/news-room/fact-sheets/detail/malaria
https://www.who.int/teams/global-malaria-programme
Discover more from Microbiology Class
Subscribe to get the latest posts sent to your email.


