

Gentamicin is an important aminoglycoside antibiotic widely recognized for its potent activity against a range of clinically significant bacterial pathogens. Its therapeutic relevance is closely associated with its ability to interfere with bacterial protein production, a process essential for cellular growth, maintenance, and replication. Unlike antibiotics that primarily disrupt cell-wall formation or nucleic-acid synthesis, gentamicin exerts its antibacterial effect through interaction with the bacterial ribosome, particularly the 30S ribosomal subunit. This interaction interferes with the accurate translation of messenger RNA and promotes the formation of abnormal proteins, ultimately contributing to irreversible damage within susceptible bacterial cells. The resulting antibacterial activity makes gentamicin particularly valuable in the management of serious infections where rapid and effective microbial control is required.
Gentamicin belongs to a broader class of antimicrobial agents known as aminoglycosides. This group includes clinically important compounds such as amikacin, tobramycin, kanamycin, neomycin, netilmicin, and streptomycin. Although these agents share a common ribosomal target, differences in their molecular structures, antimicrobial spectra, pharmacokinetic properties, and susceptibility to bacterial resistance mechanisms influence their individual clinical applications. Gentamicin is especially notable for its activity against many aerobic Gram-negative organisms and has also been incorporated into combination regimens when enhanced antibacterial efficacy is desirable.
The development of aminoglycosides represents a significant milestone in the history of antimicrobial chemotherapy. Streptomycin, the first widely recognized aminoglycoside, was isolated in 1943 from the actinomycete Streptomyces griseus. Its discovery emerged from investigations of soil microorganisms conducted by Selman Abraham Waksman and his collaborators, with Albert Schatz responsible for the laboratory isolation of streptomycin. The discovery demonstrated that soil-derived microorganisms could provide powerful therapeutic agents against bacterial diseases and established a foundation for the subsequent development of additional aminoglycoside antibiotics. Streptomycin became particularly important in the treatment of tuberculosis caused by Mycobacterium tuberculosis, where it was used alongside other antimycobacterial drugs.
The introduction of gentamicin into antimicrobial therapy subsequently expanded the therapeutic potential of the aminoglycoside class. However, its clinical use requires careful consideration because effective antibacterial concentrations must be balanced against the risk of toxicity, particularly nephrotoxicity and ototoxicity. These characteristics have made gentamicin not only an important antibacterial drug but also a significant subject of pharmacological and microbiological investigation.
Sources of gentamicin
Gentamicin originates from a naturally occurring microbial source and belongs to the aminoglycoside class of antibacterial agents. It is primarily obtained from species of the soil-dwelling actinomycete genus Micromonospora, particularly Micromonospora purpurea. These microorganisms are filamentous, Gram-positive bacteria commonly found in terrestrial environments and are capable of producing biologically active secondary metabolites. During microbial fermentation, the organism synthesizes gentamicin-related compounds as part of its secondary metabolic processes. The resulting antibiotic complex contains several closely related components, with gentamicin C compounds being particularly important for pharmaceutical applications.
Industrial production of gentamicin generally begins with the controlled cultivation of the producing Micromonospora strain in a suitable fermentation medium. Conditions such as nutrient composition, temperature, pH, aeration, agitation, and fermentation duration are carefully regulated to encourage antibiotic biosynthesis. After fermentation, the culture broth undergoes downstream processing to separate the antibiotic from microbial cells, residual nutrients, pigments, and other unwanted metabolites. Purification and concentration steps are subsequently employed to obtain a pharmaceutical-grade gentamicin preparation.
Unlike some modern aminoglycosides, gentamicin is not primarily manufactured by complete chemical synthesis. Its natural microbial origin provides the fundamental molecular framework responsible for antibacterial activity. The broader aminoglycoside family includes compounds obtained through semisynthetic modification. In such approaches, naturally occurring aminoglycoside structures are chemically altered to improve properties such as antibacterial spectrum, stability, pharmacokinetic behavior, or resistance to bacterial inactivating enzymes.
Gentamicin represents an important example of microbial biotechnology in pharmaceutical production. Its discovery from Micromonospora demonstrates the value of soil microorganisms as reservoirs of therapeutically useful metabolites. Advances in fermentation technology, strain selection, metabolic optimization, and purification have subsequently enabled more consistent production of gentamicin for clinical and research applications. The distinction between natural fermentation, semisynthetic modification, and total chemical synthesis is important when describing the origin and manufacturing pathways of aminoglycoside antibiotics.
Structure of gentamicin
Gentamicin is a structurally complex aminoglycoside antibiotic characterized by a highly polar, polycationic molecular framework. Its architecture is centered on a six-membered aminocyclitol ring, which serves as the core scaffold for the attachment of amino-sugar residues (Figure 1). This arrangement gives gentamicin its distinctive physicochemical properties and contributes substantially to its interaction with bacterial ribosomal targets.
Unlike simple carbohydrates, the sugar components of gentamicin contain multiple amino and hydroxyl functionalities. These functional groups remain extensively protonated under physiological conditions, resulting in a molecule with a strong cationic character. The positively charged regions facilitate electrostatic interactions with negatively charged bacterial cell-envelope components, particularly membrane-associated molecules. Such interactions are important during the initial stages of aminoglycoside uptake into susceptible bacterial cells.
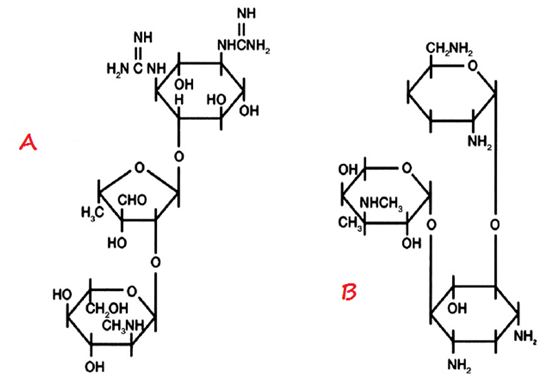
Gentamicin is not a single chemically uniform compound. It represents a mixture of closely related aminoglycoside components, principally gentamicin C1, C1a, and C2, which differ subtly in their substitution patterns. These structural variations arise from differences in the biosynthetic modification of the aminocyclitol-containing scaffold. Although closely related, the individual components can exhibit differences in physicochemical behavior and biological activity.
At the molecular level, the gentamicin framework can be viewed as a polyfunctional three-ring system. The central aminocyclitol nucleus is glycosidically connected to amino-sugar moieties, creating a compact but highly functionalized structure. The abundance and spatial arrangement of amino groups contribute to its basicity, water solubility, and affinity for anionic molecular targets. The glycosidic linkages also provide the conformational organization required for productive interactions with bacterial RNA.
Structural features of gentamicin are closely associated with its antibacterial mechanism. After entering susceptible bacterial cells, gentamicin interacts primarily with the 30S ribosomal subunit, where it binds to the decoding region of bacterial ribosomal RNA. This interaction interferes with accurate interpretation of messenger RNA and promotes production of aberrant proteins. The structural organization of gentamicin is not merely a chemical descriptor; it underpins the molecular events responsible for its bactericidal activity.
The aminocyclitol scaffold has also served as a foundation for the development of other aminoglycosides. Semi-synthetic modification of related natural aminoglycoside structures has produced agents such as tobramycin and amikacin, with alterations designed to influence antibacterial spectrum, enzymatic susceptibility, and pharmacological characteristics. The structure of gentamicin represents both a functional antimicrobial architecture and an important template in aminoglycoside medicinal chemistry.
Clinical application of gentamicin
Gentamicin is an aminoglycoside antibiotic with an important role in the management of serious bacterial infections, particularly those involving aerobic Gram-negative organisms. Its clinical value arises from its rapid bactericidal activity and ability to achieve high extracellular concentrations at sites of infection. Gentamicin is frequently incorporated into treatment regimens when organisms such as Pseudomonas aeruginosa, Klebsiella pneumoniae, Enterobacter species, and other susceptible Gram-negative bacilli are suspected or confirmed. Because many of these pathogens are associated with healthcare-associated infections, gentamicin may be particularly relevant in critically ill patients when rapid antimicrobial activity is required.
The use of gentamicin is not limited to Gram-negative infections. In selected clinical circumstances, it can provide synergistic activity against certain Gram-positive bacteria when administered alongside cell-wall-active antibiotics. This principle is particularly important in the treatment of some forms of infective endocarditis, where gentamicin may enhance the antibacterial effect of agents such as beta-lactams or glycopeptides against susceptible organisms. However, this synergistic application requires careful consideration of the patient’s renal function, bacterial susceptibility, treatment duration, and risk of aminoglycoside-associated toxicity.
Gentamicin has also been employed in the management of severe urinary tract infections, bloodstream infections, intra-abdominal infections, complicated wound infections, and other systemic infections caused by susceptible bacteria. Its penetration and pharmacodynamic properties make it useful when a rapid reduction in bacterial burden is desirable. Nevertheless, gentamicin should not be considered a universal treatment for bacterial infection. Its activity is restricted by intrinsic resistance mechanisms in certain organisms and by the increasing prevalence of acquired aminoglycoside resistance.
A clinically important limitation is that gentamicin has poor activity against anaerobic bacteria because aminoglycoside uptake into bacterial cells depends on an oxygen-dependent transport process. It is generally inappropriate as monotherapy for infections dominated by anaerobic organisms. Its effectiveness is also influenced by bacterial resistance mechanisms, including aminoglycoside-modifying enzymes, altered drug uptake, and changes in ribosomal binding sites.
Gentamicin is administered primarily by intravenous or intramuscular routes when systemic treatment is required. Unlike many antibiotics, its therapeutic use requires particular attention to pharmacokinetic and pharmacodynamic characteristics. The drug is eliminated predominantly through the kidneys, meaning that impaired renal function can substantially increase systemic exposure and the likelihood of toxicity. Dose selection and dosing intervals therefore need to be individualized according to renal function, body size, infection severity, and the therapeutic strategy being used.
The principal safety concerns associated with gentamicin are nephrotoxicity and ototoxicity. Prolonged exposure, excessive concentrations, pre-existing renal impairment, and concurrent administration of other nephrotoxic or ototoxic medicines can increase these risks. Therapeutic drug monitoring is consequently an important component of treatment when prolonged or high-intensity therapy is required.
Other aminoglycosides demonstrate different clinical applications. Streptomycin, for example, has historically occupied a specialized position in the treatment of tuberculosis and selected other infections. Neomycin, in contrast, is generally restricted to topical or localized applications because systemic administration is associated with substantial toxicity. Although aminoglycosides share a common mechanism of antibacterial action, their clinical roles differ according to antimicrobial spectrum, pharmacokinetics, toxicity profile, and therapeutic context.
Spectrum of activity of gentamicin
Gentamicin is an aminoglycoside antimicrobial agent with potent bactericidal activity against a range of clinically important bacteria. Its antibacterial spectrum is predominantly directed toward aerobic Gram-negative organisms, although it also demonstrates activity against selected Gram-positive bacteria, particularly when administered in combination with other antimicrobial agents. The effectiveness of gentamicin is strongly influenced by the susceptibility of the infecting organism, the site of infection, and the ability of the drug to reach adequate concentrations at the site of bacterial growth.
The principal antibacterial action of gentamicin results from its interaction with the 30S subunit of the bacterial ribosome. After entering the bacterial cell, gentamicin binds to ribosomal components involved in translation and interferes with the accurate decoding of messenger RNA. This disruption leads to the production of abnormal proteins, impairment of cellular functions, and progressive damage to the bacterial cell. Unlike bacteriostatic agents, which primarily suppress bacterial multiplication, gentamicin produces irreversible cellular injury that ultimately results in bacterial death.
Gentamicin exhibits particularly useful activity against members of the Enterobacterales, including organisms such as Escherichia coli, Klebsiella species, Enterobacter species, and Serratia species. It may also be active against several other aerobic Gram-negative pathogens, including Pseudomonas aeruginosa, although susceptibility varies and resistance is increasingly encountered. Microbiological susceptibility testing is important when gentamicin is considered for treatment of serious infections.
Among Gram-positive organisms, gentamicin generally has limited activity when used alone. However, it can exhibit synergistic antibacterial effects when combined with cell-wall-active antibiotics such as certain β-lactams or glycopeptides. This characteristic has contributed to its use in selected serious infections caused by susceptible Gram-positive organisms.
Gentamicin therefore possesses a clinically valuable but relatively selective antibacterial spectrum. Its bactericidal effect, concentration-dependent activity, and ability to enhance the activity of certain companion antibiotics make it useful in specific severe bacterial infections, while susceptibility patterns and potential toxicity must be carefully considered when selecting therapy.
Mechanism or mode of action of gentamicin
Gentamicin act through ribosomal disruption and bacterial protein synthesis inhibition. It exerts its antibacterial activity primarily by interfering with protein synthesis within susceptible bacterial cells. As an aminoglycoside antibiotic, it targets the bacterial ribosome, particularly the 30S ribosomal subunit, which plays a critical role in the accurate decoding of messenger RNA (mRNA) during translation. The interaction between gentamicin and the ribosome disrupts the normal process by which bacterial cells interpret genetic information and produce functional proteins.
After entering a susceptible bacterial cell, gentamicin associates with specific sites on the 30S ribosomal subunit. This interaction alters the structural and functional characteristics of the ribosome and compromises the accuracy of codon recognition. The ribosome may incorrectly interpret the sequence of mRNA, resulting in the incorporation of inappropriate amino acids into newly synthesized polypeptide chains. The production of these abnormal proteins can impair several essential cellular functions and progressively reduce bacterial viability.
Gentamicin also interferes with the initiation and progression of translation. By disturbing ribosomal activity, it prevents efficient formation and movement of functional translation complexes. The resulting disruption is particularly detrimental to rapidly multiplying bacteria that depend heavily on continuous protein production for cellular growth, metabolism, replication, and maintenance of membrane integrity.
An important characteristic of gentamicin’s action is that its antibacterial effect is not limited to temporary suppression of protein synthesis. The abnormal proteins generated as a consequence of translational errors may become incorporated into the bacterial cell membrane. Their presence can compromise membrane structure and permeability, facilitating further intracellular accumulation of gentamicin. This creates a progressive cycle of cellular injury in which increasing antibiotic uptake promotes additional ribosomal disruption and membrane damage.
The uptake of gentamicin into bacterial cells is influenced by physiological and environmental conditions. Following penetration into the bacterial cytoplasm, intracellular binding to ribosomes enables the drug to exert its principal pharmacological effect. Because this uptake process depends partly on cellular energy-dependent mechanisms, the activity of aminoglycosides may be reduced under conditions in which bacterial energy metabolism is impaired.
The combined effects of translation errors, defective protein production, ribosomal dysfunction, and membrane injury ultimately lead to bacterial cell death. Gentamicin is therefore considered bactericidal rather than merely bacteriostatic. Its activity is particularly pronounced against susceptible aerobic Gram-negative organisms, although it can also demonstrate enhanced activity against certain Gram-positive bacteria when used synergistically with other antimicrobial agents.
Gentamicin kills susceptible bacteria through a coordinated sequence of intracellular events beginning with interaction with the 30S ribosomal subunit and progressing to inaccurate mRNA decoding, defective protein synthesis, membrane disruption, and irreversible cellular damage. This multifaceted mechanism explains the potent bactericidal activity of gentamicin and provides the pharmacological basis for its clinical use against serious bacterial infections.
Bacterial resistance to gentamicin
Bacterial resistance to gentamicin represents an important challenge in the management of serious bacterial infections, particularly when treatment is prolonged or exposure to aminoglycosides is frequent. Resistance may develop through several biological mechanisms that reduce the ability of gentamicin to reach, recognize, or act on its intracellular target. One major mechanism involves alteration of the bacterial ribosomal target. Mutations affecting ribosomal proteins or ribosomal RNA can modify the binding environment for gentamicin, thereby reducing its interaction with the 30S ribosomal subunit. As a consequence, the drug becomes less capable of interfering with the normal process of bacterial protein synthesis.
Bacteria may also acquire resistance genes that encode aminoglycoside-modifying enzymes. These enzymes can chemically modify gentamicin through processes such as acetylation, phosphorylation, or adenylation, producing derivatives with substantially reduced antibacterial activity. Another mechanism involves changes in membrane permeability and active efflux, which limit intracellular accumulation of the drug. In some organisms, resistance may arise through reduced uptake associated with alterations in the bacterial envelope or metabolic state. Resistance determinants can also be transferred between bacteria through mobile genetic elements, including plasmids and transposons. The combined action of these mechanisms can markedly reduce gentamicin susceptibility and complicate antimicrobial therapy.
Pharmacokinetics of gentamicin
The pharmacokinetic characteristics of gentamicin strongly influence its clinical application and dosing requirements. Because gentamicin is a highly polar, water-soluble compound, gastrointestinal absorption following oral administration is extremely limited. Oral administration does not produce adequate systemic concentrations for the treatment of invasive bacterial infections. For systemic therapy, gentamicin is therefore generally administered by parenteral routes, particularly intravenous or intramuscular injection. Intravenous administration is commonly preferred when rapid and predictable drug exposure is required, especially in patients with severe infections.
Following administration, gentamicin distributes mainly within the extracellular fluid compartment and has relatively limited penetration into lipid-rich tissues. Penetration into the central nervous system is generally poor because of its physicochemical properties and restricted passage across biological barriers. Gentamicin is not extensively metabolized by the liver. Instead, the drug remains largely unchanged in the circulation and is eliminated predominantly through renal filtration. Renal function therefore has a major influence on systemic exposure and drug clearance.
Reduced kidney function can result in slower elimination and accumulation of gentamicin, increasing the probability of concentration-dependent toxicity. For this reason, dosage regimens are frequently adjusted according to renal function, body size, infection severity, and therapeutic drug-monitoring results. Gentamicin also exhibits concentration-dependent antibacterial activity and a post-antibiotic effect, allowing appropriately designed dosing schedules to maintain antibacterial efficacy while limiting unnecessary exposure.
Adverse effects and toxicity of gentamicin
Gentamicin possesses a clinically important toxicity profile, with nephrotoxicity and ototoxicity being the principal adverse effects associated with systemic treatment. Renal toxicity develops when gentamicin accumulates within renal tubular cells, where prolonged exposure can interfere with cellular integrity and normal tubular function. Clinically, this may manifest as increasing serum creatinine, reduced renal clearance, and other indicators of impaired kidney function. The likelihood of nephrotoxicity may increase with prolonged therapy, excessive drug exposure, pre-existing renal impairment, dehydration, advanced age, or concurrent use of other nephrotoxic medicines.
Ototoxicity is another significant concern because gentamicin can accumulate within tissues of the inner ear. Damage may involve either the cochlear structures responsible for hearing or the vestibular apparatus responsible for balance. Patients may develop hearing impairment, tinnitus, dizziness, or disturbances of equilibrium. Some forms of aminoglycoside-associated ototoxicity may be irreversible, making early recognition of auditory or vestibular symptoms particularly important.
Other reactions can occur but are generally less characteristic of gentamicin toxicity. Hypersensitivity reactions, gastrointestinal discomfort, neuromuscular blockade, and alterations in normal microbial flora have been reported. Severe neuromuscular effects are uncommon but may become clinically relevant in susceptible individuals or under specific treatment conditions. Continuous assessment of renal function, appropriate dose selection, and therapeutic drug monitoring can help minimize excessive systemic exposure and improve the safety of gentamicin therapy.
References
Chaves, B. J., & Tadi, P. (2023). Gentamicin. In StatPearls. StatPearls Publishing.
Hahn, F. E., & Sarre, S. G. (1969). Mechanism of action of gentamicin. The Journal of Infectious Diseases, 119(4–5), 364–369.
Krause, K. M., Serio, A. W., Kane, T. R., & Connolly, L. E. (2016). Aminoglycosides: An overview. Cold Spring Harbor Perspectives in Medicine, 6(6), a027029.
Nielson, C., Hsu, S., & Motaparthi, K. (2021). Topical antibacterial agents. In Comprehensive Dermatologic Drug Therapy (4th ed., pp. 465–479.e9). Elsevier.
Tangy, F., Moukkadem, M., Vindimian, E., Capmau, M. L., & Le Goffic, F. (1985). Mechanism of action of gentamicin components: Characteristics of their binding to Escherichia coli ribosomes. European Journal of Biochemistry, 147(2), 381–386.
Yoshizawa, S., Fourmy, D., & Puglisi, J. D. (1998). Structural origins of gentamicin antibiotic action. The EMBO Journal, 17(22), 6437–6448.
Axelsen P. H (2002). Essentials of Antimicrobial Pharmacology. Humana Press, Totowa, NJ.
Denyer S.P., Hodges N.A and Gorman S.P (2004). Hugo & Russell’s Pharmaceutical Microbiology. 7th ed. Blackwell Publishing Company, USA. Pp.152-172.
Discover more from Microbiology Class
Subscribe to get the latest posts sent to your email.

