Antibiotics are an important group of antimicrobial medicines developed to prevent and treat infections caused by bacteria. Their therapeutic action is directed toward bacterial cells and their essential biological processes, allowing clinicians to control infections that may otherwise progress to serious disease. Depending on the individual drug, antibiotics may either inhibit bacterial multiplication or directly damage bacterial cells, resulting in their elimination from the body. The development of antibacterial therapy has transformed modern medicine by making many previously life-threatening bacterial infections treatable and by supporting complex medical procedures such as surgery, organ transplantation, cancer chemotherapy, and intensive care.
Antibiotics act through several distinct mechanisms. Some interfere with the synthesis of the bacterial cell wall, which is essential for maintaining cellular integrity. Others inhibit protein production by targeting bacterial ribosomes, while additional agents interfere with DNA replication, RNA synthesis, or critical metabolic pathways. Antibiotics may also disrupt the bacterial cell membrane or interfere with specific biochemical processes required for survival. These differences in mechanism explain why individual antibiotics have different antibacterial spectra and why a particular drug may be effective against one bacterial species but ineffective against another.
A fundamental principle of antibiotic therapy is the distinction between bacterial and viral infections. Antibiotics are designed to act on bacterial structures or processes that are absent from viruses. They have no direct therapeutic effect against viral illnesses such as influenza, most uncomplicated common colds, and many other self-limiting viral respiratory infections. Using an antibiotic when there is no bacterial infection provides little or no clinical benefit while exposing the patient and the wider microbial environment to selective pressure. Correctly identifying the likely cause of an infection is therefore an important component of responsible antimicrobial treatment.
The selection of an antibiotic involves more than identifying whether bacteria are present. Clinicians may consider the suspected or confirmed pathogen, anatomical site of infection, severity of illness, patient-specific factors, previous antimicrobial exposure, local resistance patterns, and the drug’s pharmacokinetic and pharmacodynamic characteristics. Microbiological investigations, including culture and antimicrobial susceptibility testing, can provide additional information when bacterial identification is required. These results can help clinicians choose an agent that is active against the causative organism while avoiding unnecessarily broad treatment.
Antibiotic exposure can exert selective pressure on bacterial populations. Susceptible organisms may be inhibited or eliminated, whereas bacteria carrying resistance mechanisms can survive and multiply. Resistance may arise through genetic changes or through acquisition of resistance determinants from other bacteria. Mechanisms include drug inactivation, modification of antibiotic targets, reduced permeability, active efflux, and alternative metabolic pathways. Repeated or inappropriate antibiotic exposure can therefore contribute to the selection and dissemination of resistant organisms in the hospital and general environment.
Antimicrobial resistance has become particularly important in healthcare because resistant bacteria can restrict available treatment options and complicate infection management. Carbapenem-resistant Enterobacterales (CRE), for example, represent a significant category of resistant Gram-negative bacteria because they can withstand carbapenems, antibiotics often reserved for serious infections involving multidrug-resistant organisms. The emergence and transmission of such organisms demonstrate the connection between appropriate antibiotic use, infection prevention, microbiological surveillance, and effective clinical care.
Responsible antibiotic use therefore requires a balanced approach. Antibiotics should be prescribed when there is a reasonable indication for bacterial treatment, using an appropriate agent, dose, route, and duration. Unnecessary prescriptions, inappropriate dosing, and prolonged treatment can increase selective pressure without improving outcomes. Delayed or inadequate treatment of genuine bacterial infections can allow disease to worsen. Antimicrobial stewardship seeks to maintain this balance by promoting evidence-based prescribing while preserving antibiotic effectiveness for future patients.
Major antibacterial groups and their therapeutic characteristics
Antibiotics comprise a diverse collection of antibacterial compounds that differ in chemical structure, cellular targets, spectrum of activity, pharmacological behavior, and clinical applications. Classifying antibiotics according to their mechanism of action provides a useful framework for understanding how these medicines affect bacterial survival and why resistance can develop against particular agents. The principal classes of antibacterial agents include β-lactams, aminoglycosides, macrolides, tetracyclines, fluoroquinolones, glycopeptides, sulfonamides, and several newer or structurally distinct antibacterial groups.
β-Lactam antibiotics constitute one of the most widely used antibacterial families. This group includes penicillins, cephalosporins, monobactams, and carbapenems. Their defining structural feature is the β-lactam ring, which participates in inhibition of bacterial cell-wall synthesis. By interfering with penicillin-binding proteins, these agents impair peptidoglycan assembly and weaken the bacterial cell envelope. Carbapenems, including meropenem and imipenem, possess broad antibacterial activity and have traditionally been important for treating severe infections caused by organisms resistant to several other antibiotics. However, bacterial production of β-lactamases, particularly carbapenemases, can substantially reduce their effectiveness.
Aminoglycosides, such as gentamicin, amikacin, and tobramycin, primarily interfere with bacterial protein synthesis. They bind to the 30S ribosomal subunit and promote inaccurate translation of genetic information, ultimately disrupting essential cellular functions. These antibiotics are particularly relevant to serious infections caused by aerobic Gram-negative bacteria. Their use requires careful consideration of toxicity, especially nephrotoxicity and ototoxicity, because therapeutic effectiveness must be balanced against potential adverse effects.
Macrolides, including azithromycin, clarithromycin, and erythromycin, act mainly by binding to the 50S ribosomal subunit and suppressing bacterial protein production. Their activity against several respiratory pathogens has made them useful in the management of selected respiratory and other bacterial infections. Resistance may arise through modification of the ribosomal target, enzymatic drug modification, or increased drug efflux, limiting their usefulness against certain organisms.
Tetracyclines, represented by doxycycline and tetracycline, also target the bacterial ribosome. They attach to the 30S subunit and prevent the incorporation of aminoacyl-tRNA during protein synthesis. Their broad activity has supported their use against respiratory pathogens, intracellular bacteria, and several vector-borne infections. Doxycycline remains an important member of this class because of its versatile clinical applications.
Fluoroquinolones, such as ciprofloxacin, levofloxacin, and moxifloxacin, interfere with bacterial DNA replication by inhibiting DNA gyrase and topoisomerase IV. Their ability to penetrate various tissues contributes to their clinical utility, although increasing resistance and concerns regarding adverse effects have encouraged more selective prescribing.
Glycopeptides, particularly vancomycin, inhibit bacterial cell-wall synthesis through a mechanism distinct from that of β-lactams. They are especially important for infections caused by susceptible Gram-positive organisms, including certain resistant staphylococci and enterococci. Their limited activity against Gram-negative bacteria reflects differences in bacterial envelope architecture.
Sulfonamides and trimethoprim are known as antimetabolites because they interfere with sequential stages of bacterial folate metabolism. By restricting the production of metabolites required for nucleic acid synthesis, these agents can suppress bacterial proliferation. Their combined formulation, trimethoprim-sulfamethoxazole, provides activity against a range of clinically important pathogens.
Other antibiotic classes, including oxazolidinones, lipopeptides, polymyxins, and newer β-lactam/β-lactamase inhibitor combinations, expand the therapeutic options available for difficult-to-treat infections. Each class possesses characteristic strengths and limitations.
Classification of antibiotics according to their activity and chemical structure
Antibiotics can be classified into several categories according to their antibacterial spectrum, mode of action, and chemical composition. These classification systems provide a systematic framework for understanding the therapeutic properties of individual agents, their interactions with bacterial cells, and their potential limitations in clinical practice. The selection of an appropriate antibiotic depends on the characteristics of the causative microorganism, the site and severity of infection, and the susceptibility profile of the bacterial pathogen.
Based on their spectrum of activity, antibiotics are broadly categorized as broad-spectrum or narrow-spectrum agents. Broad-spectrum antibiotics act against a relatively wide range of bacterial species, encompassing different groups of Gram-positive and Gram-negative organisms. They may be useful when the causative pathogen has not yet been identified or when an infection involves multiple bacterial species. Unnecessary exposure to these agents can disrupt the normal microbiota and promote the selection of antimicrobial-resistant bacteria. Narrow-spectrum antibiotics exhibit activity against a more restricted group of microorganisms. Their targeted application can reduce unintended effects on beneficial bacterial populations and support more selective antimicrobial treatment. Narrow-spectrum antibiotics only target either Gram-positive or Gram-negative bacteria.
Another important classification distinguishes antibiotics according to their effects on bacterial viability. Based on their effects on bacterial viability, antibiotics can be classified as bactericidal antibiotics and bacteriostatic antibiotics. Bactericidal antibiotics directly kill susceptible bacterial cells by disrupting essential processes, including cell-wall synthesis, DNA replication, or membrane integrity. Bacteriostatic antibiotics, in comparison, primarily suppress bacterial growth and multiplication, allowing the host immune system to contribute to pathogen clearance. This distinction is not absolute, because the observed effect of an antibiotic may vary according to its concentration, the bacterial species involved, and the surrounding physiological conditions.
Chemical structure provides an additional basis for antibiotic classification. Structurally related compounds are grouped into families that share characteristic molecular features and frequently exhibit comparable antibacterial mechanisms. Examples include β-lactams, aminoglycosides, macrolides, tetracyclines, fluoroquinolones, and glycopeptides. Members of a particular family may demonstrate similarities in their bacterial targets, pharmacological properties, and susceptibility to specific resistance mechanisms. Individual agents within the same class can differ considerably in their antibacterial spectrum, tissue distribution, metabolic behavior, and clinical applications.
Structural similarities may also influence adverse drug reactions and immunological responses. Certain antibiotics within the same chemical family can exhibit cross-reactivity in patients with drug allergies, although the likelihood depends on the specific compounds and their molecular features. Likewise, related agents may share characteristic toxicological concerns without producing identical safety profiles.
These complementary classification approaches help explain the functional diversity of antibiotics and establish a foundation for rational antimicrobial selection. Integrating information about antibacterial spectrum, bactericidal or bacteriostatic activity, and chemical structure enables clinicians and microbiologists to interpret antibiotic properties more precisely while supporting appropriate prescribing and efforts to limit the emergence and spread of antimicrobial resistance.
Beta-lactam antibiotics
Beta-lactam antibiotics constitute a major class of antimicrobial agents distinguished by the presence of a four-membered beta-lactam ring (Figure 1). The beta-lactam ring of the beta-lactam antibiotics is a structural feature essential to their antibacterial activity. This group encompasses four principal families: penicillins, cephalosporins, carbapenems, and monobactams. Although these agents differ in their chemical architecture, antibacterial spectrum, pharmacokinetic properties, and susceptibility to resistance mechanisms, they share a fundamental mode of action involving the disruption of bacterial cell wall synthesis.
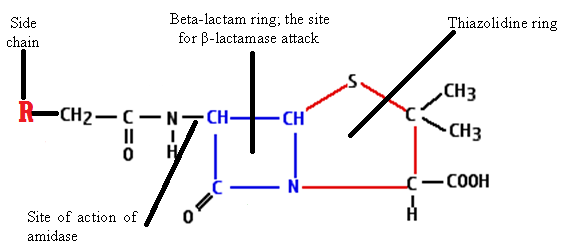
The antibacterial effect of beta-lactams arises primarily from their interaction with penicillin-binding proteins (PBPs). PBPs are enzymes responsible for the final stages of peptidoglycan assembly and cross-linking during cell wall formation in bacteria. Peptidoglycan provides mechanical strength and structural integrity to the bacterial cell wall, enabling bacteria to withstand internal osmotic pressure. By inhibiting PBP-mediated transpeptidation, beta-lactam antibiotics interfere with the formation of stable cross-links within the peptidoglycan network. The cell wall becomes structurally compromised, potentially leading to bacterial lysis and cell death. Their activity is generally most pronounced against actively growing and dividing bacteria.
Penicillins represent one of the earliest developed beta-lactam families and include agents such as amoxicillin, which is widely used against susceptible bacterial pathogens. Cephalosporins, including ceftriaxone, encompass multiple generations with differing spectra of activity and are employed in the management of various infections, including selected respiratory, bloodstream, and central nervous system infections. Carbapenems, such as meropenem and imipenem, possess broad antibacterial activity and are frequently reserved for serious infections involving susceptible organisms, particularly when resistance limits other treatment options.
Monobactams, represented by aztreonam, exhibit activity primarily against susceptible aerobic Gram-negative bacteria and may offer a useful alternative in selected clinical circumstances. Despite their therapeutic value, beta-lactam antibiotics face significant limitations arising from bacterial resistance. Beta-lactamase enzymes can hydrolyse the beta-lactam ring, rendering susceptible drugs ineffective. Additional resistance mechanisms include alterations in PBPs, reduced membrane permeability, and increased efflux of antimicrobial agents. These mechanisms can substantially diminish treatment efficacy and complicate infection management.
The clinical utility of beta-lactams therefore depends on accurate pathogen identification, susceptibility testing, appropriate drug selection, and suitable dosing. Their selective action on bacterial cell wall synthesis, a structure absent from human cells, underpins their therapeutic importance, although allergic reactions and other adverse effects remain relevant considerations. Rational prescribing and antimicrobial stewardship are essential to preserve the effectiveness of this diverse antibiotic class.
Macrolides
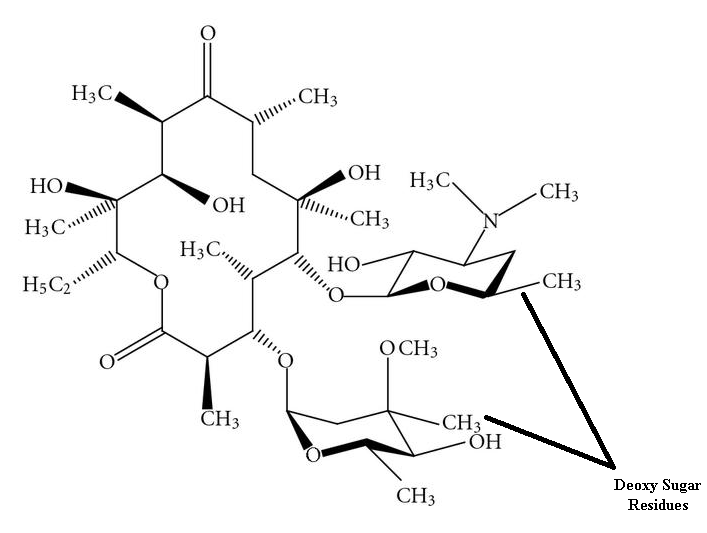
Macrolides constitute an important class of antibacterial agents distinguished by their ability to disrupt bacterial protein synthesis through selective interaction with the ribosomal machinery. Their characteristic macrocyclic lactone ring, attached to one or more deoxy-sugar residues, contributes to their structural identity, antibacterial activity, and pharmacological properties.
This class includes azithromycin, erythromycin, and clarithromycin, which are widely recognized for their therapeutic utility against selected Gram-positive bacteria, atypical respiratory pathogens, and other susceptible microorganisms. Macrolides are characterized by a large macrocyclic lactone ring to which one or more deoxy sugars, typically desosamine and cladinose, are attached, forming the structural basis of their antibacterial activity (Figure 1).
The principal mechanism of action of macrolides involves reversible binding to the 50S subunit of the bacterial ribosome, particularly within the region associated with the nascent peptide exit tunnel. This interaction interferes with peptide-chain elongation and translocation, thereby impairing the synthesis of essential bacterial proteins. Macrolides are generally bacteriostatic, although bactericidal activity may occur against certain organisms under specific concentration-dependent conditions. Their selective toxicity arises partly from structural differences between bacterial and mammalian ribosomes.
Clinically, macrolides occupy a significant position in the management of respiratory tract infections caused by susceptible organisms, including selected cases of community-acquired pneumonia, pertussis, and infections associated with Mycoplasma pneumoniae and Chlamydia pneumoniae. Azithromycin is characterized by prolonged tissue persistence and a relatively convenient dosing schedule, whereas clarithromycin exhibits activity against several respiratory pathogens and has a role in selected combination regimens for Helicobacter pylori eradication. Erythromycin remains relevant in particular clinical circumstances, including selected infections and certain motility-related disorders.
Despite these therapeutic advantages, macrolide effectiveness is increasingly challenged by antimicrobial resistance. Established resistance mechanisms include methylation of the 23S ribosomal RNA binding site, active efflux of the drug, and enzymatic modification of the antibiotic molecule. These mechanisms can reduce susceptibility and limit treatment options. Adverse effects due to macrolies administration also warrant consideration, for example gastrointestinal disturbances are common with Macrolides use and clinically significant drug interactions may occur with particular agents.
Erythromycin and clarithromycin have notable interactions involving cytochrome P450 enzymes, whereas azithromycin generally has a lower potential for such interactions. Macrolide selection should be guided by the suspected pathogen, local resistance patterns, patient-specific contraindications, and established clinical guidelines. Responsible prescribing, appropriate diagnostic evaluation, and adherence to recommended treatment regimens remain essential for preserving the clinical utility of this antibiotic class.
Tetracyclines
Tetracyclines constitute an important family of broad-spectrum antibacterial agents recognized for their activity against a wide variety of Gram-positive and Gram-negative organisms as well as several atypical bacterial pathogens. Their therapeutic significance is closely associated with their ability to interfere with bacterial protein synthesis, making them useful in the management of infections involving the respiratory tract, skin, gastrointestinal system, and other tissues. Commonly encountered members of this class include tetracycline, doxycycline, and minocycline, with doxycycline being particularly valuable because of its broad clinical utility and favorable pharmacokinetic characteristics.
The characteristic chemical structure of tetracyclines consists of four linearly fused six-membered hydrocarbon rings, with multiple hydroxyl, amide, keto, and dimethylamino substituents that contribute to their antimicrobial activity, chemical behavior, and interaction with bacterial ribosomes (Figure 3). Variations in these functional groups distinguish individual compounds and can influence their absorption, distribution, stability, and duration of action. The presence of several oxygen- and nitrogen-containing functional groups also allows tetracyclines to interact with metal ions such as calcium and magnesium.
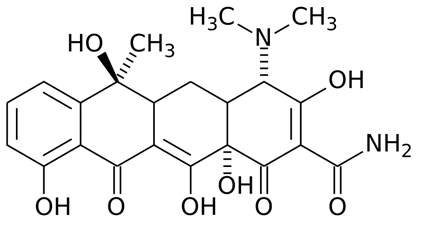
The principal antibacterial action of tetracyclines occurs at the 30S subunit of the bacterial ribosome. After entering susceptible bacterial cells, the drug associates reversibly with the ribosomal complex and prevents the attachment of aminoacyl-tRNA to the acceptor site. This interrupts the normal sequence of amino-acid incorporation during translation and consequently restricts bacterial protein synthesis. Because bacterial growth and replication depend heavily on continuous protein production, this interference produces a predominantly bacteriostatic effect.
Doxycycline has applications extending beyond conventional treatment of bacterial infections. It is used in conditions such as acne, certain respiratory infections, sexually transmitted infections caused by susceptible organisms, and several vector-borne diseases. Its activity against intracellular pathogens also contributes to its usefulness in selected clinical settings. Despite their therapeutic value, tetracyclines require appropriate administration and patient-specific consideration.
Tetracyclines can form poorly absorbed complexes with calcium, magnesium, iron, and aluminum, reducing drug absorption when taken together with dairy products or mineral-containing antacids and supplements. Tetracyclines may also cause gastrointestinal discomfort and photosensitivity. Their use during pregnancy and early childhood requires particular caution because tetracyclines can affect developing teeth and bones. Appropriate antimicrobial selection therefore depends on the causative organism, infection site, patient characteristics, and susceptibility profile.
Aminoglycosides
Aminoglycosides constitute an important group of bactericidal antimicrobial agents distinguished by their potent activity against a range of aerobic Gram-negative bacteria. Their antibacterial effect is primarily associated with interference with bacterial protein synthesis. Unlike many antibiotics that exert their effects through inhibition of cell-wall formation or nucleic-acid synthesis, aminoglycosides act directly at the bacterial ribosome, producing errors in the translation of genetic information and ultimately compromising bacterial viability.
Chemically, aminoglycosides are characterized by a highly polar structure composed of amino-modified sugars connected through glycosidic linkages to an aminocyclitol nucleus (Figure 4). For example, gentamicin and amikacin contain a 2-deoxystreptamine core, whereas streptomycin contains a streptidine component. The abundance of amino and hydroxyl groups makes these compounds strongly hydrophilic and positively charged under physiological conditions, properties that influence their transport into bacterial cells and their pharmacokinetic behavior.
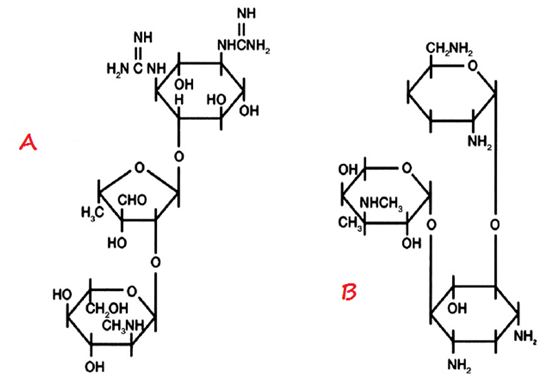
At the molecular level, aminoglycosides enter susceptible bacteria through a combination of diffusion and energy-dependent transport mechanisms. Once inside the cell, they interact predominantly with the 30S subunit of the bacterial ribosome. This interaction alters the accuracy of codon recognition during translation, causing the incorporation of incorrect amino acids into newly synthesized proteins. The resulting abnormal proteins can disrupt essential cellular processes and damage the bacterial membrane, creating a self-amplifying bactericidal effect. Their activity is therefore dependent not only on ribosomal binding but also on adequate intracellular accumulation.
Representative members include gentamicin, amikacin, and streptomycin. Gentamicin is frequently used for serious infections caused by susceptible Gram-negative organisms and may also be combined with other antibacterial agents in selected clinical situations. Amikacin retains activity against certain organisms that have developed resistance to other aminoglycosides and is consequently valuable in treating difficult infections. Streptomycin, one of the earliest clinically important aminoglycosides, remains relevant for selected bacterial diseases despite its more restricted contemporary use.
A major limitation of aminoglycoside therapy is their potential for nephrotoxicity and ototoxicity. Accumulation within renal tubular cells may impair kidney function, while exposure of the inner ear can produce irreversible auditory or vestibular injury. Clinical administration often requires careful dose adjustment, monitoring of renal function, and, when appropriate, measurement of drug concentrations. Their powerful bactericidal activity must therefore be balanced against these significant toxicity risks.
Quinolones
Quinolones constitute an important class of synthetic antibacterial agents distinguished by their ability to interfere with bacterial DNA replication. Unlike many naturally derived antibiotics, quinolones were developed through chemical modification and optimization of small molecules to produce compounds capable of selectively targeting essential bacterial enzymes. Their development began with early compounds such as nalidixic acid and subsequently expanded into a diverse group of quinolone derivatives with improved antibacterial activity and pharmacological properties.
The antibacterial activity of quinolones is primarily associated with their interaction with bacterial DNA gyrase and topoisomerase IV. These enzymes regulate the topology of bacterial DNA during replication and transcription by introducing temporary breaks into DNA strands and subsequently resealing them. Quinolones interfere with this process by stabilizing enzyme–DNA complexes, preventing the normal rejoining of DNA strands. The resulting disruption causes accumulation of damaged DNA and ultimately interferes with bacterial growth and survival.
A characteristic feature of quinolones is their defined heterocyclic chemical framework. The core structure consists of a fused bicyclic quinolone ring system containing a carbonyl group and a carboxylic acid group, with variations in substituents around this nucleus producing differences in antibacterial potency, spectrum, and pharmacokinetic behavior (Figure 5). Nalidixic acid represents an early member of this structural family and provided the foundation for subsequent molecular modifications.
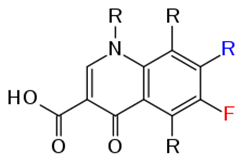
Nalidixic acid demonstrated activity mainly against susceptible Gram-negative bacteria and was initially associated with the treatment of urinary tract infections. Continued structural development produced newer quinolone compounds with enhanced antibacterial properties. Modifications of the quinolone nucleus and its substituent groups influenced characteristics such as tissue penetration, bacterial target affinity, metabolic stability, and activity against a broader range of organisms.
Quinolones therefore illustrate how systematic chemical modification can transform an antibacterial scaffold into compounds with distinct biological properties. Their mechanism, based on disruption of bacterial DNA-processing enzymes, differentiates them from antibiotics that primarily target the bacterial cell wall or ribosome.
Fluoroquinolones
Fluoroquinolones constitute an important group of synthetic antibacterial agents developed from the quinolone scaffold through structural modifications designed to enhance antibacterial potency, tissue penetration, and pharmacological performance. Their characteristic feature is the incorporation of a fluorine atom, most commonly at the C-6 position of the quinolone nucleus, which contributes substantially to their antimicrobial activity. Representative members include ciprofloxacin, levofloxacin, moxifloxacin, and ofloxacin. Although these compounds share a common structural framework, variations in their substituent groups produce differences in antibacterial spectrum, pharmacokinetic properties, and clinical applications (Figure 6).
The basic chemical structure of fluoroquinolones consists of a bicyclic quinolone core containing a carboxylic acid group and a ketone group, with a fluorine substituent typically attached to carbon-6 and additional modifications at other positions of the ring system. These structural features allow the compounds to interact efficiently with bacterial DNA-processing enzymes. Fluoroquinolones primarily exert their antibacterial effect by targeting DNA gyrase and topoisomerase IV. These enzymes are essential for DNA replication, transcription, and chromosome segregation. Stabilization of enzyme-DNA complexes interferes with normal DNA processing and ultimately produces lethal damage within susceptible bacterial cells.
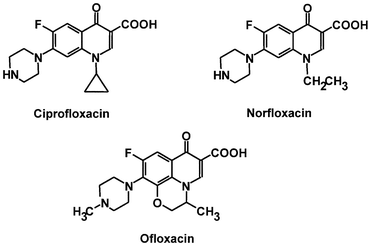
Ciprofloxacin demonstrates strong activity against many Gram-negative organisms and has been used in infections involving the urinary and gastrointestinal tracts. Levofloxacin possesses a broader activity profile and is commonly associated with respiratory, urinary, and selected skin infections. Moxifloxacin has enhanced activity against several Gram-positive and atypical respiratory pathogens and is frequently considered in the management of particular respiratory infections. The selection of an individual fluoroquinolone depends on the suspected organism, infection site, local resistance patterns, patient-specific factors, and pharmacokinetic considerations.
Despite their therapeutic value, fluoroquinolones require careful use because they can produce clinically significant adverse effects. Adverse effects include gastrointestinal disturbances, headache, dizziness, and skin reactions, while less common but potentially serious effects include tendon injury, peripheral neuropathy, and disturbances of cardiac repolarization. Their extensive use has also contributed to the emergence of resistant bacterial populations. Resistance may arise through mutations affecting DNA gyrase or topoisomerase IV, reduced intracellular drug accumulation, or enhanced efflux mechanisms. Appropriate antimicrobial selection and stewardship are essential for preserving the effectiveness of this class of antibiotic.
Sulfonamides
Sulfonamides represent an important group of synthetic antimicrobial agents that interfere with bacterial folate metabolism. Folate metabolism is an essential biochemical pathway required for the synthesis of nucleotides and ultimately for bacterial growth and replication. Unlike many antibiotics that directly damage cellular structures, sulfonamides act primarily by creating a metabolic deficiency within susceptible microorganisms. Their antibacterial activity is largely associated with their structural resemblance to para-aminobenzoic acid (PABA).
PABA is a naturally occurring substrate required for folate production. By competing with PABA, sulfonamides interfere with the enzymatic conversion of PABA into dihydropteroic acid, thereby reducing the availability of folate derivatives needed for DNA synthesis. A representative compound of the sulfonamide is sulfamethoxazole, which contains a sulfonamide functional group. It consist of a sulfur atom double-bonded to two oxygen atoms and bonded to an aromatic amine-containing moiety, together with a five-membered isoxazole ring that contributes to its molecular characteristics.
The sulfonamide structural group consists of a sulfonyl group bonded to an amine group (Figure 7). Sulfanilamide is the first member of the sulfonamide group to be discovered. The structure of the sulfonamides is chemically similar to the structure of PABA. Sulfonamides are notable for competing with p-aminobenzoic acid for inclusion in the folic acid molecule, and are generally known as antimetabolites. Sulfanilamide is the foundational derivative from which other sulfonamide antibiotics were chemically engineered by modifying its structure.
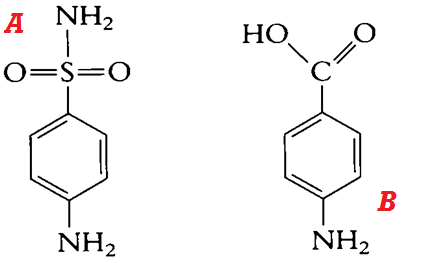
This chemical architecture allows the molecule to interact effectively with the bacterial folate-synthesis pathway. Sulfamethoxazole is frequently administered in combination with trimethoprim, which inhibits a subsequent step in folate metabolism. The sequential blockade produced by this combination can generate substantially greater antibacterial activity than either compound alone. Sulfonamides have historically been used against a broad range of bacterial pathogens and remain clinically relevant in selected infections.
Their applications include urinary tract infections and certain gastrointestinal, respiratory, and opportunistic infections, depending on local susceptibility patterns. The combination of sulfamethoxazole and trimethoprim is particularly significant because it provides activity against several Gram-positive and Gram-negative organisms as well as selected opportunistic pathogens. The effectiveness of sulfonamides is influenced considerably by bacterial resistance.
Resistance to sulfonamides may develop through alterations in the target enzyme, increased production of PABA, reduced intracellular drug accumulation, or acquisition of resistance genes through horizontal gene transfer. These mechanisms can substantially reduce susceptibility and complicate empirical treatment. Additional considerations include hypersensitivity reactions, gastrointestinal effects, and disturbances associated with folate metabolism. The continued usefulness of sulfonamides depends on appropriate antimicrobial selection, susceptibility testing where indicated, and responsible prescribing practices that minimize unnecessary selection pressure.
Glycopeptides
Glycopeptide antibiotics constitute a structurally distinctive class of antimicrobial agents whose principal target is the bacterial cell wall. Their activity is particularly important against susceptible Gram-positive organisms because the thick peptidoglycan layer of these bacteria provides accessible targets for glycopeptide binding. Rather than entering the bacterial cell and acting on an intracellular enzyme, glycopeptides interfere with synthesis of the cell wall from the extracellular side. This mechanism ultimately compromises cell-wall integrity and can lead to bacterial death.
Vancomycin is the best-known representative of this class of antibiotic. Chemically, it is a large, complex glycopeptide molecule containing a cross-linked peptide-derived core decorated with carbohydrate residues and several aromatic components, including chlorinated aromatic groups. Its highly organized three-dimensional structure is essential for recognition of the terminal peptide sequence involved in bacterial cell-wall synthesis. Vancomycin binds with high affinity to the D-alanyl-D-alanine terminus of peptidoglycan precursors. This interaction obstructs the enzymes responsible for transglycosylation and transpeptidation, preventing effective elongation and cross-linking of the bacterial cell wall.
Glycopeptides are particularly valuable in the management of serious infections caused by Gram-positive bacteria when resistance to other antimicrobial classes is present or when alternative agents are unsuitable. Vancomycin has an established role in infections caused by susceptible strains of Staphylococcus aureus, including many methicillin-resistant strains, as well as selected infections involving streptococci and enterococci. Its clinical use is influenced by the site and severity of infection, the susceptibility profile of the organism, and the pharmacokinetic characteristics of the drug.
Resistance to glycopeptides represents an important therapeutic challenge. Some bacteria can modify the terminal structure of their peptidoglycan precursors from D-alanyl-D-alanine to alternative termini such as D-alanyl-D-lactate. This apparently small structural modification markedly decreases glycopeptide binding and allows continued cell-wall synthesis despite the presence of the antibiotic. Such resistance mechanisms are particularly concerning in enterococci and have also been identified in certain S. aureus populations. In addition, vancomycin requires careful clinical monitoring because excessive exposure can contribute to nephrotoxicity.
References
Carlson-Banning, K. M., & Zechiedrich, L. (2015). Antibiotic classes and mechanisms of resistance. In S. K. Highlander, F. Rodriguez-Valera, & B. A. White (Eds.), Encyclopedia of metagenomics. Springer.
Coates, A. R., Halls, G., & Hu, Y. (2011). Novel classes of antibiotics or more of the same? British Journal of Pharmacology, 163(1), 184–194.
de Souza Mendes, C. D., & de Souza Antunes, A. M. (2013). Pipeline of known chemical classes of antibiotics. Antibiotics, 2(4), 500–534.
Eyler, R. F., & Shvets, K. (2019). Clinical pharmacology of antibiotics. Clinical Journal of the American Society of Nephrology, 14(7), 1080–1090.
Frank, U., & Tacconelli, E. (2012). Classification of the antibiotics. In The Daschner guide to in-hospital antibiotic therapy. Springer.
Kapoor, G., Saigal, S., & Elongavan, A. (2017). Action and resistance mechanisms of antibiotics: A guide for clinicians. Journal of Anaesthesiology Clinical Pharmacology, 33(3), 300–305.
Walsh, C. (2003). Introduction to major antibiotic classes and modes of action. In C. Walsh (Ed.), Antibiotics. ASM Press.
Wong, F., Zheng, E. J., Valeri, J. A., et al. (2024). Discovery of a structural class of antibiotics with explainable deep learning. Nature, 626, 177–185.
Discover more from Microbiology Class
Subscribe to get the latest posts sent to your email.