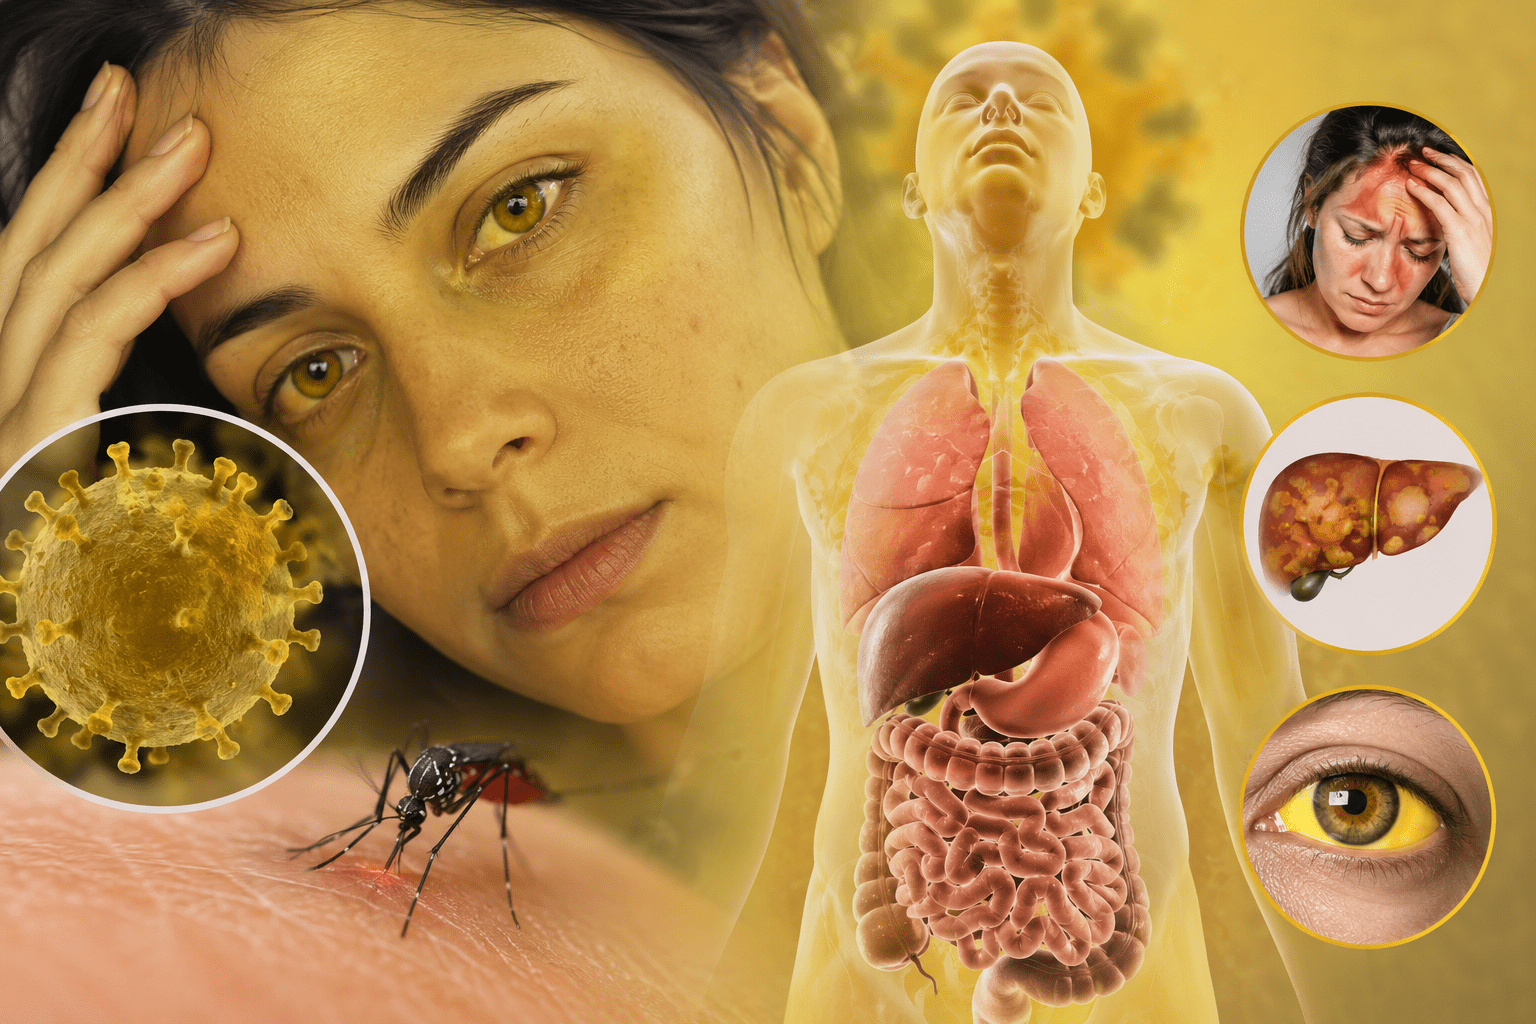
Yellow fever is an acute viral mosquito-borne disease that remains an important public health concern in tropical and subtropical regions of Africa and South America. Despite the availability of an effective vaccine, the infection continues to occur in areas where environmental conditions support the circulation of the virus and where populations remain vulnerable to mosquito-borne transmission. The disease is caused by yellow fever virus (YFV), an enveloped, single-stranded RNA virus belonging to the genus Flavivirus within the family Flaviviridae. Its transmission is closely linked to mosquito vectors and the ecological environments in which these vectors, virus, and susceptible hosts interact. The occurrence of yellow fever is strongly influenced by geographic location, mosquito populations, climate, and patterns of human movement.
Humans acquire yellow fever primarily through the bite of an infected mosquito. Different transmission cycles operate in endemic regions, involving interactions among mosquitoes, non-human primates, and humans. In forested environments, the virus can circulate between mosquitoes and wild primates, with humans becoming infected when they enter or live near these transmission zones. In some settings, transmission can extend into more densely populated areas when infected mosquitoes encounter susceptible human populations. This ecological complexity makes yellow fever more than an individual clinical problem; it represents a disease shaped by interactions between infectious agents, vectors, wildlife, human communities, and the surrounding environment.
Following infection, the clinical presentation of yellow fever can vary considerably. Some infected individuals experience a relatively mild, nonspecific illness characterized by fever, headache, muscle aches, fatigue, nausea, or other constitutional symptoms. In such cases, the disease may resemble several other febrile illnesses that are common in tropical regions, making recognition based solely on clinical manifestations challenging. However, a proportion of patients develop a much more serious form of disease after an initial period of illness. Severe yellow fever can involve hepatic injury, hemorrhagic manifestations, jaundice, renal dysfunction, and systemic organ failure. The characteristic yellow discoloration of the skin and eyes, reflected in the disease’s name, results from impaired liver function and the accumulation of bilirubin. Severe disease can progress rapidly and may be fatal, emphasizing the importance of early recognition and appropriate supportive care.
Although yellow fever is not commonly acquired by travelers from the United States, infection remains a relevant consideration for people visiting or residing in endemic regions. International travel can place individuals without previous immunity in environments where exposure to infected mosquitoes is possible. Risk is influenced by destination, season, duration and type of travel, mosquito exposure, and vaccination status. Travelers may also unknowingly enter areas where transmission is occurring because the geographic distribution of risk can change over time. For this reason, an individual’s travel history is an essential component of evaluating an unexplained febrile illness after travel to a region where yellow fever occurs.
Diagnosis requires the integration of clinical, epidemiological, and laboratory information. Because the early symptoms of yellow fever overlap with those of other infections, including malaria and other mosquito-borne viral diseases, clinical findings alone may not establish the diagnosis. Laboratory methods can provide evidence of infection, while information about recent travel and potential mosquito exposure helps place the findings in an appropriate epidemiological context. Accurate diagnosis is particularly important because suspected cases may have implications beyond the individual patient, including the potential for continued transmission in areas where competent mosquito vectors are present.
At present, there is no specific antiviral treatment that eliminates yellow fever virus from the body. Management of symptomatic disease therefore focuses primarily on supportive medical care and the treatment of complications. This therapeutic limitation places prevention at the center of yellow fever control. The most effective preventive measure is vaccination, which provides protection against infection and helps reduce the number of susceptible individuals within populations. Personal measures that reduce mosquito exposure are also important. These include applying appropriate insect repellent, wearing long-sleeved clothing and long trousers, and taking practical steps to limit contact with mosquitoes, particularly in areas and situations where vector exposure is likely.
Yellow fever therefore illustrates the continuing importance of mosquito-borne viral diseases in global health. Its persistence reflects a dynamic relationship between viral circulation, mosquito ecology, environmental conditions, human behavior, and population immunity.
Causative agent of yellow fever
Yellow fever is caused by yellow fever virus (YFV). YFV is an enveloped RNA virus belonging to the genus Flavivirus and the family Flaviviridae. It is an important human pathogen associated primarily with transmission by infected mosquitoes in tropical regions of Africa and South America. Despite its relatively small genome, the virus has a complex interaction with both mosquito vectors and vertebrate hosts.
Yellow fever virus carries a single-stranded, positive-sense RNA genome that functions directly as messenger RNA after entering a susceptible cell. The viral genome encodes a single polyprotein, which is subsequently processed into structural and non-structural proteins. The structural proteins form the viral particle, while the non-structural proteins participate in genome replication, protein processing, and manipulation of host-cell responses.
The mature virion is approximately spherical and contains a lipid envelope derived from the host cell membrane. Embedded within this envelope are viral proteins that are essential for attachment, entry, and infection of host cells. The envelope (E) protein is particularly important because it mediates interactions with host-cell receptors and participates in membrane fusion. The membrane (M) protein contributes to the organization and maturation of the viral particle.
Following transmission through the bite of an infected mosquito, YFV initially replicates in local tissues before disseminating through the bloodstream. The virus has a marked ability to infect cells of the liver, an organ that plays a central role in severe disease. Viral replication and associated cellular injury can produce hepatic dysfunction, which contributes to the characteristic jaundice from which the disease receives its name. In severe cases, infection may also affect other organs, including the kidneys and cardiovascular system.
Yellow fever virus is maintained in mosquito-primate transmission cycles. Different mosquito species participate in transmission depending on the geographic setting. Humans can become infected when bitten by an infectious mosquito, while non-human primates can serve as important reservoirs in sylvatic transmission cycles.
The biological significance of YFV extends beyond its ability to cause acute illness. Its capacity to circulate between mosquito vectors and vertebrate hosts makes ecological surveillance important in regions where transmission occurs. Prevention therefore relies heavily on vaccination, mosquito-control measures, and public-health surveillance.
Signs and symptoms of yellow fever infection
Yellow fever is an acute viral infection transmitted primarily through the bite of infected mosquitoes. Its clinical presentation can vary considerably, ranging from a short, self-limiting febrile illness to a severe, life-threatening disease involving multiple organs. Recognizing the pattern of symptoms is important because severe yellow fever can develop rapidly after an apparently mild beginning.
The illness commonly begins after an incubation period of several days. The initial stage may resemble other acute viral infections, making early recognition difficult. Typical symptoms include sudden fever, headache, chills, muscle aches, back pain, weakness, nausea, and vomiting. Loss of appetite and a general feeling of exhaustion may also occur.
Fever is often accompanied by marked malaise, with affected individuals feeling unusually tired or unwell. Headache and muscle pain can be prominent, while gastrointestinal symptoms such as nausea and vomiting may add to dehydration and physical weakness.
In many infected people, symptoms remain relatively mild and gradually resolve. Some patients experience a short period in which fever and other symptoms decrease, creating the impression that the illness is ending. This temporary improvement is an important feature of yellow fever because it does not necessarily indicate complete recovery.
A smaller proportion of patients progress to a more serious phase. Severe yellow fever may involve the liver, kidneys, heart, and other organs. Fever can return, accompanied by profound weakness and worsening systemic illness.
One of the most characteristic signs of severe disease is jaundice, in which the skin and whites of the eyes become yellow because of significant liver involvement. Dark urine may also develop. Bleeding can occur in severe cases, potentially appearing as bleeding from the nose or gums, blood in vomit, or other abnormal bleeding.
Kidney involvement may lead to reduced urine production, while severe systemic disease can cause confusion, altered consciousness, or extreme weakness. Abdominal pain may occur, particularly as liver and gastrointestinal complications develop.
Severe yellow fever is a medical emergency. Persistent or returning fever accompanied by jaundice, abnormal bleeding, repeated vomiting, reduced urination, confusion, or profound weakness requires immediate medical evaluation. These manifestations can indicate significant organ dysfunction.
Because the early symptoms overlap with many other infections, symptoms alone cannot reliably confirm yellow fever. Diagnosis requires appropriate clinical assessment and laboratory testing, particularly when there has been exposure in an area where yellow fever transmission occurs.
The clinical course therefore ranges from a brief febrile illness to rapidly progressive multisystem disease. Early recognition of warning signs, prompt medical assessment, and awareness of recent mosquito exposure or travel history are central to identifying potentially severe infection.
Transmission of yellow fever virus
Yellow fever virus (YFV) is an enveloped, single-stranded RNA virus belonging to the genus Flavivirus in the family Flaviviridae. It is closely related to other medically important flaviviruses, including West Nile virus, St. Louis encephalitis virus, and Japanese encephalitis virus. Yellow fever is a mosquito-borne viral infection, and transmission occurs primarily through the bite of infected mosquitoes belonging to the genera Aedes, Haemagogus, and Sabethes. The virus is maintained in transmission cycles involving mosquitoes, humans, and non-human primates.
Mosquitoes acquire YFV when they feed on the blood of a viremic human or non-human primate. Following infection, the virus replicates within the mosquito and subsequently reaches its salivary glands. The infected mosquito can then transmit the virus to another susceptible host during a subsequent blood meal. Infected humans are considered viremic, meaning that virus is present in the bloodstream and can be acquired by mosquitoes. Viremia generally begins shortly before the onset of clinical symptoms and usually persists for approximately five days after symptom onset. During this period, infected individuals can contribute to further transmission if competent mosquitoes are present.
Yellow fever virus is maintained through three major transmission cycles: the jungle (sylvatic), intermediate (savannah), and urban cycles. These cycles differ according to the mosquito vectors involved, the vertebrate hosts that maintain the virus, and the environmental setting in which transmission occurs (Figure 1).

The jungle or sylvatic cycle primarily involves transmission between non-human primates and forest-dwelling mosquitoes. In South America, mosquitoes of the genera Haemagogus and Sabethes are important vectors. Non-human primates serve as major amplifying hosts, while mosquitoes maintain the virus within forest ecosystems. Humans generally become infected when they enter or work in forested areas and are bitten by infected mosquitoes. Consequently, occupational and recreational activities in forest environments can increase the risk of infection among unvaccinated individuals.
The intermediate or savannah cycle, which is particularly important in Africa, occurs in humid or semi-humid areas bordering forests. In this cycle, mosquitoes can transmit YFV between non-human primates and humans, as well as among humans in some settings. Individuals living or working near forest margins may therefore be exposed to infected mosquitoes without entering deep forest environments. This transmission pattern can produce localized outbreaks and may serve as a bridge between sylvatic and urban transmission.
The urban cycle involves transmission primarily between humans through mosquitoes adapted to urban environments, especially Aedes aegypti. An urban outbreak may begin when a viremic person infected in a jungle or savannah setting enters a populated area. If competent mosquitoes feed on that person during the viremic period, they may become infected and subsequently transmit YFV to other susceptible individuals. High population density, inadequate vaccination coverage, and abundant mosquito populations can facilitate rapid amplification of transmission.
The epidemiology of yellow fever reflects a complex interaction between mosquito vectors, vertebrate hosts, human movement, environmental conditions, and population immunity. Understanding these transmission cycles is essential for surveillance, risk assessment, vaccination strategies, and the prevention and control of yellow fever outbreaks. Figure 1 illustrates the three principal transmission cycles and the movement of yellow fever virus between mosquitoes, non-human primates, and humans.
Pathogenesis of yellow fever virus
YFV is an enveloped, positive-sense single-stranded RNA virus belonging to the genus Flavivirus. Its pathogenesis is characterized by an initial phase of viral replication followed, in severe disease, by systemic dissemination and injury to multiple organs. The outcome depends on the balance between viral replication, innate immune responses, tissue tropism, and host inflammatory mechanisms.
Following the bite of an infected mosquito, YFV is deposited into the skin together with mosquito saliva. The virus initially encounters keratinocytes, fibroblasts, and resident antigen-presenting cells. Instead of remaining confined to the inoculation site, YFV can exploit these cells as an early amplification niche. Newly produced virions then gain access to draining lymphatic vessels and regional lymph nodes, where additional replication occurs. This early phase facilitates entry of the virus into the bloodstream, producing the characteristic viraemic stage.
Once viraemia develops, YFV reaches organs containing cells that support efficient viral replication. The liver represents the major target organ and is central to severe yellow fever pathology. Viral replication within hepatocytes and hepatic macrophage populations is associated with cellular stress, dysfunction, and cell death. Hepatocyte injury disrupts normal hepatic metabolism and contributes to impaired synthesis of coagulation factors. The resulting disturbance of haemostasis can manifest as bleeding, while extensive hepatic dysfunction contributes to jaundice and metabolic abnormalities.
A distinctive feature of severe yellow fever is the pattern of hepatic injury, which is not explained solely by direct viral cytolysis. Innate immune activation contributes substantially to tissue damage. Recognition of viral RNA by intracellular and extracellular pattern-recognition systems induces interferons and other inflammatory mediators. These responses can restrict viral replication, but excessive or poorly regulated inflammation may amplify cellular injury. Thus, antiviral immunity has a dual role: it limits viral expansion while potentially contributing to pathological inflammation.
The virus also affects the kidneys. Renal dysfunction may develop as a consequence of direct viral effects, systemic inflammation, circulatory disturbances, and the metabolic consequences of severe hepatic injury. Reduced renal filtration can produce accumulation of nitrogenous waste and disturbances in fluid and electrolyte balance. In advanced disease, hepatic and renal dysfunction may therefore reinforce one another, contributing to rapid clinical deterioration.
Haemorrhagic manifestations arise from several interacting mechanisms rather than a single defect. Severe hepatic dysfunction reduces production of clotting proteins, while endothelial disturbance, thrombocytopenia, coagulation abnormalities, and systemic inflammatory activation further compromise haemostasis. This creates a pathological environment in which relatively minor vascular injury can produce significant bleeding.
The cardiovascular system may become involved during severe infection. Systemic inflammatory mediators, vascular dysfunction, fluid loss, and myocardial injury can impair effective circulation. Reduced tissue perfusion subsequently worsens renal and hepatic dysfunction, establishing a self-reinforcing cycle of organ injury. Neurological manifestations, although less dominant than hepatic and haemorrhagic disease, can occur through systemic toxicity, metabolic disturbance, and, in some cases, neurological involvement.
Host immunity ultimately determines whether infection resolves or progresses toward severe disease. Effective early interferon responses can restrict viral multiplication, while adaptive immunity subsequently contributes to viral clearance through neutralizing antibodies and cellular immune mechanisms. When viral replication and systemic inflammation become sufficiently extensive, however, the physiological consequences may exceed the body’s capacity to compensate.
Yellow fever pathogenesis can be viewed as a dynamic progression from local viral amplification to lymphatic spread, viraemia, hepatic tropism, systemic immune activation, vascular and coagulation disturbances, and multiorgan dysfunction. The severe phenotype is therefore produced by an interaction between viral replication and host-mediated tissue injury rather than by viral presence alone.
Laboratory diagnosis of yellow fever infection
Laboratory diagnosis of yellow fever is important because its clinical presentation can resemble other acute febrile illnesses, including dengue, malaria, viral hepatitis, and other arboviral infections. Diagnosis is based on clinical findings, travel or exposure history, and laboratory confirmation.
During the early phase of illness, yellow fever virus can be detected directly in blood. Reverse-transcription polymerase chain reaction (RT-PCR) is commonly used to detect viral RNA, particularly during the first few days after symptom onset. Viral isolation in cell culture can also confirm infection, but it is mainly performed in specialized reference laboratories because of biosafety requirements and the time required.
As the immune response develops, serological testing becomes more useful. Detection of yellow fever virus-specific IgM antibodies by enzyme-linked immunosorbent assay (ELISA) can provide evidence of recent infection. However, IgM antibodies may cross-react with antibodies against other flaviviruses, such as dengue and West Nile virus. Therefore, a positive IgM result may require confirmation using a plaque reduction neutralization test (PRNT), particularly when cross-reactivity is a concern.
Other laboratory findings are supportive but not diagnostic. These may include leukopenia during the early stage, followed by leukocytosis in severe disease, elevated serum aminotransferases, hyperbilirubinemia, prolonged coagulation times, thrombocytopenia, and evidence of renal dysfunction. Severe cases may show markedly elevated liver enzymes and abnormalities in coagulation and renal function.
The choice of diagnostic test depends on the time since symptom onset and specimen availability. Blood or serum is generally used for molecular and serological testing. Testing should preferably be performed through appropriate public-health or reference laboratories, especially in regions where yellow fever is uncommon.
RT-PCR is particularly useful early in infection, while IgM serology becomes increasingly useful later. Because serological cross-reactivity can occur, laboratory results should always be interpreted together with clinical and epidemiological information.
Treatment of yellow fever infection
There is no specific antiviral treatment routinely recommended for yellow fever. Management is primarily supportive, with the aim of maintaining hydration, controlling symptoms, monitoring organ function, and treating complications. Patients with suspected or confirmed yellow fever should receive medical assessment, particularly because severe disease can progress rapidly.
In mild cases, treatment includes adequate rest, oral or intravenous fluids as needed, and management of fever and discomfort. Paracetamol (acetaminophen) may be used for fever and pain when appropriate. Aspirin and other non-steroidal anti-inflammatory drugs are generally avoided because yellow fever can cause thrombocytopenia, bleeding, and coagulation abnormalities.
Patients with severe yellow fever require hospitalization, often with close monitoring or intensive care. Intravenous fluids may be necessary to maintain circulation and correct dehydration. Blood pressure, oxygenation, urine output, blood glucose, liver function, renal function, and coagulation status should be monitored. Hypoglycemia may occur in severe disease and requires prompt correction.
Yellow fever can cause serious complications, including acute liver injury, kidney failure, bleeding, shock, and encephalopathy. These complications are treated according to standard supportive and critical-care principles. Patients who develop acute kidney injury may require renal replacement therapy, such as dialysis, when clinically indicated. Significant bleeding may require appropriate blood-product support.
Because yellow fever is a mosquito-borne viral infection, preventing further transmission is also important. During the period when virus may be present in the blood, patients should avoid exposure to mosquitoes by using insecticide-treated bed nets, protective clothing, and appropriate mosquito repellents. This reduces the possibility of mosquitoes acquiring the virus and transmitting it to other people.
Antibiotics do not treat yellow fever itself, although they may be prescribed if a separate bacterial infection is suspected or confirmed. The most effective preventive measure is yellow fever vaccination, which is highly effective and can prevent infection and severe disease. Early recognition, appropriate supportive care, monitoring for complications, and prevention of mosquito transmission are the main components of yellow fever management.
Epidemiology of yellow fever infection
Yellow fever is primarily transmitted to humans through the bite of infected mosquitoes. Yellow fever remains an important public-health problem in tropical regions of sub-Saharan Africa and South America, where environmental conditions support mosquito vectors and viral transmission.
Approximately 200,000 cases and 30,000 deaths are estimated to occur globally each year, with the majority of cases occurring in Africa. However, surveillance systems may underestimate the true burden because many infections are asymptomatic or clinically mild and may not be diagnosed. The disease has a wide clinical spectrum. Most infected individuals develop no symptoms or only a mild febrile illness, while a smaller proportion develop severe disease characterized by jaundice, bleeding, liver and kidney dysfunction, and shock. Severe cases have a high case-fatality rate.
Yellow fever transmission occurs through three principal epidemiological cycles: sylvatic, intermediate, and urban. In the sylvatic (jungle) cycle, the virus circulates between non-human primates and forest-dwelling mosquitoes. Humans become infected when they enter forested areas and are bitten by infected mosquitoes. This cycle is particularly important in parts of South America.
The intermediate cycle, mainly recognized in Africa, involves transmission between mosquitoes and both humans and non-human primates in humid or semi-humid savannah environments. People living or working near forest margins may be exposed, and this cycle can produce localized outbreaks.
The urban cycle occurs when infected humans introduce the virus into densely populated areas where competent Aedes mosquitoes transmit it from person to person. Urban transmission can lead to large outbreaks, particularly where population immunity is low and mosquito-control measures are inadequate.
Several factors influence yellow fever epidemiology. Vaccination coverage is the most important modifiable determinant of population susceptibility. Areas with low vaccination coverage can accumulate susceptible individuals, increasing the risk of outbreaks. Mosquito abundance, rainfall, temperature, deforestation, population movement, and human settlement patterns can also influence transmission. International travel can occasionally result in infected travelers introducing the virus into regions where competent mosquito vectors are present.
Yellow fever is endemic in more than 40 countries in tropical Africa and South America. Africa accounts for most of the global disease burden, while South America experiences periodic outbreaks, particularly in countries with extensive forested areas. Large outbreaks have occurred when virus transmission has expanded into populations with inadequate immunity.
Prevention relies heavily on vaccination with the highly effective live-attenuated yellow fever vaccine, combined with surveillance and mosquito-control measures. Routine immunization and mass vaccination campaigns are used in endemic areas, while vaccination may also be required or recommended for travelers entering certain countries. Early detection of cases is essential because rapid investigation and vaccination campaigns can help prevent outbreaks from becoming widespread.
Prevention of yellow fever
The most effective way to prevent yellow fever virus infection is to avoid mosquito bites and receive vaccination when recommended. Yellow fever is transmitted primarily by infected Aedes and other mosquito species. Because mosquitoes may bite during both daytime and nighttime, travelers and people living in risk areas should use multiple protective measures.
Prevent mosquito bites
Use insect repellant to prevent mosquito bite. Apply an Environmental Protection Agency (EPA)-registered insect repellent containing one of the following active ingredients:
- DEET. DEET stands for N,N-diethyl-meta-toluamide. It is a chemical compound used as an insect repellent.
- Picaridin (icaridin)
- IR3535 (Ethyl butylacetylaminopropionate), an insect repellant
- Oil of lemon eucalyptus (OLE)
- Para-menthane-diol (PMD)
- 2-undecanone
When used according to label instructions, EPA-registered repellents are considered safe and effective, including for pregnant and breastfeeding women.
For infants and children:
- Do not use insect repellent on infants younger than 2 months; instead, dress them in clothing that covers the arms and legs and use mosquito netting over strollers and carriers.
- Do not use OLE or PMD products in children younger than 3 years.
- Always follow the product label and avoid applying repellent to a child’s hands, eyes, mouth, cuts, or irritated skin.
- Adults should apply repellent to their own hands before applying it to a child’s face.
General repellent precautions:
- Reapply repellent according to the product instructions.
- Do not apply repellent to skin covered by clothing.
- If sunscreen is also needed, apply sunscreen first and insect repellent afterward.
- The effectiveness of non-EPA-registered, including some natural, repellents may be uncertain. Using an EPA-registered product provides evidence-based protection against mosquito bites.
Wear protective clothing
Wear long-sleeved shirts, long pants, and socks when possible. Clothing should provide adequate coverage, particularly in areas with active mosquito transmission.
Treat clothing and gear
Clothing and outdoor equipment can be treated with permethrin, an insecticide that kills or repels mosquitoes. Permethrin-treated clothing, boots, pants, socks, and tents can provide protection through multiple washings, although the duration varies by product.
- Follow the manufacturer’s instructions when treating clothing or equipment.
- Never apply permethrin directly to the skin.
- Check product instructions for the expected duration of protection.
Reduce mosquito exposure indoors and outdoors
Use window and door screens and repair damaged screens. Air conditioning can also reduce mosquito entry. To limit mosquito breeding, regularly empty, scrub, cover, or dispose of containers that collect standing water, including buckets, tires, flowerpots, toys, birdbaths, and other outdoor containers. Inspect both indoor and outdoor areas.
Vaccination
Yellow fever vaccination is the most important specific preventive measure. A single dose of yellow fever vaccine provides long-lasting protection for most people. Vaccination is recommended for people living in or traveling to areas where yellow fever transmission occurs, depending on the destination, travel itinerary, and individual health considerations. Some countries also require proof of vaccination for entry under specific circumstances.
Prevention during international travel
Travelers to yellow fever risk areas should check current vaccination recommendations before departure and seek advice from an appropriate travel-health professional. Choose accommodation with air conditioning or screened windows and doors. When sleeping in locations without adequate screening, use a mosquito bed net; insecticide-treated nets provide additional protection.
Because no single measure provides complete protection, combining vaccination, personal insect-bite prevention, protective clothing, and mosquito-control measures offers the most comprehensive approach to reducing the risk of yellow fever infection.
Yellow fever vaccine
A safe and effective yellow fever vaccine has been available for more than 80 years. It is a live-attenuated vaccine and remains the most important measure for preventing yellow fever. A single dose provides long-lasting, generally lifelong protection for most people, and routine booster doses are not required. Immunity develops rapidly, with most vaccinated individuals developing protection within 10 days and more than 99% by 30 days.
Yellow fever vaccination is recommended for people 9 months of age and older who live in or travel to areas of Africa and South America where there is a risk of yellow fever transmission. Vaccination may also be required as a condition of entry into certain countries to prevent international spread of the virus. Travelers should consult a healthcare provider or an official travel-health service before departure to determine whether vaccination is recommended or required.
Yellow fever vaccine recommendations
For most people, one dose provides lifelong protection, and a routine booster is unnecessary. However, additional vaccination may be considered in selected circumstances, such as certain travelers visiting areas with ongoing transmission or when specifically required by national regulations. Decisions should take into account the individual’s risk of exposure, destination, previous vaccination history, and current public-health recommendations.
The vaccine is generally recommended from 9 months of age. Vaccination of infants 6-8 months old, adults aged 60 years or older, pregnant women, and breastfeeding women requires individual assessment because the risk of adverse reactions or reduced immune response may be higher. In these situations, vaccination may nevertheless be appropriate when the risk of yellow fever exposure is substantial.
Contraindications
Yellow fever vaccine should not be administered to people with conditions associated with a substantially increased risk of serious vaccine-related complications. Important contraindications include:
- Infants younger than 6 months
- Severe allergy to a vaccine component, including severe allergy to eggs
- Primary immunodeficiency
- Certain malignant neoplasms
- Thymus disorders associated with abnormal immune function
- Organ transplantation
- Immunosuppressive or immunomodulatory therapy
- Symptomatic HIV infection or severe immunosuppression, including a CD4 count below 200 cells/mm³ in relevant patients.
Contraindications and precautions should be assessed by a healthcare professional before vaccination.
Reactions to yellow fever vaccine
Most adverse reactions are mild and short-lived. They may include headache, muscle aches, low-grade fever, and local discomfort. Serious adverse events are rare but can include severe allergic reactions (anaphylaxis), neurologic complications such as encephalitis or Guillain-Barré syndrome, and, very rarely, yellow fever vaccine-associated viscerotropic disease involving severe dysfunction of internal organs. Anyone who develops significant or persistent symptoms after vaccination, particularly high fever, severe weakness, difficulty breathing, neurological symptoms, or signs of organ dysfunction, should seek prompt medical assessment.
Yellow fever vaccine, pregnancy, and conception
Because yellow fever vaccine is live-attenuated, pregnancy is considered a precaution rather than an absolute contraindication. Pregnant women should generally avoid travel to areas where yellow fever transmission occurs when travel can be postponed. If travel is unavoidable and the risk of exposure is considered greater than the potential risk from vaccination, vaccination may be recommended following an individualized assessment.
Available experience has not demonstrated a clear increase in adverse pregnancy outcomes following inadvertent vaccination during pregnancy. Therefore, inadvertent vaccination is not generally considered an indication for termination of pregnancy. Pregnant individuals who receive the vaccine should discuss their circumstances with their healthcare provider, including whether additional vaccination or assessment may be appropriate because pregnancy can affect the immune response.
For conception after vaccination, CDC guidance recommends waiting 4 weeks after receiving yellow fever vaccine before becoming pregnant. Yellow fever vaccination provides highly effective protection against a potentially severe mosquito-borne infection. Decisions regarding vaccination should balance the individual’s risk of exposure against the potential risks of vaccination, particularly in people with relevant precautions or contraindications.
References
CDC. Yellow fever vaccine: recommendations of the Advisory Committee on Immunization Practices (ACIP). MMWR Morb Mortal Wkly Rep. 2010;59(RR-7):1–27.
CDC. Yellow fever vaccine booster doses: Recommendations of the Advisory Committee on Immunization Practices, 2015. MMWR Morb Mortal Wkly Rep. 2015;64(23):647–50.
CDC. Notes from the Field: Fatal Yellow Fever Vaccine–Associated Viscerotropic Disease — Oregon, September 2014. MMWR Morb Mortal Wkly Rep. 2015;64(10):279–281.
Chen, L. H., & Wilson, M. E. (2020). Yellow fever control: Current epidemiology and vaccination strategies. Tropical Diseases, Travel Medicine and Vaccines, 6, 1.
Gianchecchi, E., Cianchi, V., Torelli, A., & Montomoli, E. (2022). Yellow fever: Origin, epidemiology, preventive strategies and future prospects. Vaccines, 10(3), 372.
McGuinness, I., Beckham, J. D., Tyler, K. L., & Pastula, D. M. (2017). An overview of yellow fever virus disease. The Neurohospitalist, 7(4), 157–158.
Monath, T. P. (2001). Yellow fever: An update. The Lancet Infectious Diseases, 1, 11–20.
Monath, T. P., Gershman, M., Staples, J. E., & Barrett, A. (2012). Yellow fever vaccine. In S. A. Plotkin, W. A. Orenstein, & P. A. Offit (Eds.), Vaccines (pp. 870–968). Saunders.
Tuells, J., Henao-Martínez, A. F., & Franco-Paredes, C. (2022). Yellow fever: A perennial threat. Archives of Medical Research, 53(7), 649–657.
Barwick R. History of thymoma and yellow fever vaccination. Lancet. 2004;364(9438):936.
Cavalcanti DP, Salomao MA, Lopez-Camelo J, et al. Early exposure to yellow fever vaccine during pregnancy. Trop Med Int Health. 2007;12(7):833–7.
Discover more from Microbiology Class
Subscribe to get the latest posts sent to your email.